Red eye is one of the most common presenting complaints in eye care.
Most causes are benign, but a few threaten sight within hours.
Therefore, use a structured history and examination to find the dangerous ones first.
First Questions in a Red Eye
Ask about the onset, pain, photophobia, vision, discharge and previous episodes.
Also, ask about contact lens wear, trauma, chemical exposure and recent surgery.
Then ask about systemic disease, such as arthritis or skin disease.
Because the history narrows the list quickly, take it before you look.
Red Flags That Change Urgency
Reduced vision, severe pain and marked photophobia need same-day review.
Also, a corneal opacity, a hypopyon, a fixed pupil or halos around lights need an urgent referral.
Contact lens wearers with pain and recent eye surgery patients belong in the same group.
Therefore, never reassure a patient before you check acuity.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this sitePatterns of Redness
Diffuse redness that moves with the conjunctiva suggests conjunctival disease.
Circumcorneal injection, or ciliary flush, suggests keratitis, uveitis or angle closure.
Sectoral redness suggests episcleritis or scleritis (see episcleritis and scleritis).
Also, a single bright patch suggests subconjunctival hemorrhage (see subconjunctival hemorrhage).
Red Eye With Discharge
Watery discharge with a follicular reaction points to viral conjunctivitis (see epidemic keratoconjunctivitis).
Purulent discharge with lids stuck together points to bacterial disease.
Ropy discharge with itch points to allergy (see allergic conjunctivitis).
Painful Red Eye
Keratitis causes pain, photophobia and a corneal infiltrate that stains with fluorescein (see herpes simplex keratitis).
Acute anterior uveitis gives pain, photophobia and cells in the anterior chamber (see acute anterior uveitis).
Acute angle closure gives severe pain, a mid-dilated pupil, a hazy cornea and a high pressure (see acute angle closure glaucoma).
Painless Red Eye
Conjunctivitis is usually mild, and episcleritis is often painless.
Subconjunctival hemorrhage looks dramatic but needs only reassurance.
Also, check the blood pressure in recurrent cases.
Examination Sequence
Start with visual acuity and pupils.
Then examine the lids and conjunctiva, stain the cornea with fluorescein and look at the anterior chamber.
Finally, measure the intraocular pressure when angle closure or uveitis is possible.
Because each step answers a question, do not skip the stain.
Management and Pitfalls
Treat the cause, and refer when the diagnosis is uncertain.
Do not start topical steroids in a red eye without a diagnosis, since herpes and fungi can worsen.
Also, avoid patching in suspected infection, because it can promote growth.
Contact Lens Wearers With a Red Eye
Contact lens wearers need a careful corneal examination, since infection can progress quickly (see contact lens acute red eye).
Also, ask the patient to stop lens use and bring the case.
Therefore, treat every painful red eye in a lens wearer as keratitis until proven otherwise.
Red Eye After Eye Surgery
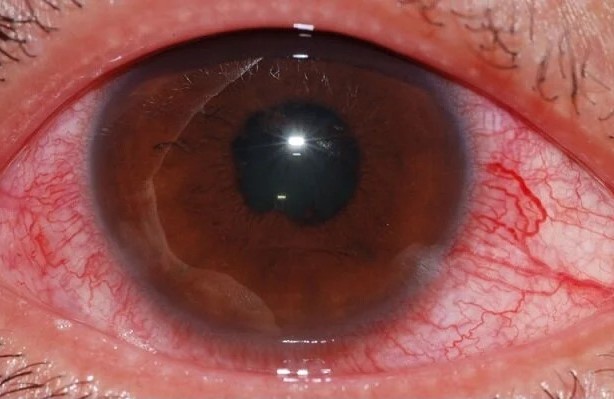
A red eye in the first weeks after cataract surgery can reflect endophthalmitis, inflammation or raised pressure.
Also, severe pain and reduced vision need same-day review (see acute postoperative endophthalmitis).
Red Eye in Children
Most pediatric red eyes are infectious conjunctivitis or allergy.
Also, consider trauma, foreign body and uveitis in children with arthritis (see juvenile idiopathic arthritis uveitis).
Red Eye and Systemic Disease
Scleritis may accompany rheumatoid arthritis and granulomatosis with polyangiitis.
Also, uveitis can accompany spondyloarthropathy and inflammatory bowel disease.
Because systemic disease changes management, ask about joint pain, back pain and bowel symptoms.
Safe Use of Topical Treatment
Prescribe lubricants for mild cases and avoid steroids without an examination.
Also, warn patients not to use leftover drops.
Follow-Up for the Red Eye
Tell the patient to return if pain or blur develops or if the eye is not better in several days.
Also, document visual acuity at each visit.
Using Visual Acuity as a Vital Sign
Visual acuity is the key measurement in every red eye.
A drop in acuity means that the cornea, the anterior chamber or the pressure is involved.
Also, record acuity before you instill any drops.
Therefore, make acuity the first step in your routine.
Documentation That Protects Patients
Write down acuity, pupils, staining pattern and the plan.
Also, record the safety-net advice that you gave.
Because red eyes can change quickly, clear notes help the next clinician.
Thinking in Layers From Outside In
Work from the lids to the conjunctiva, then the cornea, the anterior chamber and the lens.
Each layer has its own set of causes and signs.
Also, the pupil and the pressure tell you about deeper structures.
Because a systematic approach reduces misses, repeat the same order at every visit.
Finally, write down what you excluded as well as what you found.
For the latest studies, see the PubMed results for red eye.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Leibowitz HM. The red eye. N Engl J Med. 2000;343:345-351.
- Mahmood AR, Narang AT. Diagnosis and management of the acute red eye. Emerg Med Clin North Am. 2008;26:35-55.
- Cronau H, Kankanala RR, Mauger T. Diagnosis and management of red eye in primary care. Am Fam Physician. 2010;81:137-144.
- Varu DM, Rhee MK, Akpek EK, et al. Conjunctivitis Preferred Practice Pattern. Ophthalmology. 2019;126:P94-P169.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.