A toxoplasmosis chorioretinal scar is far more than a static, healed marker of past infection, since the encysted parasite responsible for it remains alive within the scar indefinitely, capable of reactivating at any point over a patient’s lifetime, and recognizing the fundus pattern that signals an active recurrence, a fresh lesion appearing right at the edge of an old, pigmented scar, is central to prompt diagnosis when this happens.
Why the Old Scar Matters So Much
Ocular toxoplasmosis is caused by the parasite Toxoplasma gondii, and unlike many infectious causes of chorioretinitis, the organism is not fully cleared after the initial infection resolves; instead, it persists in a dormant, encysted form within the old chorioretinal scar, which is why recurrence characteristically occurs adjacent to a pre-existing scar rather than as an entirely new lesion appearing in a previously unaffected area of retina.
Appearance of the Old, Inactive Scar
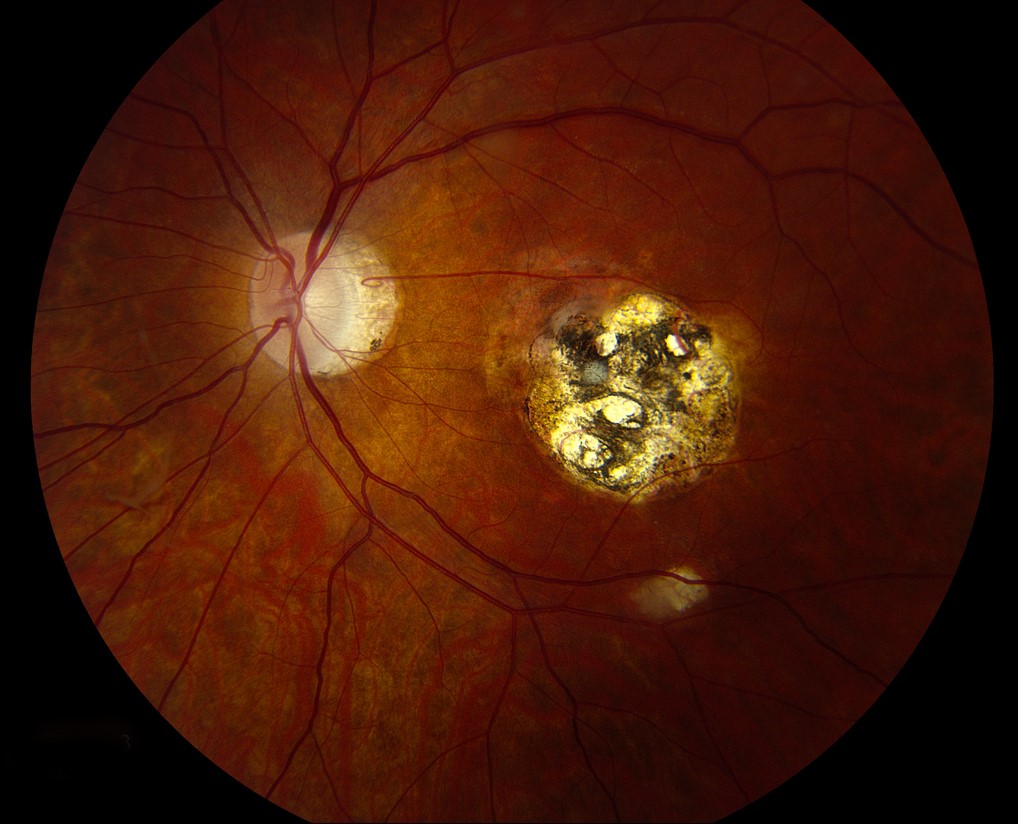
A healed toxoplasmosis scar typically appears as a sharply demarcated, atrophic chorioretinal lesion with a pigmented, often heavily pigmented, border, and variable size depending on the extent of the original episode of active infection, most classically located near the macula, though lesions can occur elsewhere in the fundus as well.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteThe Classic Sign of Reactivation
Active recurrent toxoplasmosis retinochoroiditis classically presents as a fresh, fluffy, yellow-white focus of retinitis appearing immediately adjacent to the border of an old, pigmented scar, a pattern often described using the vivid clinical phrase “headlight in the fog,” referring to the appearance of the new, hazy white lesion glowing against the backdrop of overlying vitreous haze from the accompanying inflammatory reaction.
- Prominent vitritis typically accompanies the active lesion, sometimes severe enough to significantly obscure the view of the fundus details, which is itself part of what gives the “fog” component of the classic description
- The active lesion is typically smaller than the original scar, representing a more limited area of new, active infection at the margin of the old site
Congenital Versus Acquired Toxoplasmosis
- Congenital toxoplasmosis, acquired transplacentally from maternal infection during pregnancy, often produces the most extensive, sometimes bilateral, macular scarring, and affected individuals face a lifetime risk of recurrent episodes, often beginning in the second or third decade of life
- Acquired toxoplasmosis, from postnatal infection, can also cause chorioretinitis, with the same lifelong risk of recurrence at the site of any resulting scar
Clinical Evaluation of a Suspected Recurrence
- Dilated fundus examination specifically assessing for a fresh, fluffy white lesion at the margin of a known or newly discovered pigmented chorioretinal scar
- Assessment of vitreous haze and inflammation, which both supports the diagnosis and affects the quality of the fundus view obtained
- A history of prior episodes, or, in a patient with no known history, assessment for evidence of a prior scar consistent with congenital or previously unrecognized toxoplasmosis
- Serologic testing for Toxoplasma antibodies supports the diagnosis, though a positive result mainly confirms prior exposure and does not independently confirm that a currently active lesion is caused by toxoplasmosis, so serology is interpreted together with the classic clinical appearance
Management
Treating Active Recurrence
Active toxoplasmosis retinochoroiditis threatening vision, particularly lesions near the macula, optic nerve, or major vascular arcades, or associated with significant vitritis, is treated with systemic antiparasitic therapy, classically pyrimethamine and sulfadiazine with folinic acid supplementation, or alternative regimens depending on patient tolerance and other factors, generally continued for a defined course of several weeks.
Systemic corticosteroids are often added once antiparasitic coverage is established, to help control the intense inflammatory response, though corticosteroids are never used as monotherapy without concurrent antiparasitic treatment given the risk of allowing unchecked parasitic proliferation.
Small, Peripheral Lesions
Small lesions in the peripheral retina, away from the macula, optic nerve, and major vessels, and without significant vitritis, may sometimes be observed rather than actively treated, given their more limited threat to central vision, though this decision is individualized based on lesion location and severity.
Long-Term Considerations
Because the parasite remains dormant within the scar indefinitely, every patient with a known toxoplasmosis chorioretinal scar carries a lifelong risk of recurrence, and education about symptoms of a new episode, including new floaters, blurred vision, or photophobia, supports prompt recognition and treatment of future recurrences.
Prognosis
Prognosis depends heavily on lesion location, with macular or optic-nerve-involving lesions carrying the greatest risk of permanent central visual loss, while peripheral lesions, even with recurrence, more often preserve good central vision.
With prompt recognition of the characteristic “headlight in the fog” appearance and timely antiparasitic and anti-inflammatory treatment, many recurrences resolve with reasonable preservation of vision, though each episode carries some risk of adding to the cumulative area of chorioretinal scarring.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Holland GN. Ocular toxoplasmosis: a global reassessment. Part I: epidemiology and course of disease. Am J Ophthalmol. 2003;136:973-988.
- Holland GN. Ocular toxoplasmosis: a global reassessment. Part II: disease manifestations and management. Am J Ophthalmol. 2004;137:1-17.
- Bosch-Driessen LH, Berendschot TT, Ongkosuwito JV, Rothova A. Ocular toxoplasmosis: clinical features and prognosis of 154 patients. Ophthalmology. 2002;109:869-878.
- Butler NJ, Furtado JM, Winthrop KL, Smith JR. Ocular toxoplasmosis II: clinical features, pathology and management. Clin Exp Ophthalmol. 2013;41:95-108.
Test yourself
A few questions straight from this article.
-
Why does ocular toxoplasmosis typically recur adjacent to an old chorioretinal scar?
Toxoplasma gondii is not cleared after the first infection; it survives in a dormant encysted form inside the old scar, so recurrence appears at the scar edge rather than in untouched retina. -
A healed toxoplasmosis chorioretinal scar characteristically has which appearance?
The healed lesion is a sharply demarcated atrophic chorioretinal scar with an often heavily pigmented border, classically near the macula though it can occur elsewhere. -
Which fundus pattern signals reactivation of toxoplasmosis retinochoroiditis?
Recurrence appears as a fresh, fluffy, yellow-white focus of retinitis immediately beside the pigmented scar, glowing through vitreous haze in the pattern called headlight in the fog. -
How does an active recurrent toxoplasmosis lesion usually compare in size with the old scar?
The active lesion is typically smaller than the original scar, representing a more limited area of new infection at the margin of the old site. -
In congenital toxoplasmosis, recurrent ocular episodes often begin in which period of life?
Congenital toxoplasmosis, acquired transplacentally, often causes extensive and sometimes bilateral macular scarring, with recurrences frequently starting in the second or third decade. -
What does a positive Toxoplasma serology contribute when active retinochoroiditis is suspected?
A positive titre mainly documents past exposure and cannot by itself prove that a current lesion is toxoplasmic, so serology is read alongside the classic fundus appearance. -
Which systemic regimen is classically used for sight-threatening toxoplasmosis retinochoroiditis?
Lesions near the macula, optic nerve, or major arcades, or with marked vitritis, are treated with systemic antiparasitic therapy, classically pyrimethamine and sulfadiazine plus folinic acid, for a defined course of several weeks. -
What rule governs systemic corticosteroid use in active ocular toxoplasmosis?
Steroids help control the intense inflammation but are never given as monotherapy, because without antiparasitic cover the parasite can proliferate unchecked. -
Which active toxoplasmosis lesions may sometimes be observed rather than treated?
Small lesions well away from the macula, optic nerve, and major vessels, without marked vitritis, pose a limited threat to central vision and may be observed, decided case by case. -
What most strongly determines visual prognosis in recurrent ocular toxoplasmosis?
Macular or optic-nerve lesions carry the greatest risk of permanent central visual loss, while peripheral lesions more often preserve good central vision even when they recur.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.