Diabetic retinopathy screening intervals vary by diabetes type, duration, retinopathy grade, and control.
Annual screening is the traditional standard, but evidence supports longer intervals for low-risk patients.
Choosing the right interval balances safety, cost, and access.
Standard Recommendations for Diabetic Retinopathy Screening Intervals
The American Diabetes Association advises an eye examination within five years of diagnosis in type 1 diabetes.
In type 2 diabetes, the first examination should occur at diagnosis.
If there is no retinopathy and glycemia is well controlled, repeat every one to two years.
Solomon and colleagues summarized these recommendations in the ADA position statement.
Pregnancy and Diabetic Retinopathy Screening Intervals
Pregnancy accelerates retinopathy, so examine women with diabetes before or early in pregnancy.
Then repeat once per trimester and again within a year after delivery (see diabetic retinopathy in pregnancy).
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteLonger Diabetic Retinopathy Screening Intervals
Agardh and Tababat-Khani proposed three-year intervals for people with type 2 diabetes and no retinopathy.
The English national program moved toward two-year intervals for low-risk patients after modeling studies.
Scanlon described these programs and the way risk categories drive the interval.
The risk of sight-threatening disease in the interval is low for people with no retinopathy and good control.
Shorter Diabetic Retinopathy Screening Intervals
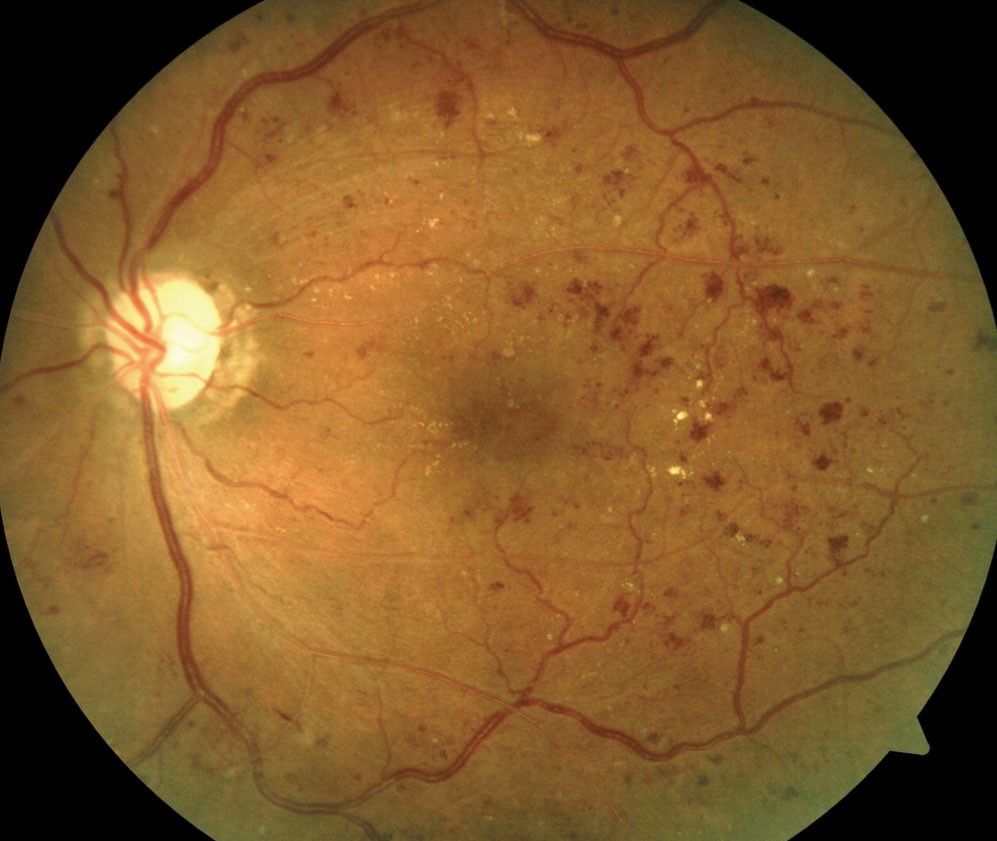
- Moderate or worse nonproliferative retinopathy, at 3 to 6 months
- Proliferative disease or macular edema, with prompt treatment and close review
- Poor glycemic or blood pressure control
- Rapid improvement in glycemia, which may worsen retinopathy temporarily
Examine more often when risk factors cluster (see proliferative diabetic retinopathy).
Technology and Diabetic Retinopathy Screening Intervals
Telemedicine and artificial intelligence can extend screening to underserved areas.
Wide-field imaging may find peripheral lesions that change the risk grade (see AI diabetic retinopathy screening).
Programs need clear referral pathways, since screening alone does not save vision.
Practical Points on Diabetic Retinopathy Screening Intervals
Grade each examination, and set the interval from the grade and risk profile.
Document the date of the next review, and send reminders.
Keep adherence high, since missed appointments cause most late presentations.
An Example Case
A 52-year-old man with type 2 diabetes for eight years has no retinopathy on two consecutive annual exams.
His hemoglobin A1c is 6.8 percent, and his blood pressure is controlled.
His clinician moves him to a two-year interval based on the risk grade.
At the next exam, he has no retinopathy, and the schedule continues.
Questions Patients Ask
Patients ask why the interval is longer than last time, and the answer is that low-risk patients have a very small chance of problems in the first year.
They also ask whether they should call if vision changes, and they should.
Because patients may relax too much, stress that sudden changes need prompt review.
Pitfalls to Avoid
- Using a long interval without a validated grade
- Forgetting to examine after rapid improvement in glycemic control
- Delaying the first examination in type 2 diabetes
- Failing to track patients who miss appointments
Looking Ahead
Risk calculators that combine glycemia, blood pressure, duration, and prior grades may personalize intervals.
Also, artificial intelligence may extend screening at low cost.
Therefore, individualized schedules will likely replace fixed intervals.
Practical Points
Define the grade using a validated scheme at each visit.
Then set the next date and document it in the record.
Also send reminders by message or phone.
Special Situations
Pregnancy, puberty, and cataract surgery may speed up retinopathy.
Patients on rapidly lowering therapy may worsen temporarily.
Therefore, shorten the interval in these situations.
Equity and Access
Many patients with diabetes never receive eye exams.
Community programs, mobile cameras, and primary care imaging expand coverage.
Because outcomes depend on follow-up, invest in recall systems.
Risk Calculators and Personalized Intervals
Some programs use algorithms that combine prior grades, glycemic control, and duration.
These tools can place patients in low, medium, and high-risk groups.
Because the interval then follows the individual risk, resources go where they are needed.
However, the tools need local validation before use.
Communicating the Plan to Patients
Explain why the interval is chosen and what symptoms need earlier review.
Then give written instructions and a reminder date.
Also involve the primary care team, so that glycemic and blood pressure control stay in focus.
Summary
Choose the interval from the grade, the type of diabetes, and control.
Then document the next date and send reminders.
Because missed visits cause most late presentations, track attendance.
For the latest studies, see the PubMed results for diabetic retinopathy screening intervals.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Solomon SD, Chew E, Duh EJ, et al. Diabetic retinopathy: a position statement by the American Diabetes Association. Diabetes Care. 2017;40:412-418.
- Agardh E, Tababat-Khani P. Adopting 3-year screening intervals for sight-threatening retinal vascular lesions in type 2 diabetes subjects without retinopathy. Diabetes Care. 2011;34:1318-1319.
- Scanlon PH. The English National Screening Programme for diabetic retinopathy 2003-2016. Acta Diabetol. 2017;54:515-525.
- Flaxel CJ, Adelman RA, Bailey ST, et al. Diabetic retinopathy preferred practice pattern. Ophthalmology. 2020;127:P66-P145.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.