Blue cone monochromacy (BCM) is a rare X-linked recessive cone disorder in which only the blue (S) cones and the rods function.
It presents in infancy with poor vision, nystagmus, and light sensitivity, and the fundus is often normal, which delays the diagnosis.
Recognizing it matters for genetic counselling and, increasingly, for gene therapy trials.
What Is Blue Cone Monochromacy?
The disorder results from loss of function of the long-wavelength (L) and medium-wavelength (M) opsin genes on the X chromosome.
The cause may be a deletion of the locus control region that regulates both genes, or a mutation that inactivates the L and M opsin genes.
In males with the disorder, the L and M cones are nonfunctional, and vision depends on S cones, which are few and sparse in the fovea, and on rods.
Female carriers are usually asymptomatic, but they may have mild abnormalities on testing.
Clinical Features
- Reduced central vision, usually between 20/80 and 20/200, and stable in childhood
- Pendular nystagmus in infancy, which often decreases with age
- Photophobia, particularly in bright light
- Myopia, which can be high, and astigmatism
- Severe color vision deficiency, with a characteristic confusion pattern
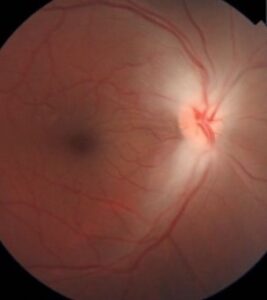
- A normal fundus in children, and later macular changes in some adults
A patient with BCM can have better vision at dusk, because the rods are less affected by the lack of cone function.
Progressive macular atrophy has been described in older individuals.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteDifferential Diagnosis
- Rod monochromacy (achromatopsia): autosomal recessive, with absence of all cone function, more severe photophobia, and a flat S-cone response (see achromatopsia)
- Cone and cone-rod dystrophy: progressive loss and a macular change (see cone-rod dystrophy)
- Albinism: iris transillumination and foveal hypoplasia (see albinism and foveal hypoplasia)
- Infantile nystagmus syndrome and Leber congenital amaurosis
Investigations
The electroretinogram is key: the photopic, cone-driven response is absent or severely reduced, the rod response is normal, and a specific S-cone ERG shows a preserved response (see electroretinography).
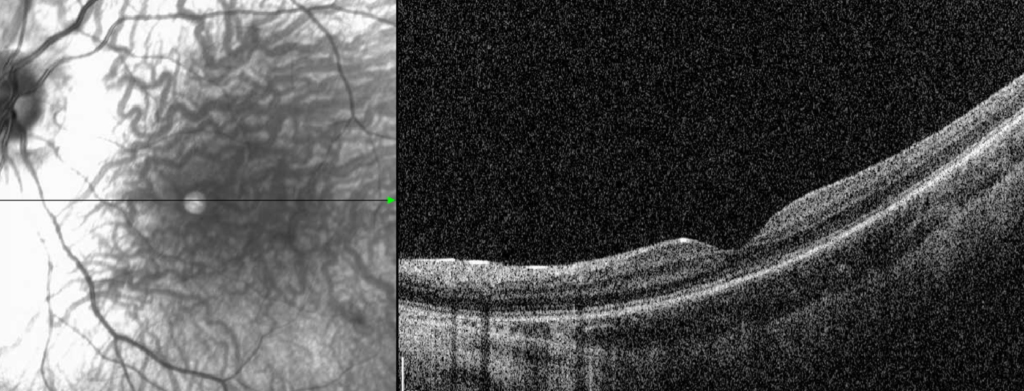
OCT may show a preserved or slightly disrupted ellipsoid zone in the fovea, with a normal foveal contour in many patients.
Color testing shows a tritan-like pattern, and the anomaloscope test is abnormal.
Molecular testing for the L and M opsin gene cluster confirms the diagnosis and provides the basis for family counselling.
Management
No treatment cures the condition, so care aims to optimize vision and comfort.
Correct refractive error, and consider tinted or filter lenses, or a red-tinted contact lens, to reduce glare.
Low-vision services and educational support help children to use their remaining vision.
Genetic counselling should explain the X-linked pattern, in which the sons of a carrier have a 50 percent chance of being affected.
Gene therapy trials for the disease have been undertaken, and families can be told about research opportunities (see gene therapy for inherited retinal disease).
Diagnosis in Practice
The history of poor vision since infancy, nystagmus, photophobia, and a normal-appearing fundus in a boy should raise the possibility of a cone disorder, and the family history may show affected maternal relatives.
The first test is usually the ERG, performed by a center that can include a flicker test and an S-cone stimulus.
In infants, the ERG can be performed under sedation, and the results guide the genetic work-up.
Genetic testing identifies the cause and allows the family to be counselled, and it should be considered a routine step in the diagnostic pathway.
Color Vision Findings
Patients with BCM can often distinguish blue from yellow at a particular level of brightness, but they confuse red, orange, yellow, and green.
They use brightness cues, and their performance on color tests is erratic.
Tests such as the Farnsworth D-15 and the anomaloscope show a typical pattern, but the diagnosis does not depend on them.
Visual Function and Day-to-Day Life
Photophobia is a daily problem, and tinted lenses with a red or dark filter, a wide-brimmed hat, and shaded environments help.
Children benefit from large print, high-contrast materials, and assistance in school.
Many patients are comfortable in dim light, and they perform better in the evening.
Nystagmus usually improves with age, and a head posture at the null point may be used.
Research and Gene Therapy
Gene therapy approaches to restore L and M cone function are in early stages, and some trials in patients with BCM have been conducted.
Families should be put in touch with registries and specialist centers if they wish to participate.
Remind families that natural history data matter, and that regular follow-up with imaging and visual function tests contributes to understanding the condition.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Nathans J, Davenport CM, Maumenee IH, et al. Molecular genetics of human blue cone monochromacy. Science. 1989;245:831-838.
- Michaelides M, Johnson S, Simunovic MP, et al. Blue cone monochromatism: a phenotype and genotype assessment with evidence of progressive loss of cone function in older individuals. Eye. 2005;19:2-10.
- Ryan SJ, Schachat AP, Wilkinson CP, et al, eds. Retina. 6th ed. Elsevier; 2018.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
Which photoreceptors remain functional in blue cone monochromacy?
Blue cone monochromacy is an X-linked recessive cone disorder in which only the blue (S) cones and the rods function, so vision depends on sparse foveal S cones and on rods. -
Loss of function of which genes causes blue cone monochromacy?
The disorder follows loss of function of the long-wavelength (L) and medium-wavelength (M) opsin genes on the X chromosome, either by deletion of the locus control region that regulates both or by an inactivating mutation. -
What central visual acuity range is typical in blue cone monochromacy?
Central vision in blue cone monochromacy is usually reduced to between 20/80 and 20/200, and it is stable through childhood. -
What is the characteristic electroretinogram pattern in blue cone monochromacy?
The electroretinogram is the key test: the photopic cone-driven response is absent or severely reduced, the rod response is normal, and a specific S-cone stimulus shows a preserved response. -
Which feature separates rod monochromacy from blue cone monochromacy?
Rod monochromacy (achromatopsia) is autosomal recessive with absence of all cone function and a flat S-cone response, whereas blue cone monochromacy is X-linked and retains an S-cone response. -
What is the mainstay of management for blue cone monochromacy?
No treatment cures the condition, so care optimizes vision and comfort: correct the refractive error and consider tinted filter lenses or a red-tinted contact lens to reduce glare, with low-vision and educational support. -
In blue cone monochromacy, what is the chance that a carrier mother's son is affected?
Genetic counselling should explain the X-linked pattern, in which the sons of a carrier have a 50 percent chance of being affected; female carriers are usually asymptomatic. -
What retinal change has been described in older individuals with blue cone monochromacy?
The fundus is normal in children, but macular changes appear in some adults, and progressive macular atrophy has been described in older individuals. -
What does OCT typically show in blue cone monochromacy?
OCT may show a preserved or only slightly disrupted ellipsoid zone at the fovea, with a normal foveal contour in many patients. -
Why does a patient with blue cone monochromacy often see better at dusk?
Because the rods are spared by the loss of L and M cone function, patients are comfortable in dim light and often perform better at dusk and in the evening.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.