
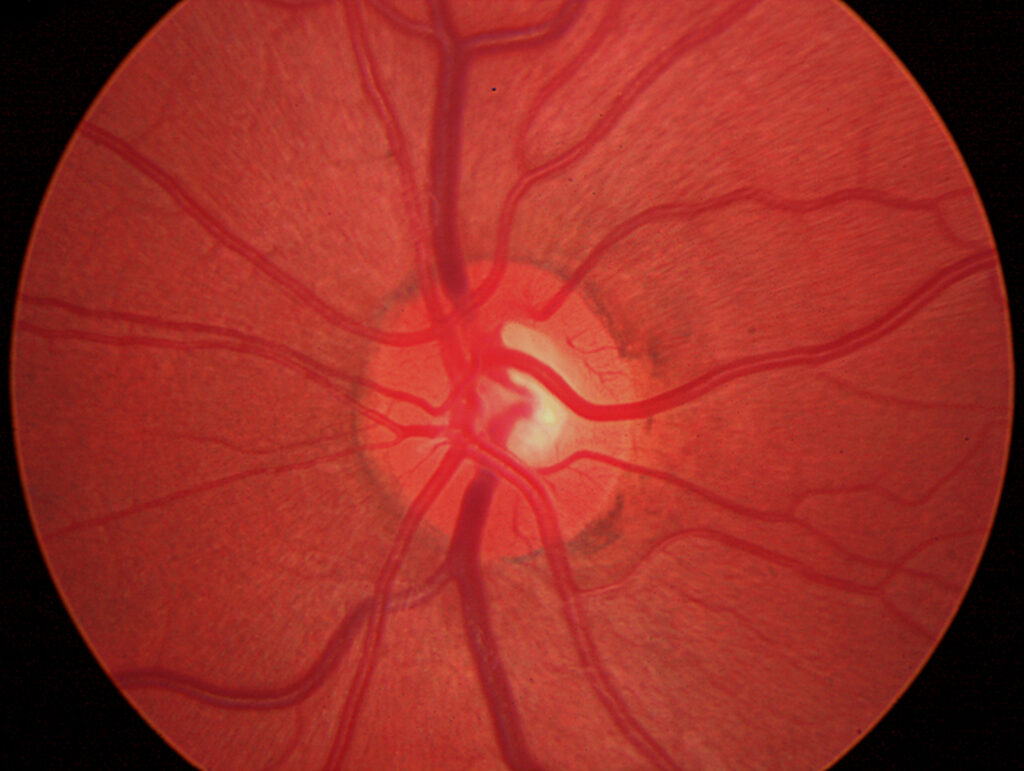
Spontaneous venous pulsation is the rhythmic narrowing and filling of the central retinal vein as it leaves the optic disc.
It occurs with each heartbeat, and clinicians look for it during fundus examination of patients with suspected raised intracranial pressure.
The sign is useful, but it has limits that every examiner should know.
Why Spontaneous Venous Pulsation Occurs
Intraocular pressure squeezes the vein as it passes through the lamina cribrosa, while the cerebrospinal fluid pressure acts on the vein within the optic nerve sheath.
During systole, the intraocular pressure rises briefly, and the vein collapses at the disc.
The pulsation appears when intracranial pressure is lower than the peak intraocular pressure.
Therefore, it reflects the balance between the two pressures, not the absolute intracranial pressure (see papilledema).
How to Look for Spontaneous Venous Pulsation
Use a direct ophthalmoscope without dilation, since a small pupil gives stable viewing.
Focus on the main vein at the disc surface, where it emerges from the cup.
Observe for 10 to 20 seconds, and watch for rhythmic narrowing and widening in time with the pulse.
A video recording or slit lamp lens may help when the view is difficult.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteHow Common Spontaneous Venous Pulsation Is
Levin found pulsation in most normal subjects, and absent pulsation in about one in ten.
Other studies report varying rates, from about two thirds to more than 90 percent.
It is more often present in young people, and it may appear and disappear in the same person.
Therefore, absence on a single examination has limited meaning (see pseudopapilledema and papilledema).
Interpreting Spontaneous Venous Pulsation
Presence suggests that the cerebrospinal fluid pressure is below a threshold, often cited as around 190 mm of water.
Jacks and Miller reviewed the evidence and concluded that visible pulsation argues against high pressure at that moment.
Absence does not prove raised pressure, since many normal eyes lack it.
Use the sign together with the disc appearance, the symptoms, and imaging (see is every optic disc swelling papilledema).
Limits of Spontaneous Venous Pulsation
- Poor view, hazy media, or small pupils
- Variation over time in the same patient
- Pulsation may be present in mild disease with intermittent pressure rises
- Medications and eye pressure changes alter the pattern
Wong and White noted that the test is a clinical tool and not a substitute for lumbar puncture.
Practical Use
Check pulsation when you suspect papilledema, and record whether it is present or absent.
Combine the finding with the history, the visual fields, and OCT of the disc.
Order imaging and lumbar puncture when symptoms or other signs suggest raised intracranial pressure.
An Example Case
A 28-year-old woman has headaches and transient visual obscurations, and her acuity is 20/20.
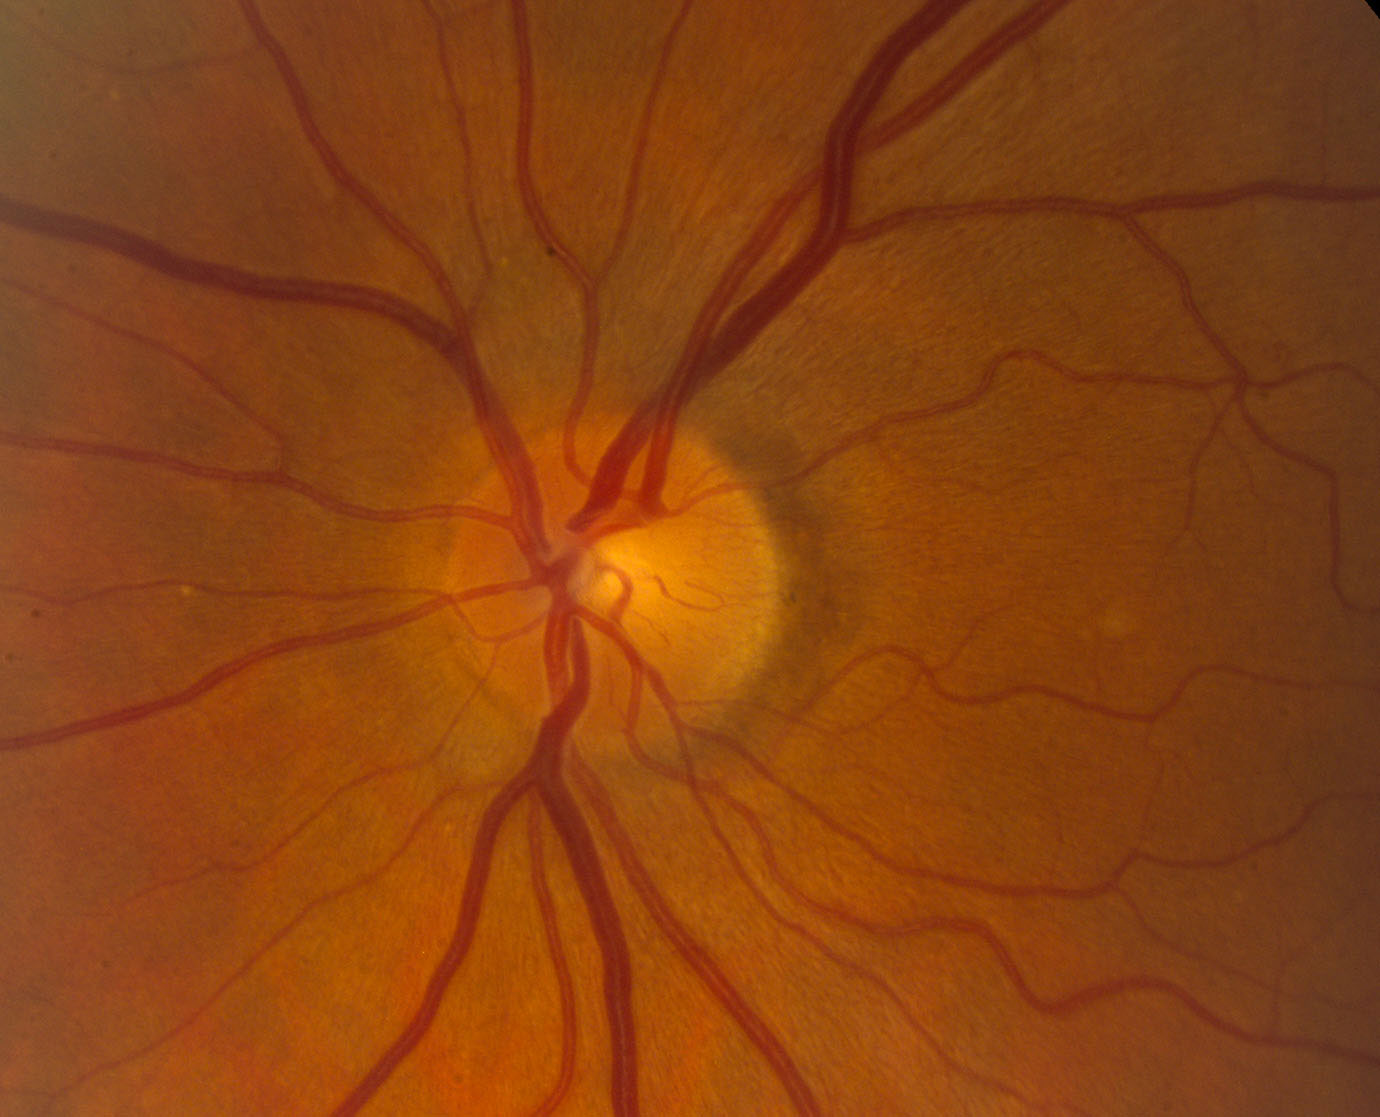
The discs look mildly swollen, and spontaneous venous pulsation is absent in both eyes.
MRI and venography are normal, and the opening pressure on lumbar puncture is 36 cm of water.
The diagnosis is idiopathic intracranial hypertension, and she starts acetazolamide.
After treatment, the disc swelling resolves, and pulsations reappear in one eye.
Questions Patients Ask
Patients ask whether the pulsation can be seen by themselves, and it cannot, because it needs an ophthalmoscope.
They also ask whether the sign proves high pressure, and the honest answer is that it does not.
Because many people lack the sign, explain that it is only one clue.
Pitfalls to Avoid
- Treating absent pulsation as proof of papilledema
- Overlooking pulsation that is visible only on the main trunk
- Checking after dilation with a poor view
- Ignoring the symptoms when pulsation is present
Looking Ahead
Researchers study automated detection of pulsation with video and OCT.
Also, noninvasive measures of intracranial pressure may complement the sign.
However, no test replaces the history and the full examination.
Practical Points
Record pulsation in the chart as present, absent, or not seen because of a poor view.
Then repeat the check at follow-up visits, since changes may help.
Also pair the finding with OCT of the retinal nerve fiber layer and the visual field.
Teaching Tips
Practice on healthy colleagues to learn how pulsation looks.
Use a brief, steady gaze on the vein at the disc margin.
Because the movement is subtle, patience matters.
Documenting the Finding
Write the result in the chart in a standard way.
Then include the method, such as direct ophthalmoscopy.
Also note the pupil size, since a small pupil may limit the view.
Because the sign changes over time, record the date and the time of the examination.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Levin BE. The clinical significance of spontaneous pulsations of the retinal vein. Arch Neurol. 1978;35:37-40.
- Jacks AS, Miller NR. Spontaneous retinal venous pulsation: aetiology and significance. J Neurol Neurosurg Psychiatry. 2003;74:7-9.
- Wong SH, White RP. The clinical validity of the spontaneous retinal venous pulsation. J Neuroophthalmol. 2013;33:17-20.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 5: Neuro-Ophthalmology. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.


