Dorsal midbrain syndrome, also called Parinaud syndrome, is a cluster of eye signs that localize a lesion to the upper midbrain and the posterior commissure.
The classic findings are a supranuclear upgaze palsy, convergence-retraction nystagmus, eyelid retraction, and light-near dissociation of the pupils.
The cause may be a pineal tumor or hydrocephalus, so the finding requires prompt imaging.
What Is Dorsal Midbrain Syndrome?
The syndrome results from damage to the structures at the junction of the midbrain and the thalamus, including the posterior commissure and the rostral interstitial nucleus of the medial longitudinal fasciculus.
These centers generate vertical saccades and coordinate the pupil light reflex, so the signs occur together.
The term should not be confused with Parinaud oculoglandular syndrome, which has the same eponym but is an infectious conjunctivitis (see Parinaud oculoglandular syndrome).
Clinical Features
- Upgaze palsy: reduced voluntary upward saccades and pursuit, with preserved Bell phenomenon and vestibulo-ocular reflex in the early stage
- Convergence-retraction nystagmus: the eyes jerk toward each other and retract into the orbit on attempted upward saccades
- Eyelid retraction (Collier sign): the lids appear raised and the patient has a staring look
- Light-near dissociation: large, mid-dilated pupils that react poorly to light and better to near
- Accommodation spasm or paralysis, and skew deviation: in some patients
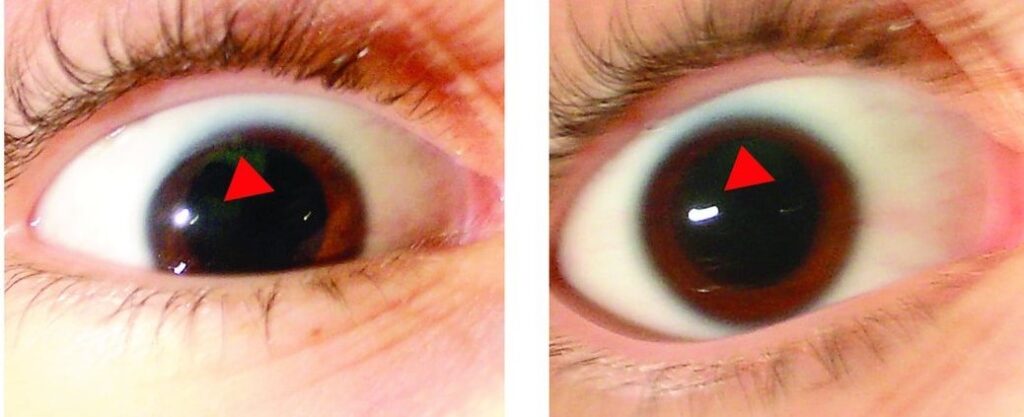
Infants with hydrocephalus may show the “setting sun” sign, in which the eyes are deviated downward and the sclera is visible above the iris.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteCauses
- Pineal region tumors: germinoma, pineocytoma, and other germ cell tumors, usually in children and young adults
- Hydrocephalus: aqueductal stenosis or obstruction, with raised pressure
- Midbrain stroke or hemorrhage: often with other brainstem signs
- Demyelination, trauma, and vascular malformations
- Infection and inflammation: toxoplasmosis, tuberculosis, and neurosarcoidosis
In older adults, the commonest cause is a midbrain stroke, while in children and young adults tumors and hydrocephalus predominate.
Differential Diagnosis
- Progressive supranuclear palsy: a vertical gaze palsy with falls, and a downgaze predominance
- Thyroid eye disease: eyelid retraction with restrictive limitation of upgaze (see thyroid eye disease)
- Myasthenia gravis: fatigable weakness without pupil changes (see ocular myasthenia gravis)
- Internuclear ophthalmoplegia and other brainstem syndromes (see internuclear ophthalmoplegia)
- Pupillary disorders: Argyll Robertson and Adie pupils (see Argyll Robertson pupil and Adie tonic pupil)
Evaluation
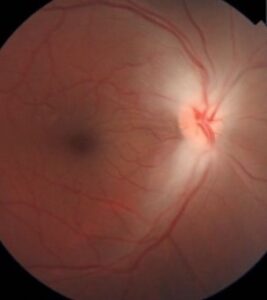
Examine the eye movements, the pupils, the lids, and the optic discs, because papilledema indicates raised intracranial pressure (see papilledema).
MRI of the brain with contrast and MR venography or angiography are the key investigations, and CT can be used if MRI is not available.
In a child or young adult with a pineal mass, check serum and cerebrospinal fluid tumor markers, such as alpha-fetoprotein and beta-human chorionic gonadotropin.
Management
Treatment is directed at the cause.
Hydrocephalus is relieved by shunting or third ventriculostomy, and the upgaze often improves after the pressure falls.
Pineal tumors need a neurosurgical and oncologic plan, and germinomas are radiosensitive and chemosensitive.
Ischemic and inflammatory lesions are treated by the neurology team.
Prisms, or surgery for a persistent vertical deviation, are options for residual diplopia once the condition is stable.
Explain to patients that the eye signs reflect a problem in the brain that needs urgent imaging, and that many causes are treatable.
Examining the Patient
Test the saccades and the pursuit in all directions, and compare upward with downward movement.
Ask the patient to follow a target upward, and then spin the head while the patient fixes on a target to test the vestibulo-ocular reflex, which will be intact in a supranuclear lesion.
Look for convergence-retraction nystagmus by using an optokinetic drum or a striped tape moving downward, which induces upward saccades.
Examine the pupils with a bright light and with a near target, and measure their size.
Pineal Tumors
A pineal mass may cause obstruction of the aqueduct and hydrocephalus, with headache, vomiting, and papilledema.
Germinomas are the most common tumor in this region, and they respond well to radiotherapy and chemotherapy.
Other germ cell tumors, pineal parenchymal tumors, and gliomas have different management.
A tissue diagnosis may be obtained by endoscopic biopsy at the time of third ventriculostomy.
Vascular and Inflammatory Causes
In an older patient with sudden onset of vertical gaze limitation, a midbrain infarct is likely, and the patient should be treated in a stroke pathway.
In a young woman with other neurologic signs, multiple sclerosis should be considered.
Sarcoidosis, tuberculosis, and toxoplasmosis can also affect the region, and tests for these should be part of the work-up when imaging does not show a tumor.
Prognosis
The prognosis depends on the cause: the signs often resolve when the hydrocephalus is treated, and they may persist when the lesion is destructive.
Follow the patient with serial examinations, and refer to rehabilitation for diplopia and for the reading difficulties that follow vertical gaze palsy.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Keane JR. The pretectal syndrome: 206 patients. Neurology. 1990;40:684-690.
- Liu GT, Volpe NJ, Galetta SL. Neuro-Ophthalmology: Diagnosis and Management. 3rd ed. Elsevier; 2019.
- Miller NR, Newman NJ, Biousse V, Kerrison JB, eds. Walsh and Hoyt’s Clinical Neuro-Ophthalmology. 6th ed. Lippincott Williams and Wilkins; 2005.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 5: Neuro-Ophthalmology. AAO; current edition.
Test yourself
A few questions straight from this article.
-
A lesion causing dorsal midbrain syndrome localizes to which structures?
Dorsal midbrain syndrome follows damage at the midbrain-thalamic junction, involving the posterior commissure and the rostral interstitial nucleus of the medial longitudinal fasciculus, which generate vertical saccades. -
What happens during convergence-retraction nystagmus?
On attempted upward saccades the eyes jerk toward each other and retract into the orbit, which is the characteristic convergence-retraction nystagmus of dorsal midbrain syndrome. -
Eyelid retraction in dorsal midbrain syndrome is known as which sign?
The eyelid retraction of dorsal midbrain syndrome is called Collier sign: the lids appear raised and the patient has a staring look. -
What do the pupils show in dorsal midbrain syndrome?
Light-near dissociation is classic: the pupils are large and mid-dilated, react poorly to light, and react better to a near target, because the lesion involves the centres coordinating the light reflex. -
Which sign may an infant with hydrocephalus and dorsal midbrain syndrome show?
Infants with hydrocephalus may show the setting sun sign, in which the eyes are deviated downward and sclera is visible above the iris. -
Which finding confirms that an upgaze palsy is supranuclear in origin?
In dorsal midbrain syndrome the Bell phenomenon and the vestibulo-ocular reflex are preserved early, so spinning the head while the patient fixates shows an intact reflex despite the voluntary upgaze palsy. -
What is the commonest cause of dorsal midbrain syndrome in an older adult?
In older adults the commonest cause is a midbrain stroke, whereas in children and young adults pineal region tumours and hydrocephalus predominate. -
Which tumour markers are checked in a young patient with a pineal mass?
In a child or young adult with a pineal mass, serum and cerebrospinal fluid tumour markers such as alpha-fetoprotein and beta-human chorionic gonadotropin should be measured alongside contrast MRI. -
Which feature points to progressive supranuclear palsy rather than dorsal midbrain syndrome?
Progressive supranuclear palsy also causes a vertical gaze palsy, but it comes with falls and a downgaze predominance, unlike the upgaze-predominant palsy of dorsal midbrain syndrome. -
How is dorsal midbrain syndrome caused by hydrocephalus managed?
Treatment is directed at the cause: hydrocephalus is relieved by shunting or third ventriculostomy, and the upgaze often improves once the pressure falls.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.