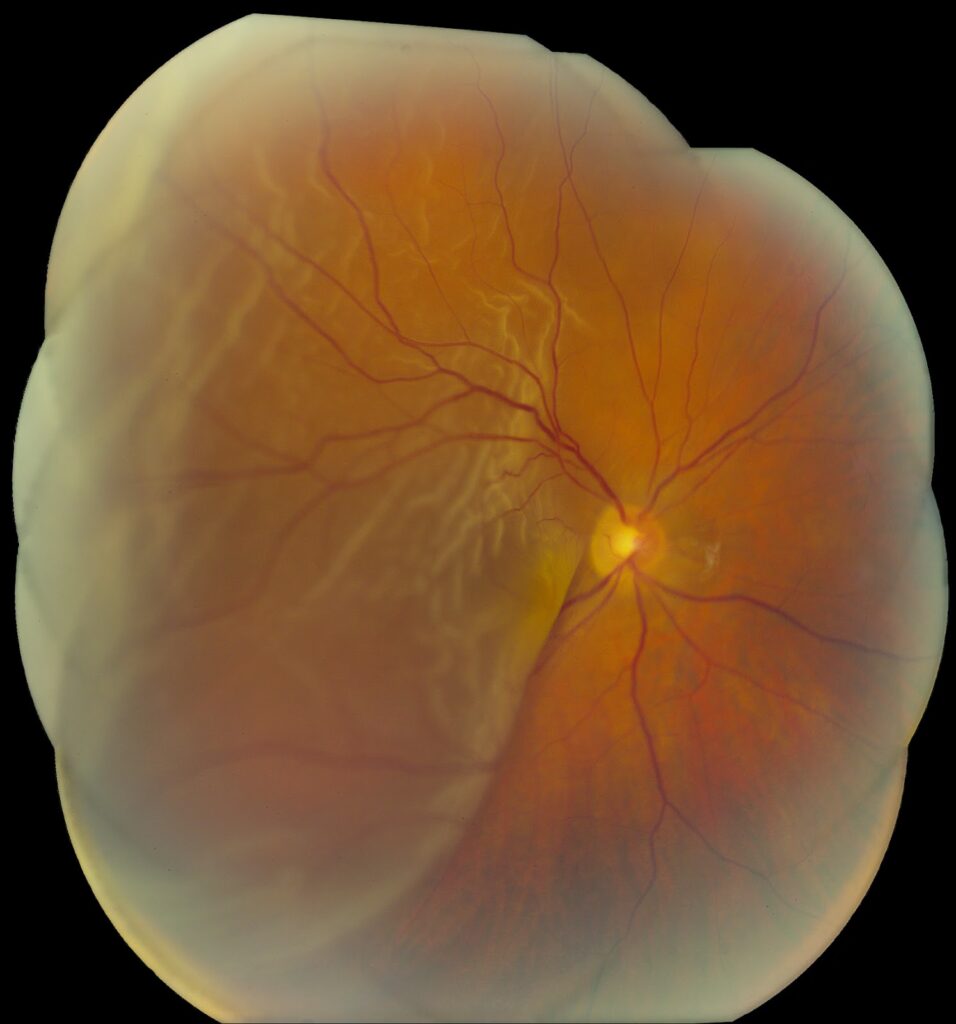
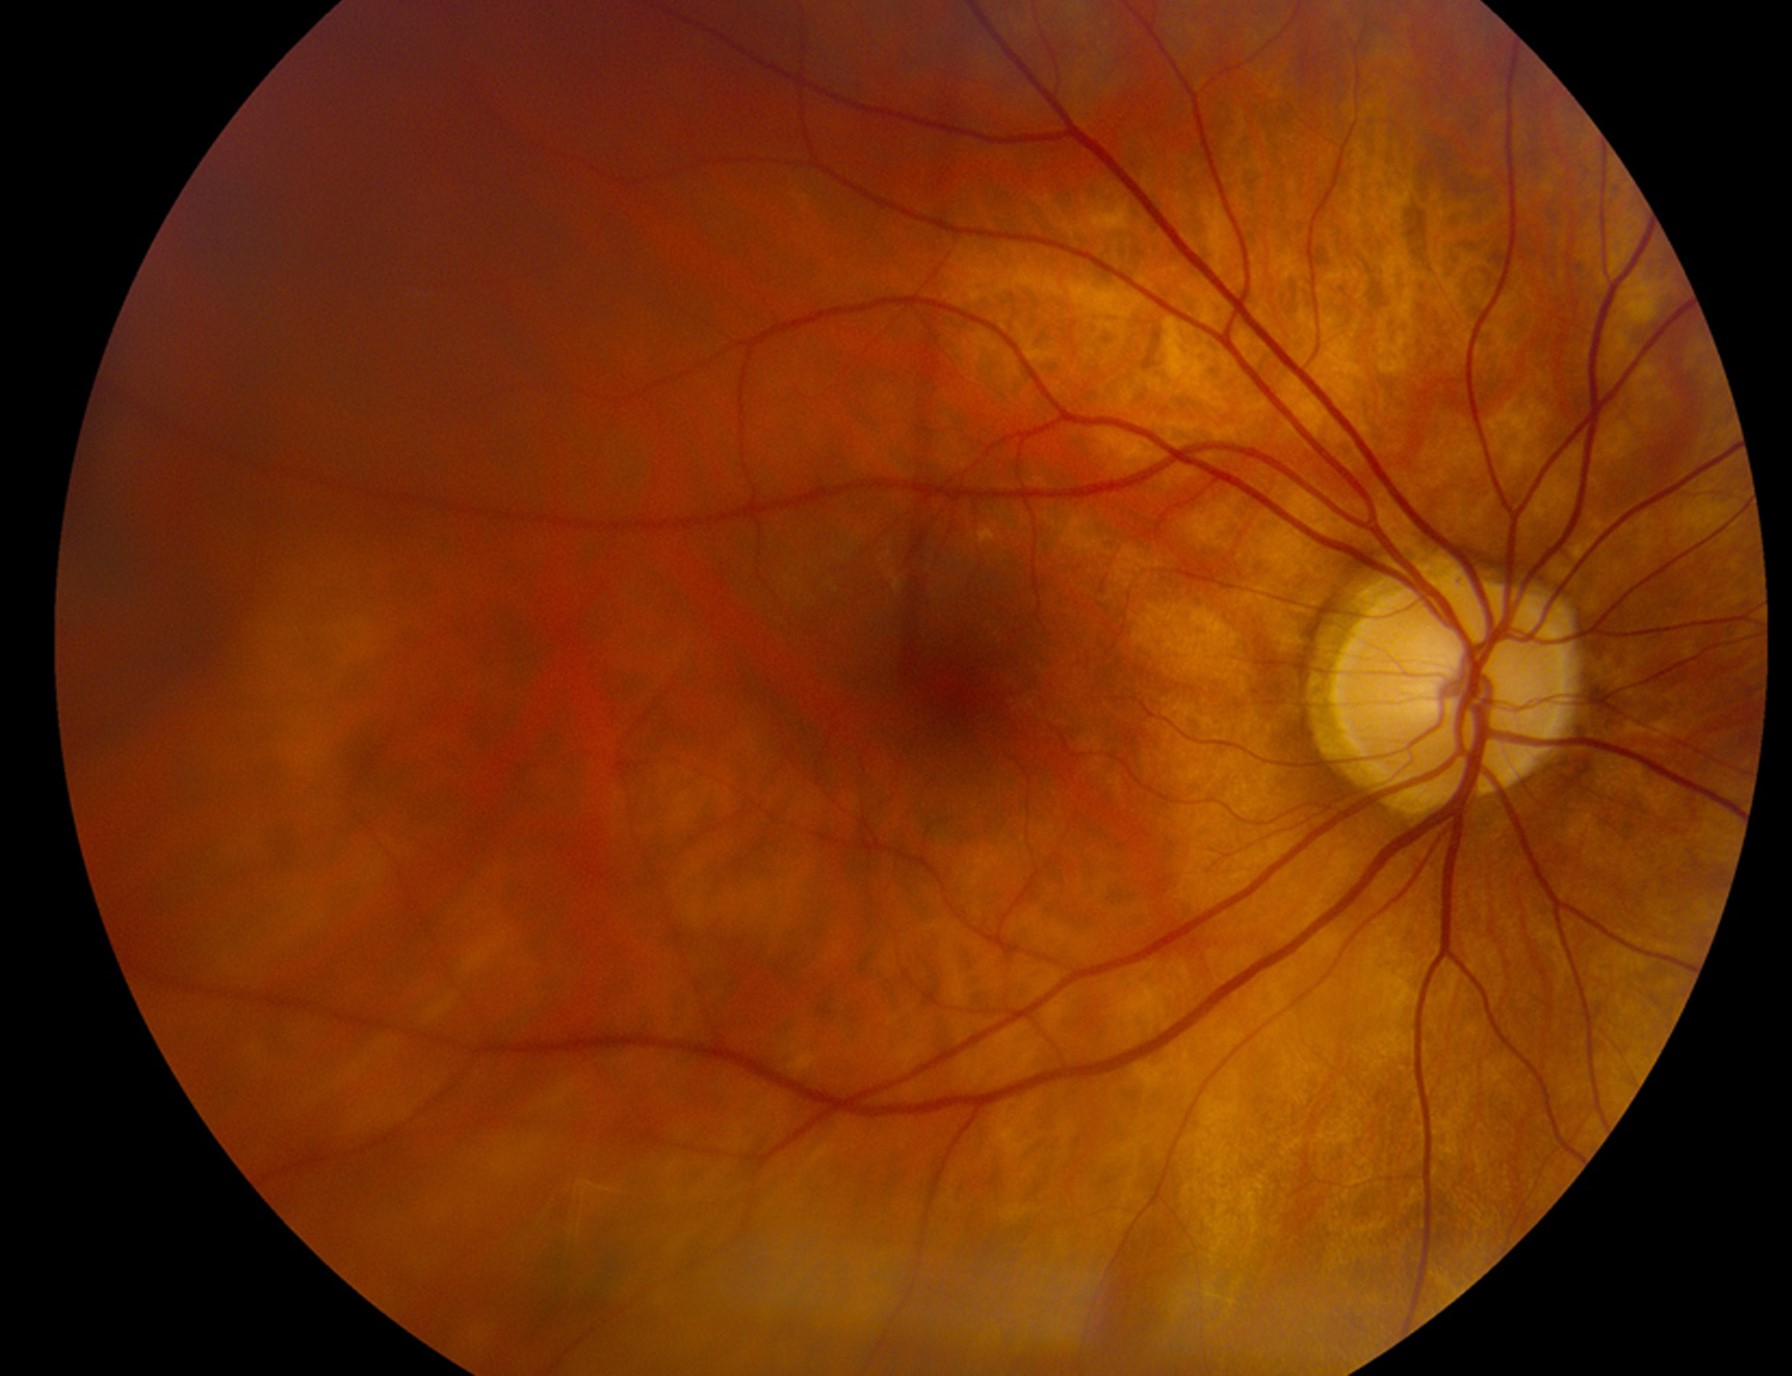
Macula-off retinal detachment is a rhegmatogenous detachment in which the fovea has separated from the retinal pigment epithelium.
Central acuity is reduced, and recovery after successful reattachment depends largely on how long the fovea stayed detached.
The clinical question is how fast to operate, and the answer is a balance between the evidence for early repair and the practical limits of the operating schedule.
What Is Macula-Off Retinal Detachment?
In a macula-on detachment, the central retina remains attached and the patient usually keeps good acuity, which makes the case more urgent to repair (see macula-on retinal detachment).
In a macula-off detachment, subretinal fluid has spread under the fovea, the photoreceptors lose contact with the retinal pigment epithelium, and they begin to degenerate.
Photoreceptor outer segments shorten, cells undergo apoptosis, and Müller cells and glia react in ways that can later form scar tissue.
The longer this state lasts, the more permanent the loss.
Even after the retina is reattached, the fovea may not return to normal, and some patients are left with distortion or reduced contrast.
Clinical Features
- A shadow or curtain in the peripheral field that progressed to include the center
- Reduced central acuity, with metamorphopsia once the retina is reattached
- A relative afferent pupillary defect in extensive detachments
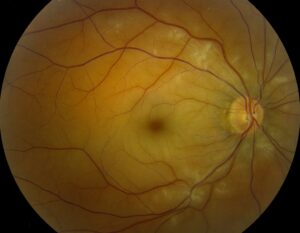
- A mobile, corrugated, opaque retina with a break, often a horseshoe tear in the superior periphery
- Lower intraocular pressure than the fellow eye in some cases
The history of when the central vision was lost is the most important piece of information for planning surgery, and the patient should be asked to be as precise as possible.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteWhat Determines Visual Recovery
The best-studied factor is the duration of foveal detachment.
Studies of buckle surgery have found that eyes operated within a few days of macular detachment recover better acuity on average than those operated after one to two weeks, with a gradual decline in outcome as time passes.
The data are not perfectly consistent, and some authors found little difference within the first week.
Other factors include the preoperative acuity, the height of the macular detachment, the patient’s age, the presence of proliferative vitreoretinopathy, and the surgical approach.
Eyes with a macular hole or an epiretinal membrane after surgery fare worse.
Timing of Surgery
Most surgeons aim to repair a recent macula-off detachment within a few days, often within 24 to 72 hours when logistics allow.
Patients with a macula-on detachment, or with a detachment threatening the macula, are prioritized over those who are already macula-off.
A macula-off detachment of more than a week or two is still repaired, but the surgeon should counsel the patient that central vision may not recover fully.
Posturing may reduce the progression of fluid toward the macula while the patient waits for surgery.
Surgical Options
The choice depends on the lens status, the number and position of the breaks, the amount of vitreous traction, and the surgeon’s experience.
- Pneumatic retinopexy: suitable for a single break or a cluster in the superior 8 clock hours in a phakic eye (see pneumatic retinopexy)
- Scleral buckle: often preferred in young, phakic patients with an attached vitreous (see scleral buckle surgery)
- Pars plana vitrectomy: frequently used in pseudophakic eyes and in complex cases (see pars plana vitrectomy)
Gas or silicone oil tamponade is chosen according to the extent of the disease and the ability of the patient to position.
After Surgery
Visual recovery is slow and can continue for six to twelve months.
OCT may show subretinal fluid for weeks after a gas procedure, and the integrity of the ellipsoid zone helps to predict the final acuity (see ellipsoid zone disruption).
Patients should be told that distortion and reduced contrast may persist even with a technically perfect repair.
Early review for redetachment, epiretinal membrane, and cataract, in phakic eyes treated with gas, is part of the follow-up.
Imaging Before and After Surgery
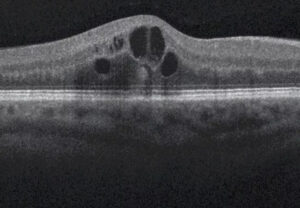
OCT of the macula in a macula-off detachment shows a neurosensory elevation with elongated and sometimes ragged photoreceptor outer segments.
Outer retinal folds, intraretinal cystic spaces, and a thin or absent foveal ellipsoid line are all unfavorable signs.
After repair, the recovery of the ellipsoid and interdigitation zones on OCT tracks closely with the recovery of acuity.
Persistent subretinal fluid after gas absorption usually resolves over weeks, and the clinician should avoid intervening too early.
What to Tell the Patient
Be honest about the uncertainty, because acuity cannot be predicted precisely at the first visit.
Most patients regain useful reading vision, and many reach 20/40 or better when the repair is early and no complications arise, but some are left with distortion or a central scotoma.
Explain that the fellow eye has a higher risk of a detachment, and that the symptoms to watch for are the same.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Ross WH. Visual recovery after macula-off retinal detachment. Eye. 2002;16:440-446.
- Hassan TS, Sarrafizadeh R, Ruby AJ, et al. The effect of duration of macular detachment on results after the scleral buckle repair of primary, macula-off retinal detachments. Ophthalmology. 2002;109:146-152.
- Ryan SJ, Schachat AP, Wilkinson CP, et al, eds. Retina. 6th ed. Elsevier; 2018.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
What defines a macula-off rhegmatogenous retinal detachment?
In a macula-off detachment subretinal fluid has spread under the fovea, so the photoreceptors lose contact with the retinal pigment epithelium and begin to degenerate. -
Why is a macula-on detachment prioritised over a macula-off detachment for surgery?
In a macula-on detachment the central retina is still attached and acuity is usually good, which makes repair more urgent; eyes that are already macula-off are placed after them on the list. -
What have studies of scleral buckle repair shown about timing in macula-off detachment?
Buckle series found better average acuity when eyes were operated within a few days of macular detachment, with a gradual decline thereafter, although the data are not perfectly consistent and some authors found little difference within the first week. -
Within what window do most surgeons aim to repair a recent macula-off detachment?
Most surgeons aim to repair a recent macula-off detachment within a few days, often within 24 to 72 hours when logistics allow; older detachments are still repaired but with guarded counselling. -
What intraocular pressure is found in some eyes with rhegmatogenous retinal detachment?
Some eyes with a rhegmatogenous detachment have a lower intraocular pressure than the fellow eye, alongside a mobile corrugated opaque retina and a relative afferent pupillary defect in extensive cases. -
Which detachment is suitable for pneumatic retinopexy?
Pneumatic retinopexy suits a single break, or a cluster of breaks, within the superior 8 clock hours in a phakic eye; buckle and vitrectomy are chosen for other configurations. -
How long can visual recovery continue after repair of a macula-off detachment?
Visual recovery is slow and can continue for six to twelve months after successful reattachment, and distortion or reduced contrast may persist despite a technically perfect repair. -
Which OCT feature helps predict final acuity after macula-off detachment repair?
The integrity of the ellipsoid zone helps predict final acuity, and recovery of the ellipsoid and interdigitation zones on OCT tracks closely with recovery of vision; a thin or absent ellipsoid line is unfavourable. -
How should subretinal fluid persisting after gas absorption be managed?
Persistent subretinal fluid after gas absorption usually resolves over weeks, so the clinician should avoid intervening too early while continuing review for redetachment and epiretinal membrane. -
What should a patient be told about the fellow eye after a retinal detachment?
The fellow eye carries a higher risk of detachment, and the patient should be told that the warning symptoms to watch for are the same ones that brought them in.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.