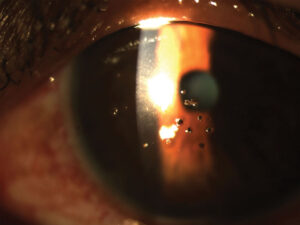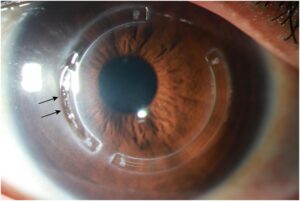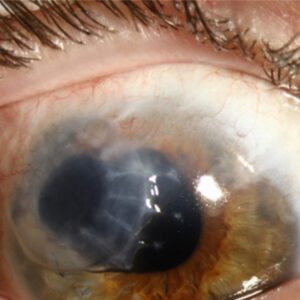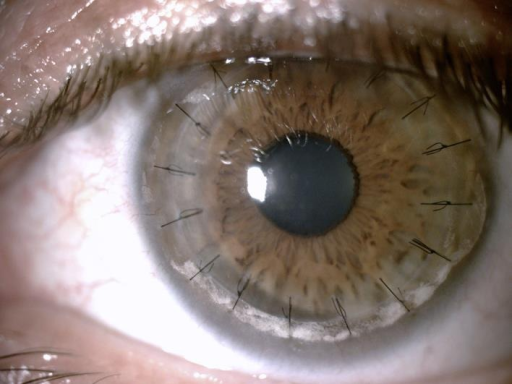
Deep anterior lamellar keratoplasty (DALK) replaces diseased corneal stroma down to the level of Descemet membrane while leaving the patient’s own endothelium in place, and it has become the preferred procedure for stromal disease with a healthy endothelium.
Avoiding an endothelial transplant removes the single largest cause of graft failure, which is endothelial rejection, and gives these patients a different long-term risk profile from a full-thickness graft.
Why Spare the Endothelium?
Endothelial cells do not regenerate, and immune rejection targeting the endothelium is the leading cause of late graft failure after penetrating keratoplasty.
When the endothelium is healthy and only the stroma is diseased, replacing just the stroma removes the tissue at risk of rejection and leaves the more durable, non-immunogenic layer untouched, which is the central rationale for DALK over a full-thickness transplant in the right patient.
Indications
DALK is suited to corneal disease confined to the stroma and epithelium, with a healthy endothelium.
- Keratoconus, particularly moderate to advanced disease not suitable for crosslinking or contact lenses (see keratoconus)
- Stromal corneal dystrophies, including macular, granular, and lattice dystrophy, when the endothelium is unaffected
- Corneal scarring from prior infection or trauma that spares the endothelium
- Some cases of corneal ectasia after refractive surgery
DALK is not appropriate when the endothelium itself is diseased, as in Fuchs endothelial dystrophy or after significant endothelial decompensation, since those cases need an endothelial or full-thickness graft.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteSurgical Technique
The goal is to remove host stroma down to a bare, intact Descemet membrane, onto which donor stroma is then sutured.
- The big bubble technique injects air into the deep stroma to separate it from Descemet membrane in a single plane, which is the most widely used approach when it succeeds
- Manual lamellar dissection is used when the big bubble cannot be achieved, removing stroma in layers
- Perforation of Descemet membrane during dissection is the main intraoperative complication, and a significant perforation may require conversion to full-thickness penetrating keratoplasty
Surgeon experience strongly influences both the success rate of achieving a clean big bubble and the perforation rate.
Advantages Over Penetrating Keratoplasty
- No risk of endothelial rejection, since the host endothelium is retained
- A closed-globe procedure for most of the operation, reducing the risk of expulsive hemorrhage
- Lower long-term risk of graft failure related to endothelial cell loss
- Comparable visual outcomes to penetrating keratoplasty in most series, once residual interface haze resolves
The main disadvantage is a technically demanding learning curve, and visual recovery can be limited by interface haze or irregularity even when the endothelium is preserved.
Complications
- Descemet membrane perforation, sometimes requiring conversion to penetrating keratoplasty
- Interface haze, which can limit best-corrected vision even after a technically successful graft
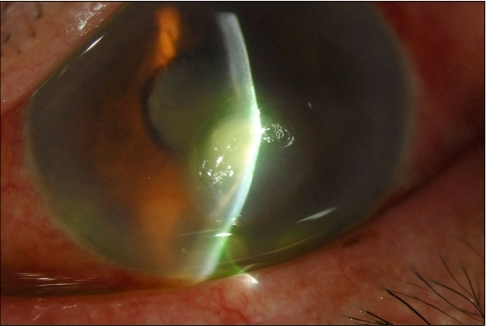
- Double anterior chamber, from residual fluid or air between the graft and host Descemet membrane
- Stromal rejection, which is less severe than endothelial rejection and usually responds well to topical corticosteroids
Prognosis
Visual outcomes are generally good, and the absence of endothelial rejection risk gives DALK a graft survival advantage over penetrating keratoplasty in most long-term comparisons.
Patient selection matters most: a healthy endothelium and disease confined to the stroma predict the best result, while patients who need conversion to penetrating keratoplasty during surgery lose much of that advantage for that eye.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Anwar M, Teichmann KD. Big-bubble technique to bare Descemet’s membrane in anterior lamellar keratoplasty. J Cataract Refract Surg. 2002;28:398-403.
- Feizi S, Javadi MA, Jamali H, Mirbabaee F. Deep anterior lamellar keratoplasty for keratoconus: big-bubble technique. Cornea. 2010;29:177-182.
- Ardjomand N, Hau S, McAlister JC, et al. Quality of vision and graft thickness in deep anterior lamellar and penetrating corneal allografts. Am J Ophthalmol. 2007;143:228-235.
- Keane M, Coster D, Ziaei M, Williams K. Deep anterior lamellar keratoplasty versus penetrating keratoplasty for treating keratoconus. Cochrane Database Syst Rev. 2014;(7):CD009700.
Test yourself
A few questions straight from this article.
-
What tissue does deep anterior lamellar keratoplasty replace?
DALK removes diseased stroma down to the level of Descemet membrane and leaves the patient's own endothelium in place. -
Which process is the leading cause of late graft failure after penetrating keratoplasty?
Endothelial cells do not regenerate, and immune rejection directed at the endothelium is the leading cause of late graft failure after penetrating keratoplasty. -
Which corneal condition calls for an endothelial or full-thickness graft rather than DALK?
DALK is inappropriate when the endothelium itself is diseased, as in Fuchs endothelial dystrophy or significant endothelial decompensation, which need an endothelial or full-thickness graft. -
How does the big bubble technique bare Descemet membrane during DALK?
The big bubble technique injects air into the deep stroma, separating it from Descemet membrane in a single clean plane, and is the most widely used approach when it works. -
What is the main intraoperative complication of deep anterior lamellar keratoplasty?
Descemet membrane perforation during dissection is the principal intraoperative complication, and a significant perforation may force conversion to full-thickness penetrating keratoplasty. -
Which approach is used in DALK when a big bubble cannot be achieved?
When the big bubble cannot be obtained, the surgeon switches to manual lamellar dissection, removing host stroma layer by layer. -
What produces a double anterior chamber after deep anterior lamellar keratoplasty?
A double anterior chamber arises from residual fluid or air collecting between the donor graft and the host Descemet membrane. -
How does stromal rejection after DALK typically behave?
Stromal rejection after DALK is less severe than endothelial rejection and usually responds well to topical corticosteroid treatment. -
Which complication can limit best-corrected vision after a technically successful DALK?
Interface haze or irregularity can limit best-corrected visual acuity even when the graft is technically successful and the endothelium is preserved. -
Which intraoperative risk is reduced because DALK is largely a closed-globe procedure?
Because most of a DALK is performed with the globe closed, the risk of expulsive hemorrhage is lower than with penetrating keratoplasty.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.