Eye emergencies are time-critical.
Some can be treated at the door, and others need urgent specialist care.
Knowing the red flags speeds the right decision.
Why Eye Emergencies Need Triage
Eye problems make up a large share of emergency department visits.
Most are minor, but a few threaten sight within hours.
Sorting them early saves vision.
Therefore, train front-line staff to triage.
Chemical Injury Among Eye Emergencies
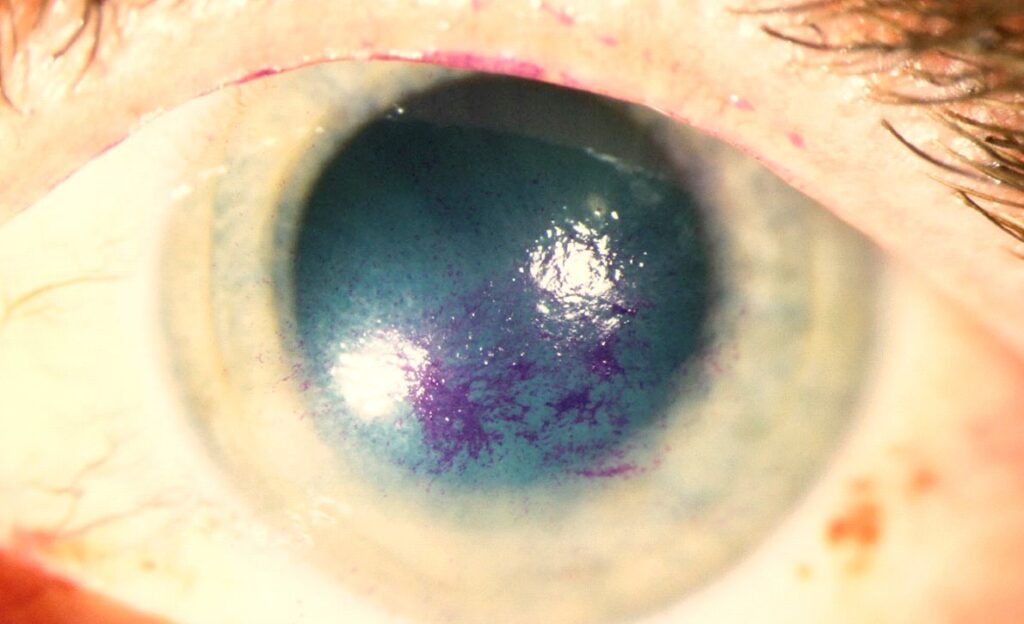
Alkali and acid burns need immediate irrigation.
Start washing at the scene and continue for at least 30 minutes (see chemical eye injury).
Check pH and keep irrigating until it is neutral.
So irrigate before asking questions.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteAngle Closure in Eye Emergencies
Severe pain, halos, nausea and a red eye signal angle closure.
Pressure is very high and the cornea hazy.
Treat with drops and systemic agents, then laser.
Also refer at once (see acute angle closure).
Retinal Detachment in Eye Emergencies
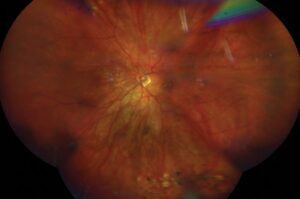
Flashes, floaters and a curtain suggest detachment.
Loss of central vision means the macula is involved.
Surgery is needed within a day or two.
Therefore, do not delay referral (see retinal detachment symptoms).
Central Retinal Artery Occlusion
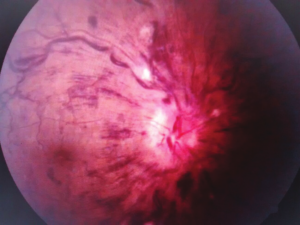
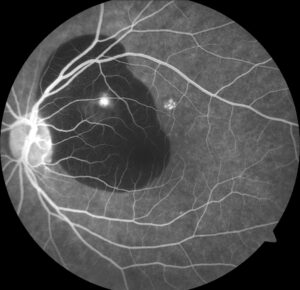
Sudden painless vision loss with a pale retina is an emergency.
It is a stroke equivalent (see central retinal artery occlusion).
Send the patient to a stroke center.
So time matters.
Endophthalmitis in Eye Emergencies
Pain, redness and falling vision after surgery or injection signal infection.
A hypopyon may be present.
Intravitreal antibiotics are required.
Also treat any case within days of surgery as an emergency (see acute postoperative endophthalmitis).
Orbital Cellulitis in Eye Emergencies
Swollen lids, fever, pain on eye movement and proptosis point to orbital spread.
Imaging and admission are needed.
Antibiotics should start without delay.
Therefore, treat it as an emergency (see orbital cellulitis).
Open Globe Injury
Penetrating trauma needs a shield and no pressure.
Do not remove foreign bodies.
Avoid topical drops and keep the patient fasting.
So arrange urgent surgical repair.
Corneal Ulcer
A white infiltrate with pain and redness needs same-day care.
Contact lens wearers are at high risk.
Scraping and intensive drops follow.
Also stop lens wear.
Hyphema
Blood in the anterior chamber after trauma requires review.
Raised pressure and rebleeding are risks (see hyphema).
Rest, a shield and close follow-up help.
So refer all cases.
Giant Cell Arteritis
Headache, jaw pain and sudden vision loss in an older adult need urgent steroids.
Delay risks loss of the second eye.
Blood tests support the diagnosis.
Therefore, treat on suspicion.
Acute Optic Neuritis and Other Neurological Causes
Painful vision loss in a young adult needs prompt assessment.
MRI and steroids may be needed.
New double vision or a field defect may indicate stroke.
Also arrange urgent imaging.
First Aid for Eye Emergencies
Irrigate chemicals, shield the eye after trauma and do not press on a ruptured globe.
Remove contact lenses if no injury is suspected.
Seek help quickly.
So give simple instructions to patients.
Eye Emergencies: Practical Summary
Check vision, pupils and pain, then decide the urgency.
If sight is at risk, refer the same day.
Because early care saves vision, keep a low threshold.
Finally, teach patients the warning signs.
Pitfalls to Avoid
- Do not wait for tests before irrigating a chemical injury
- Never apply pressure to a possible open globe
- Avoid reassuring painless sudden vision loss
- Do not delay steroids in suspected arteritis
Pediatric Eye Emergencies
Children with trauma or sudden squint need urgent review.
Leukocoria is also an emergency.
Because history is hard to get, examine thoroughly.
Therefore, refer when in doubt.
Eye Emergencies After Surgery
Pain, redness and falling vision after surgery need prompt action.
Endophthalmitis can progress within hours.
Because early treatment saves vision, call the surgeon.
So provide patients with a contact number.
Preparing Clinics for Eye Emergencies
Keep irrigation fluid, a shield and fluorescein at hand.
Train staff to recognize red flags.
Because time matters, write clear protocols.
Finally, audit cases after the event.
Telephone Triage
Ask about vision loss, pain, trauma and chemical exposure.
Book same-day visits for red-flag answers.
Because phone advice shapes outcomes, use a script.
Therefore, review calls regularly.
Eye Emergencies: Key Message
Teach patients that pain, vision loss and trauma need same-day care.
If in doubt, call the clinic.
Because delays harm vision, set a low threshold.
Finally, provide a written list of warning signs.
For the latest studies, see the PubMed results for eye emergencies.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Channa R, Zafar SN, Canner JK, Haring RS, Schneider EB, Friedman DS. Epidemiology of eye-related emergency department visits. JAMA Ophthalmol. 2016;134:312-319.
- Vaziri K, Schwartz SG, Flynn HW Jr, Kishor KS, Moshfeghi AA. Eye-related emergency department visits in the United States, 2010. Ophthalmology. 2016;123:917-919.
- Haring RS, Sheffield ID, Channa R, Canner JK, Schneider EB. Epidemiologic trends of chemical ocular burns in the United States. JAMA Ophthalmol. 2016;134:1119-1124.
- Mac Grory B, Schrag M, Biousse V, et al. Management of central retinal artery occlusion: a scientific statement from the American Heart Association. Stroke. 2021;52:e282-e294.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.