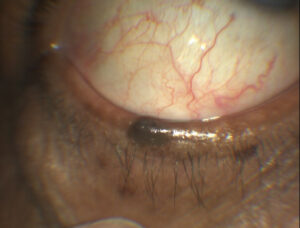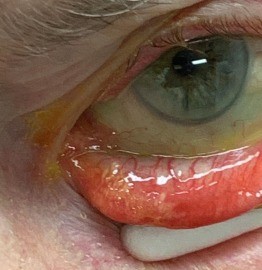
Sebaceous gland carcinoma is an aggressive eyelid malignancy that arises from the meibomian glands, the glands of Zeis, or the sebaceous glands of the caruncle, and it is notorious for masquerading as far more common and benign conditions, especially a recurrent chalazion or chronic unilateral blepharitis.
The delay this causes is the single biggest factor behind its worse prognosis compared with basal cell carcinoma, since the tumor keeps growing and can spread through the conjunctival epithelium while it is being treated for something else.
Why It Is Missed
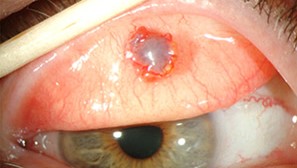
Sebaceous gland carcinoma often looks unremarkable at first: a firm, yellowish nodule that resembles a chalazion, or a diffuse thickening of the eyelid margin that resembles chronic blepharitis or meibomian gland dysfunction.
A substantial proportion of patients are treated for a presumed chalazion, sometimes more than once, before a biopsy reveals the true diagnosis.
Pagetoid spread, in which malignant cells migrate through the conjunctival and corneal epithelium without forming an obvious mass, adds another layer of difficulty, since the eye may show only diffuse conjunctival thickening or a papillary conjunctivitis-like appearance.
Warning Signs
Certain features should prompt biopsy rather than continued conservative treatment.
- A chalazion that recurs at the same site after treatment, or that recurs following incision and curettage
- Loss of eyelashes (madarosis) at the site of a presumed chalazion, since inflammatory chalazia do not usually destroy lash follicles (see madarosis)
- Diffuse yellowish thickening of the eyelid margin
- Unilateral chronic blepharoconjunctivitis that does not respond to standard treatment
- Any recurrent or atypical eyelid lesion in an older patient
A low threshold for biopsy, particularly for a chalazion that recurs after treatment or that appears atypical, is the single most effective way to catch this tumor earlier.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDiagnosis
Full-thickness eyelid biopsy is needed, since superficial biopsy can miss the tumor or the pagetoid spread within the epithelium.
Map biopsy, taking multiple conjunctival samples from different quadrants, is used when pagetoid spread is suspected, to define how far the malignant cells have travelled from the primary tumor.
Oil red O staining on fresh or frozen tissue can highlight the lipid content characteristic of sebaceous differentiation, supporting the histologic diagnosis.
Management
Surgical Excision
Wide local excision with margin control, often using Mohs micrographic surgery or frozen-section-controlled excision, is the primary treatment, followed by eyelid reconstruction matched to the resulting defect (see eyelid margin tumor reconstruction).
Extensive pagetoid spread may require conjunctival map biopsies to guide the extent of surgery, and, in severe cases, orbital exenteration when the tumor has spread beyond what can be controlled with eyelid-sparing surgery.
Regional and Systemic Disease
Sebaceous gland carcinoma can spread to regional lymph nodes, so palpation of the preauricular and cervical nodes is part of the evaluation, and imaging or sentinel node biopsy is considered for larger or higher-risk tumors.
Radiotherapy
Radiotherapy is used as an adjunct for incompletely excised tumors, for patients who cannot tolerate further surgery, or for regional disease, though surgery remains the primary treatment.
Systemic Association
Sebaceous gland carcinoma, particularly when multiple or in a younger patient, can be a marker of Muir-Torre syndrome, a hereditary cancer syndrome linked to Lynch syndrome mismatch repair gene mutations, and it warrants a discussion about screening for colorectal and other internal malignancies.
Prognosis
Delayed diagnosis is the strongest predictor of a worse outcome, including local recurrence, regional spread, and death from metastatic disease.
Early recognition and complete excision give a good prognosis, which is why any atypical or recurrent eyelid lesion deserves biopsy rather than another round of conservative treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields JA, Demirci H, Marr BP, Eagle RC Jr, Shields CL. Sebaceous carcinoma of the ocular region: a review. Surv Ophthalmol. 2005;50:103-122.
- Kass LG, Hornblass A. Sebaceous carcinoma of the ocular adnexa. Surv Ophthalmol. 1989;33:477-490.
- Muqit MM, Roberts F, Lee WR, Kemp E. Improved survival rates in sebaceous carcinoma of the eyelid. Eye (Lond). 2004;18:49-53.
- Cook BE Jr, Bartley GB. Treatment options and future prospects for the management of eyelid malignancies: an evidence-based update. Ophthalmology. 2001;108:2088-2098.
Test yourself
A few questions straight from this article.
-
From which structures does sebaceous gland carcinoma of the eyelid arise?
The tumor arises from the meibomian glands, the glands of Zeis, or the sebaceous glands of the caruncle. -
Which benign lesion does sebaceous gland carcinoma most characteristically masquerade as?
It is notorious for mimicking a recurrent chalazion, and many patients are treated for a presumed chalazion before biopsy reveals the malignancy. -
What characterises pagetoid spread in sebaceous gland carcinoma?
In pagetoid spread, malignant cells travel through the conjunctival and corneal epithelium without forming an obvious mass, sometimes looking only like a papillary conjunctivitis. -
Which sign at a presumed chalazion site should prompt biopsy for malignancy?
Madarosis at the site of a presumed chalazion is a red flag, because inflammatory chalazia do not usually destroy lash follicles. -
Which biopsy is required when sebaceous gland carcinoma is suspected?
A full-thickness eyelid biopsy is needed because a superficial sample can miss the tumor or the pagetoid spread lying within the epithelium. -
What is the purpose of conjunctival map biopsy in sebaceous gland carcinoma?
Map biopsy samples the conjunctiva in several quadrants to map the extent of pagetoid spread away from the primary tumor and guide the extent of surgery. -
Which stain highlights sebaceous differentiation in an eyelid tumor specimen?
Oil red O staining on fresh or frozen tissue demonstrates the lipid content typical of sebaceous differentiation and supports the histologic diagnosis. -
What role does radiotherapy play in sebaceous gland carcinoma of the eyelid?
Surgery remains primary; radiotherapy is reserved as an adjunct for incompletely excised tumors, patients unfit for further surgery, or regional disease. -
Which hereditary syndrome may be signalled by multiple sebaceous gland carcinomas?
Multiple tumors, or disease in a younger patient, can mark Muir-Torre syndrome, linked to Lynch syndrome mismatch repair mutations and warranting colorectal cancer screening discussion. -
What is the strongest predictor of a poor outcome in eyelid sebaceous gland carcinoma?
Delayed diagnosis is the strongest predictor of local recurrence, regional spread and death from metastasis, whereas early complete excision carries a good prognosis.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.