Headache and the eye overlap in daily practice.
Most headaches are benign, yet some signal eye or brain disease.
A careful eye examination catches the dangerous few.
Why Headache and the Eye Are Linked
The trigeminal nerve serves the eye and head.
Pain from the eye can be felt as headache.
Neurological disease can also affect vision.
Therefore, look at both systems.
Headache and the Eye in Migraine With Aura
Migraine aura causes zigzags, scintillations and blind spots lasting under an hour.
Symptoms spread slowly and are often bilateral.
Headache usually follows.
So aura lasts minutes, not seconds (see retinal migraine).
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteCluster Headache and the Eye
Cluster headache causes severe pain around one eye.
Tearing, redness and a drooping lid occur on the same side.
Attacks last up to three hours.
Also, patients pace the room during attacks.
Acute Angle Closure, Headache and the Eye
Severe eye pain with headache, halos and vomiting suggests angle closure.
The eye is red and the pupil mid-dilated (see acute angle-closure glaucoma).
It is an emergency.
Therefore, check pressure in painful red eyes.
Giant Cell Arteritis, Headache and the Eye
New headache after age 50 raises concern.
Jaw pain, scalp tenderness and visual symptoms add to it.
Check ESR and CRP and start steroids if suspected.
So never delay treatment while awaiting biopsy.
Raised Pressure, Headache and the Eye
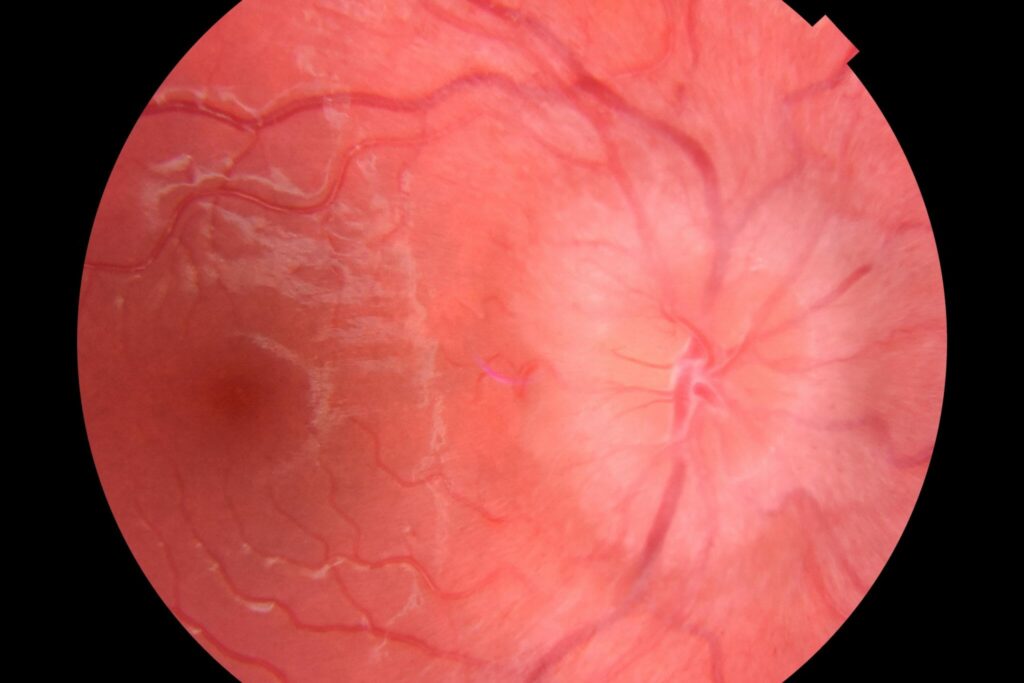
Headache worse on lying down or with transient visual obscurations suggests raised pressure.
Papilledema confirms it (see idiopathic intracranial hypertension).
Imaging and lumbar puncture follow.
Also assess visual fields.
Optic Neuritis
Pain on eye movement accompanies vision loss.
Young adults are mostly affected (see optic neuritis).
MRI shows white matter lesions in many.
So consider multiple sclerosis.
Refractive Error and Eye Strain
Uncorrected hyperopia and astigmatism can cause frontal headache after close work.
Evidence for a strong link is limited.
Correct significant errors and review symptoms.
Therefore, test vision in patients with chronic headache.
Convergence Insufficiency
Patients feel strain and headache when reading.
Near point of convergence is remote.
Exercises can help.
Also screen for binocular problems.
Photophobia
Light sensitivity occurs in migraine, meningitis and uveitis.
Eye redness and pain favor uveitis.
Neck stiffness and fever require urgent care.
So combine signs with history.
Sinus and Eye Disease
Facial pain and pressure may follow sinusitis.
Eye signs include swelling and proptosis in orbital spread.
Imaging and antibiotics are needed in such cases (see orbital cellulitis).
Therefore, do not dismiss eye swelling.
Red Flags for Headache and the Eye
Sudden severe headache, new neurological signs and vision loss need urgent assessment.
Papilledema and pupil changes also matter.
Age over 50 and cancer history raise risk.
So use a red-flag checklist.
Examination Priorities
Check visual acuity, pupils, fields, motility and the optic discs.
Measure pressure when the eye is red.
Dilate unless angle closure is suspected.
Also take blood pressure.
Headache and the Eye: Practical Summary
Ask about aura, jaw pain, red eye and positional pain.
If red flags exist, examine the discs and refer.
Because treatment of arteritis is urgent, act at once.
Finally, document the exam.
Pitfalls to Avoid
- Do not treat every headache as benign
- Never skip the optic disc examination
- Avoid delaying steroids in suspected arteritis
- Do not dilate a possible angle closure
Visual Snow and Persistent Aura
Some patients see static across the visual field for months.
Others have aura without headache.
Because these symptoms confuse, examine the eye and image if needed.
Therefore, reassure only after a normal work-up.
Medication Overuse
Frequent analgesics can cause headaches that return as the drug wears off.
If a patient takes pain medicine most days, ask about it.
Because withdrawal helps, refer to a headache clinic.
So include medication history in the visit.
Sleep Apnea and Morning Headache
Morning headache and daytime sleepiness suggest sleep apnea.
Sleep apnea also links to glaucoma and papilledema.
Because treatment helps both, ask about snoring.
Then arrange a sleep study.
When to Order Imaging
Order imaging for a new neurological sign, a thunderclap onset or papilledema.
If the exam is normal and the pattern is typical, imaging may not be needed.
Because radiation and cost matter, apply judgment.
Therefore, follow red-flag lists.
Working With Neurologists
Share eye findings in your referral letter.
If the discs look swollen, say so clearly.
Because teamwork improves outcomes, agree a follow-up plan.
Finally, keep the patient informed.
For the latest studies, see the PubMed results for headache and the eye.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Headache Classification Committee of the International Headache Society. The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38:1-211.
- Mollan SP, Davies B, Silver NC, et al. Idiopathic intracranial hypertension: consensus guidelines on management. J Neurol Neurosurg Psychiatry. 2018;89:1088-1100.
- Do TP, Remmers A, Schytz HW, et al. Red and orange flags for secondary headaches in clinical practice: SNNOOP10 list. Neurology. 2019;92:134-144.
- Digre KB, Brennan KC. Shedding light on photophobia. J Neuroophthalmol. 2012;32:68-81.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.