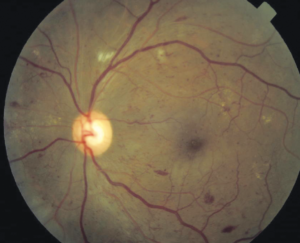
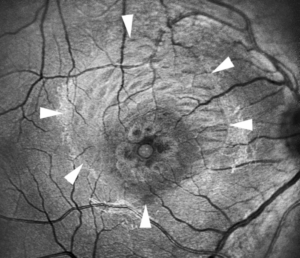
Macular pucker recurrence after surgical peeling is less common than many patients expect to hear, and much of what looks like recurrence on a postoperative OCT scan is not actually regrowth of the membrane but a related, usually benign, surface change from the surgery itself.
Separating true recurrence from these surgical artifacts changes the conversation with a patient who returns worried that their pucker is coming back.
True Recurrence Versus Look-Alikes
Genuine epiretinal membrane recurrence, meaning regrowth of a fibrocellular membrane on the retinal surface after a technically complete initial peel, does occur, but published rates are low, generally in the low single digits of percent in most modern series.
Two other postoperative findings are far more commonly confused with recurrence.
- Dissociated optic nerve fiber layer appearance, a dimpled, arcuate pattern seen after internal limiting membrane (ILM) peeling, thought to reflect subtle mechanical disruption of the nerve fiber layer rather than true membrane regrowth, and generally without visual consequence
- Residual or incompletely peeled membrane fragments left at the time of the original surgery, which can be mistaken for new membrane formation on follow-up imaging when in fact they were never fully removed
Why ILM Peeling Reduces True Recurrence
Peeling the internal limiting membrane in addition to the epiretinal membrane itself has become standard practice in most cases, based on evidence that it substantially reduces the rate of true epiretinal membrane recurrence compared with removing the epiretinal membrane alone.
The rationale is that residual glial and myofibroblastic cells on the ILM surface, if left behind, can serve as a scaffold for new membrane formation, and removing the ILM removes that scaffold along with the visible membrane.
The tradeoff is that ILM peeling itself is thought to contribute to the dissociated optic nerve fiber layer appearance described above, so the technique that reduces true recurrence also increases the frequency of this benign look-alike finding.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteRisk Factors for True Recurrence
- Incomplete removal of the epiretinal membrane at the initial surgery
- Peeling the epiretinal membrane without also removing the ILM
- An underlying condition with an ongoing proliferative stimulus, such as proliferative vitreoretinopathy or chronic inflammation
- Secondary epiretinal membranes, which form in the setting of another retinal disease such as diabetic retinopathy or vein occlusion, and can have a higher recurrence tendency than idiopathic membranes if the underlying disease remains active
Clinical Evaluation of Suspected Recurrence
- OCT is the key tool, and careful comparison with immediate postoperative scans helps distinguish new membrane formation from a dissociated nerve fiber layer pattern that has simply persisted or become more visible over time
- Assessment of visual acuity and symptoms, since a true recurrence causing new metamorphopsia or vision loss is a different clinical situation from an incidental OCT finding with stable, good vision
- Review of the original operative note, when available, regarding whether ILM peeling was performed and whether the surgeon noted complete removal
Management
Incidental Findings Without Visual Symptoms
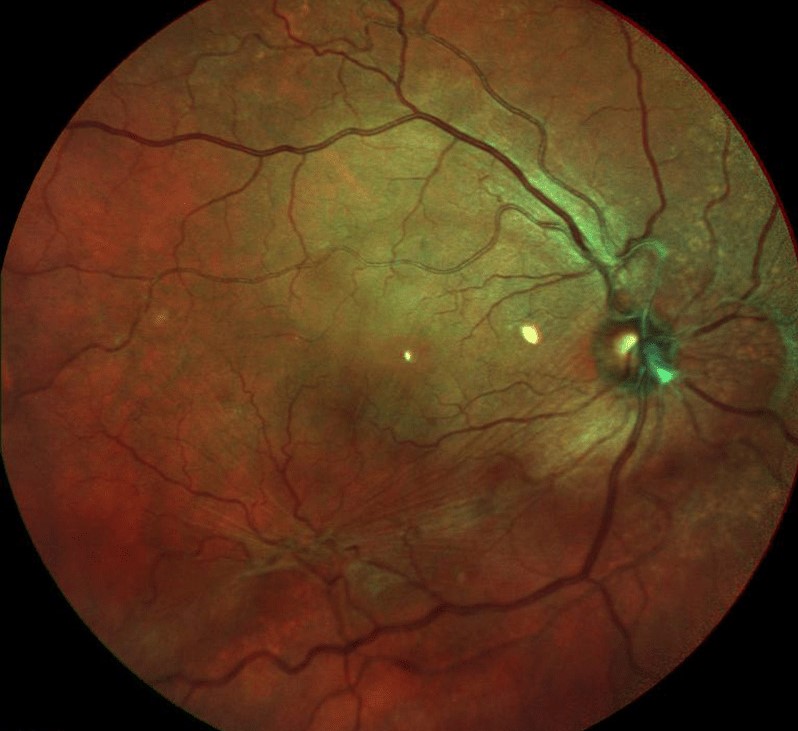
A dissociated nerve fiber layer appearance or a small residual membrane fragment without visual symptoms and with stable good acuity is generally observed rather than treated.
True, Symptomatic Recurrence
Repeat vitrectomy with membrane and, if not previously performed, ILM peeling is the treatment for a true recurrent epiretinal membrane causing significant visual symptoms.
Outcomes of repeat surgery are generally favorable, though visual recovery may be less complete than after the first operation, particularly if there has been a prolonged period of recurrent traction (see epiretinal membrane).
Counseling Patients
Patients benefit from knowing before surgery that a certain postoperative OCT appearance is expected and not a sign of failure, which reduces unnecessary alarm at follow-up visits when a subtle surface irregularity is seen.
Setting this expectation up front is as much a part of good postoperative care as the surgery itself.
Prognosis
True recurrence requiring reoperation is uncommon, and most patients maintain the visual improvement achieved with their initial surgery.
When recurrence does occur and is treated, outcomes with repeat surgery are generally good, though cumulative surgical trauma to the macula can modestly limit the ceiling of visual recovery compared with a single successful operation.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Tadayoni R, Paques M, Massin P, Mouki-Benani S, Mikol J, Gaudric A. Dissociated optic nerve fiber layer appearance after idiopathic epiretinal membrane removal. Ophthalmology. 2001;108:2279-2283.
- Chang WC, Lin C, Lee CH, Sung TL, Tung TH, Liu JH. Vitrectomy with or without internal limiting membrane peeling for idiopathic epiretinal membrane. PLoS One. 2017;12:e0179105.
- Park DW, Dugel PU, Garda J, et al. Macular pucker removal with and without internal limiting membrane peeling. Ophthalmology. 2003;110:62-64.
- Sandali O, El Sanharawi M, Basli E, et al. Epiretinal membrane recurrence: incidence, characteristics, evolution, and preventive and risk factors. Retina. 2013;33:2032-2038.
Test yourself
A few questions straight from this article.
-
Much of what looks like macular pucker recurrence on postoperative OCT is actually what?
Most of what appears to be recurrence on a follow-up scan is a related, usually benign surface change produced by the surgery rather than regrowth of the membrane. -
Published rates of true epiretinal membrane recurrence after a complete peel fall in which range?
Genuine regrowth of a fibrocellular membrane after a technically complete peel does occur, but published rates are low, generally in the low single digits of percent in modern series. -
Which OCT appearance follows internal limiting membrane peeling and is usually of no visual consequence?
The dissociated optic nerve fibre layer appearance is a dimpled, arcuate pattern seen after ILM peeling, thought to reflect subtle mechanical disruption and generally without visual consequence. -
What limits the ceiling of visual recovery after repeat surgery for a recurrent macular pucker?
Outcomes of repeat surgery are generally good, but cumulative surgical trauma to the macula can modestly limit visual recovery compared with a single successful operation. -
Why does removing the internal limiting membrane reduce true epiretinal membrane recurrence?
Residual glial and myofibroblastic cells left on the ILM surface can act as a scaffold for new membrane formation, so removing the ILM removes that scaffold. -
What is the stated tradeoff of adding ILM peeling to epiretinal membrane removal?
ILM peeling is thought to contribute to the dissociated optic nerve fibre layer appearance, so the technique that lowers true recurrence raises the frequency of this benign look-alike. -
Which situation carries a higher tendency to true epiretinal membrane recurrence?
Secondary membranes arising with diabetic retinopathy or vein occlusion can recur more readily than idiopathic membranes if the underlying disease stays active. -
Which comparison best helps interpret a suspected recurrence seen on OCT?
Careful comparison with the immediate postoperative scans distinguishes new membrane formation from a dissociated nerve fibre layer pattern that has persisted or become more visible. -
How is a dissociated nerve fibre layer appearance with stable good acuity managed?
A dissociated nerve fibre layer appearance, or a small residual fragment, without visual symptoms and with stable good acuity is generally observed rather than treated. -
What is the treatment for a true, symptomatic recurrent epiretinal membrane?
True recurrence causing significant visual symptoms is treated by repeat vitrectomy with membrane removal and ILM peeling if that was not done at the first operation.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.