Cataract surgery and anticoagulants raise a common question, because many elderly patients take blood thinners for atrial fibrillation, stroke prevention, or coronary disease.
Stopping these drugs carries a real risk of thromboembolism, while the risk of serious bleeding from cataract surgery is very small.
Most guidance now recommends continuing the medication.
Cataract Surgery and Anticoagulants: The Risk of Stopping
Warfarin, direct oral anticoagulants, aspirin, and clopidogrel are given to prevent clots in patients at risk.
Stopping them, even for a few days, can lead to stroke, myocardial infarction, or thrombosis.
The harm of such an event is much greater than the risk of a small hemorrhage in the eye.
Cataract surgery is a low-bleeding-risk procedure (see phacoemulsification), particularly when it is done through a clear corneal incision under topical anesthesia.
Cataract Surgery and Anticoagulants: What the Evidence Shows
A large Cardiovascular and cataract-surgery study of anticoagulant and antiplatelet medication found a very low rate of sight-threatening hemorrhage. It also found no increase in complications in patients who continued aspirin, clopidogrel, or warfarin.
Another study of a national dataset of tens of thousands of cataract operations looked at bleeding. The rate of intraoperative and postoperative bleeding was no higher in patients taking antithrombotic drugs.
A survey of medical complications found that stopping medicines before cataract surgery did not reduce the risk of ocular hemorrhage, but exposed patients to systemic risk.
Studies of anesthetic techniques show that sharp needle blocks carry a risk of retrobulbar hemorrhage, so the choice of anesthesia matters.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteChoosing the Anesthetic
- Topical or intracameral anesthesia: the preferred option in patients on anticoagulants, with no needle
- Sub-Tenon anesthesia: a blunt cannula technique with a low risk of hemorrhage, although conjunctival bleeding can occur
- Peribulbar block: a sharp needle outside the muscle cone, with some risk
- Retrobulbar block: the highest risk of orbital hemorrhage, so avoid it in anticoagulated patients
Cataract Surgery and Anticoagulants: Practical Recommendations
- Warfarin: continue it, and check the INR in the days before surgery. Confirm that it is within the therapeutic range, usually not higher than about 3.0 to 3.5, depending on local guidance
- Direct oral anticoagulants: continue them according to the usual dosing, and tell the surgeon which one is used
- Aspirin and clopidogrel: continue
- Dual antiplatelet therapy and complex regimens: discuss with the prescribing physician, but usually continue
- Herbal supplements and fish oil: low risk, but ask about them
Patients with very high INR values or uncontrolled bleeding disorders need discussion before surgery.
Surgical Technique
Use a clear corneal incision, which is avascular, and avoid scleral tunnel incisions where bleeding may occur.
Take extra care with iris manipulation, and with the placement of ports, since hyphema is a possible bleed.
Keep the anterior chamber formed at the end of the case, and check the wound for leaks.
Cataract Surgery and Anticoagulants: What to Tell the Patient
Reassure patients that they do not need to stop their medicine unless advised by their doctor, and that this advice is based on evidence.
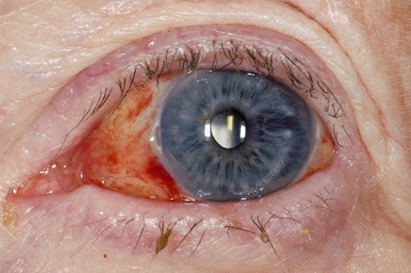
Explain what bleeding may occur, for example a small subconjunctival hemorrhage, and what to do if there is sudden pain or loss of vision.
Make sure the clinic has an up-to-date list of the drugs the patient takes.
Special Situations
Patients on anticoagulants who need combined procedures, such as cataract surgery with glaucoma surgery or vitrectomy, may need individual advice. The bleeding risk rises with the complexity of the operation.
Those with very high bleeding risk, such as a recent major hemorrhage or severe thrombocytopenia, need a decision with their physician.
A patient who takes both an anticoagulant and an antiplatelet drug is at higher risk of bruising and conjunctival hemorrhage. Still, the rate of serious ocular bleeding remains very low.
Communication With Other Physicians
Do not tell patients to stop an anticoagulant without a discussion with the prescribing doctor, and avoid unnecessary letters that ask whether the drug may be withheld.
A short note to the general practitioner prevents unnecessary changes at the pre-assessment clinic. It says that the surgery is low risk and that the drug should continue.
Pre-Assessment Practicalities
- Record the name, dose, and indication of each blood-thinning drug
- Check the INR within the week before surgery if the patient takes warfarin, and plan a repeat if it is out of range
- Ask the patient to bring a list of all medicines, including herbal products
- Prefer topical anesthesia, and record the choice in the chart
- Instruct the patient on what a small subconjunctival hemorrhage looks like, so that it does not cause alarm
If the INR is above the recommended limit, discuss with the physician and consider rescheduling instead of stopping the drug without advice.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Katz J, Feldman MA, Bass EB, et al. Risks and benefits of anticoagulant and antiplatelet medication use before cataract surgery. Ophthalmology. 2003;110:1784-1788.
- Benzimra JD, Johnston RL, Jaycock P, et al. The Cataract National Dataset electronic multicentre audit of 55,567 operations: antiplatelet and anticoagulant medications. Eye. 2009;23:10-16.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 11: Lens and Cataract. AAO; current edition.
Test yourself
A few questions straight from this article.
-
What does most current guidance recommend for anticoagulants and antiplatelet drugs before routine cataract surgery?
Most guidance now recommends continuing these drugs; warfarin, DOACs, aspirin and clopidogrel are all usually continued. -
Why is stopping anticoagulants before cataract surgery discouraged?
Stopping even for a few days can cause stroke, myocardial infarction or thrombosis, while serious bleeding from cataract surgery is very rare. -
Which anesthetic is preferred for cataract surgery in a patient on anticoagulants?
Topical or intracameral anesthesia uses no needle, so it is preferred in anticoagulated patients. -
Which anesthetic technique carries the highest risk of orbital hemorrhage in anticoagulated cataract patients?
Sharp needle blocks risk retrobulbar hemorrhage, and the retrobulbar block carries the highest risk, so it should be avoided in these patients. -
For a patient continuing warfarin through cataract surgery, what upper INR limit is usually accepted?
The INR should be checked in the week before surgery and be within the therapeutic range, usually not above about 3.0 to 3.5 depending on local guidance. -
Which incision is preferred for cataract surgery in a patient on anticoagulants?
A clear corneal incision is avascular, so scleral tunnel incisions, where bleeding may occur, are avoided. -
Which anticoagulated cataract patients may need individual advice because their bleeding risk is higher?
Bleeding risk rises with the complexity of the operation, so combined procedures may need individual advice. -
Pre-assessment for cataract surgery finds the warfarin INR above the recommended limit. What is advised?
If the INR is too high, discuss with the physician and consider rescheduling rather than stopping the drug without advice. -
Which minor bleed should anticoagulated patients be told to expect after cataract surgery so it does not alarm them?
Patients should know what a small subconjunctival hemorrhage looks like, and should report sudden pain or loss of vision. -
What happens when a cataract patient takes both an anticoagulant and an antiplatelet drug?
Combined therapy raises the risk of bruising and conjunctival hemorrhage, but the rate of serious ocular bleeding remains very low.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.