Dry eye treatment works best when it follows a clear sequence.
Start with simple measures and escalate only if symptoms and signs persist.
The TFOS DEWS II report describes this stepwise model.
Confirm the Diagnosis First
Symptoms alone do not prove dry eye.
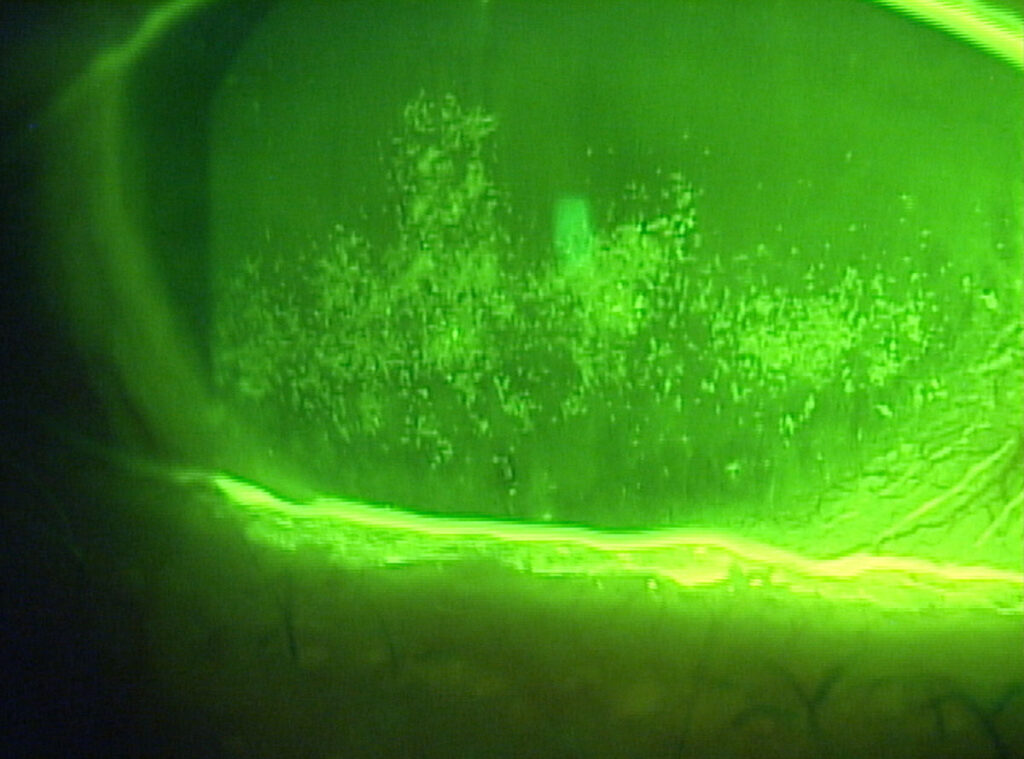
Check tear break-up time, corneal staining and the lid margins.
Also exclude allergy, infection and neurotrophic disease.
Therefore, treat only after the diagnosis is clear (see dry eye disease).
Step One in Dry Eye Treatment
Counsel patients on screen breaks, humidity and avoiding direct airflow.
Review their drugs, because antihistamines and some antidepressants dry the eye.
The DREAM study found no clear benefit from omega-3 supplements.
So do not promise results from supplements.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteLubricants in Dry Eye Treatment
Preservative-free lubricants suit frequent use.
Start with four drops a day and adjust to symptoms.
Gels and ointments help at night.
Reassess after four to six weeks.
Lid Care in Dry Eye Treatment
Warm compresses and gentle lid hygiene help meibomian gland dysfunction.
Patients need to repeat them daily to keep the benefit.
Also treat blepharitis when it is present (see blepharitis).
Therefore, always examine the lid margin.
Anti-Inflammatory Dry Eye Treatment
Topical cyclosporine and lifitegrast target inflammation on the ocular surface.
Both take weeks to work, so warn patients early.
Short courses of a low-potency steroid can bridge the gap.
However, monitor pressure and the lens during steroid use.
Punctal Plugs
Plugs reduce tear drainage in aqueous deficiency.
They suit patients with clear tear loss and good lid health.
However, they can cause tearing and infection.
Therefore, reserve them for selected eyes.
Biologic Drops
Autologous serum supplies growth factors and vitamins found in natural tears.
It helps patients with severe disease or persistent staining.
Supply is limited, and preparation needs a qualified pharmacy.
See autologous serum eye drops.
Oral and Procedural Options
Low-dose oral doxycycline can help meibomian gland disease.
Thermal pulsation and light-based treatments also have a role.
However, trial results vary between devices.
Therefore, choose them after lid care has failed.
Dry Eye Treatment in Severe Disease
Scleral lenses protect the cornea and keep a fluid reservoir in front of it.
Amniotic membrane and tarsorrhaphy rescue refractory cases.
In addition, search for systemic causes such as Sjogren syndrome.
Early referral prevents scarring.
Follow-Up in Dry Eye Treatment
Review patients after four to eight weeks of any change.
Compare symptoms, staining and tear break-up time.
Then step up or step down according to the response.
Keep the plan simple to protect adherence.
Setting Expectations
Dry eye is a chronic condition with good and bad weeks.
Cure is rare, but control is realistic.
Therefore, explain the goals at the first visit.
Patients who understand this stay with the plan.
Pitfalls to Avoid
- Do not skip the lid examination
- Never prescribe a steroid without a follow-up date
- Do not use plugs in eyes with active inflammation
- Avoid changing several treatments at once
Matching Dry Eye Treatment to Subtype
Aqueous deficiency responds best to lubricants, plugs and anti-inflammatory drops.
Evaporative disease responds to lid care and oil-based drops.
Many patients have both, so combine the steps.
Therefore, identify the subtype before choosing the plan.
Dry Eye Treatment After Cataract Surgery
Surgery can unmask or worsen dry eye.
Treat the surface before measuring for the lens.
Poor surface quality leads to unreliable biometry.
So optimize the tear film in the weeks before surgery.
Dry Eye Treatment in Contact Lens Wearers
Lens wear reduces tear stability and adds friction.
Switch to a lens with higher water content or a daily disposable.
Also reduce wearing time.
In addition, use drops labeled for lenses.
Dry Eye Treatment and Screen Use
Blink rate falls by half during screen work.
Teach patients the twenty-twenty-twenty rule for breaks.
Place the screen slightly below eye level.
This reduces the exposed surface area.
Dry Eye Treatment in Systemic Disease
Rheumatoid arthritis, thyroid disease and Sjogren syndrome all dry the eye.
Ask about dry mouth and joint pain.
Also review medication lists for drying agents.
Therefore, coordinate care with the physician.
Measuring Progress
Use a symptom score at each visit.
Add tear break-up time and corneal staining.
Photograph the stain if possible.
Over time, the trend guides the next step.
When to Refer
Refer patients with severe pain, corneal ulcers or thinning.
Refer those with suspected Sjogren syndrome or ocular cicatricial disease.
Also refer when standard care fails after three months.
Early referral protects vision.
For the latest studies, see the PubMed results for dry eye treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Jones L, Downie LE, Korb D, et al. TFOS DEWS II management and therapy report. Ocul Surf. 2017;15:575-628.
- Craig JP, Nichols KK, Akpek EK, et al. TFOS DEWS II definition and classification report. Ocul Surf. 2017;15:276-283.
- Asbell PA, Maguire MG, Pistilli M, et al. n-3 fatty acid supplementation for the treatment of dry eye disease. N Engl J Med. 2018;378:1681-1690.
- Akpek EK, Amescua G, Farid M, et al. Dry eye syndrome preferred practice pattern. Ophthalmology. 2019;126:286-334.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.