AMD genetics accounts for a large share of the risk of age-related macular degeneration, and it shapes how we think about prevention and therapy.
Common variants in the complement pathway and at chromosome 10q26 explain most of the known heritability.
Genetic testing is not part of routine care, but knowing the biology helps clinicians to counsel families.
How AMD Genetics Contributes to Risk
Twin and family studies show that heritability is high, with estimates between 45 and 70 percent.
Environmental factors such as smoking and diet interact with genes, so risk is multifactorial.
A person with an affected parent or sibling has a clearly higher chance of the disease (see age-related macular degeneration).
The CFH Gene and AMD Genetics
Klein and colleagues found that a variant in complement factor H, Y402H, strongly increases risk.
Haines and colleagues reported the same association in an independent study the same year.
Homozygous carriers of the risk variant have several times the risk of noncarriers.
The gene regulates the alternative complement pathway, so complement activation is central to the disease.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteARMS2 and HTRA1 in AMD Genetics
A second major locus lies at 10q26 near ARMS2 and HTRA1.
Rivera and colleagues showed that it contributes independently of CFH.
The ARMS2 variant carries a high risk of neovascular disease, and the exact causal gene is still debated (see geographic atrophy).
Other Genes in AMD Genetics
- Complement genes: C3, C2, CFB, CFI, SERPING1
- Lipid and extracellular matrix genes
- Rare coding variants in CFH and CFI
Fritsche and colleagues identified 34 loci in a large collaborative study and found that rare and common variants both contribute.
Genetic Risk Scores in AMD Genetics
Risk scores combine many variants to estimate disease probability.
They discriminate between high and low risk groups, but they have limited value in predicting an individual’s outcome.
Chew and colleagues reviewed the use of testing with AREDS supplements and found no clear role for routine testing.
Clinical Use of AMD Genetics
Current guidelines do not recommend routine genetic testing in AMD.
Testing may help research, family counseling, and trials that stratify by genotype.
Use the family history, imaging, and lifestyle factors to guide care, and advise smoking cessation and a healthy diet.
An Example Case
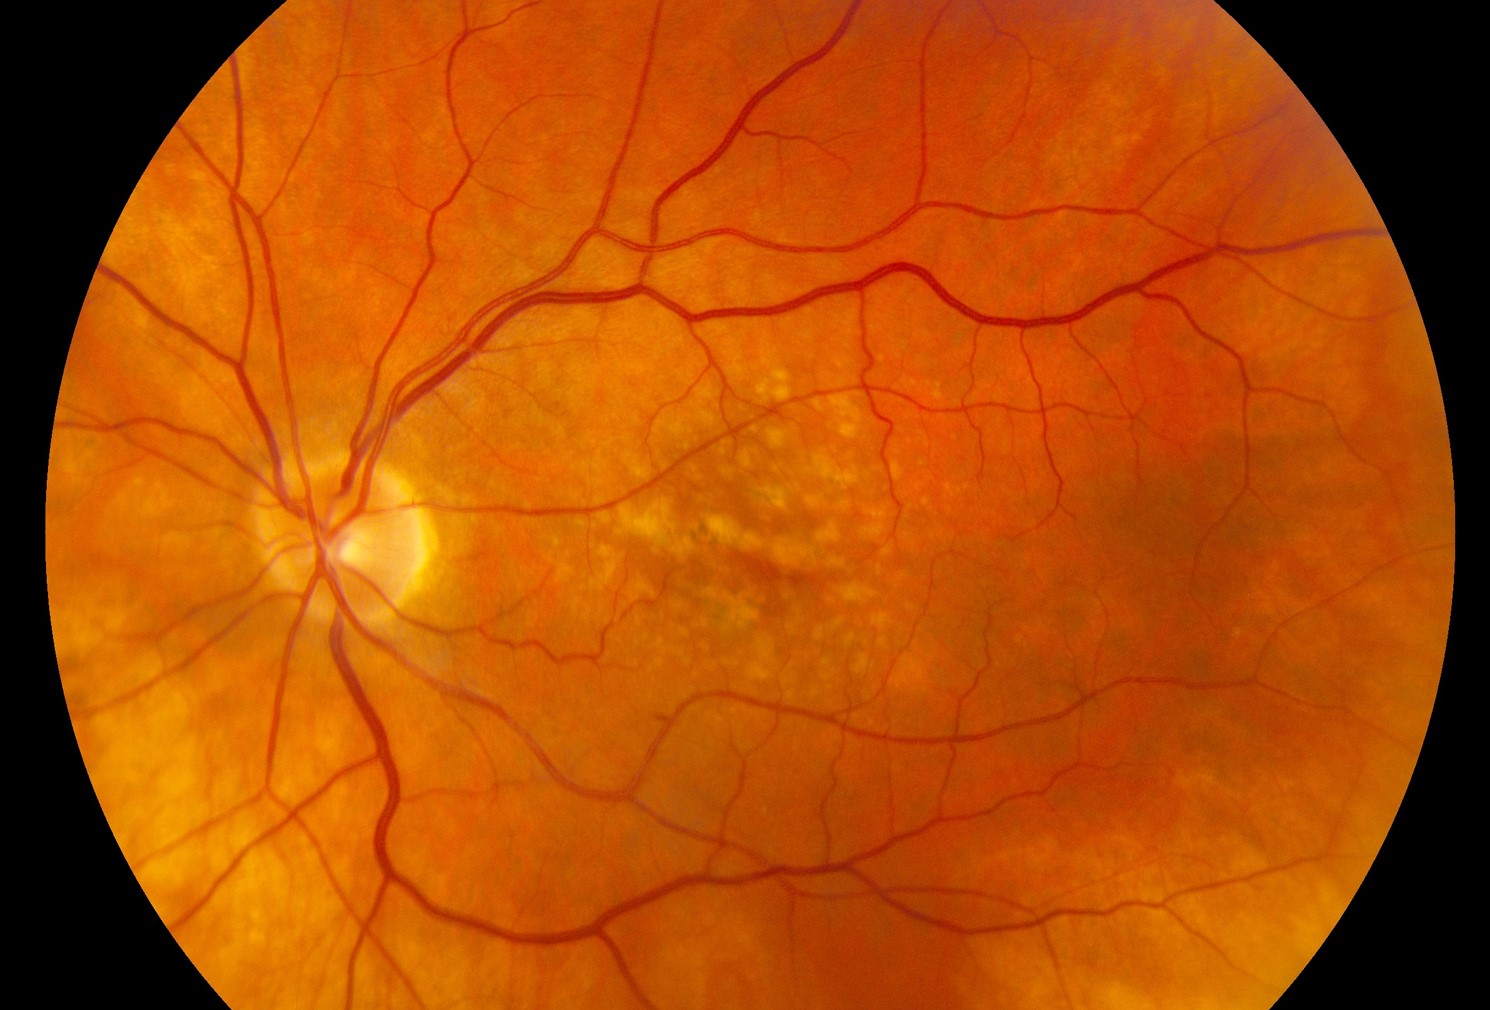
A 56-year-old man has intermediate AMD in both eyes, and his mother had advanced disease at 70.
He asks whether he should have a genetic test to know his risk.
The clinician explains that genes raise risk but do not decide the outcome, and that testing does not change current care.
Instead, they review his smoking status, diet, and supplement use, and they plan regular OCT.
He stops smoking, takes the AREDS2 formulation, and monitors his vision at home.
Questions Patients Ask
Patients ask whether their children will get the disease, and the answer is that the risk is higher than average but far from certain.
They also ask whether a gene test will tell them what to do, and for now it will not change treatment.
Because family fear is common, explain that lifestyle measures lower risk even in carriers.
Pitfalls to Avoid
- Ordering direct-to-consumer tests without counseling
- Telling a carrier that disease is certain
- Withholding supplements because the genotype is favorable
- Using genetic results to change anti-VEGF choices without evidence
Looking Ahead
Polygenic risk scores may improve prediction, and they may select people for prevention trials.
Also, complement-targeting drugs may work better in specific genotypes, though data are still preliminary.
Therefore, genetics may influence care within the next decade.
Practical Points
Take a family history in every patient with AMD.
Then advise first-degree relatives to have a dilated exam after age 50.
Also give clear lifestyle advice, whatever the genotype.
Gene and Environment
Smoking multiplies the risk in carriers of CFH and ARMS2 risk alleles.
Because tobacco use is modifiable, its effect gives a strong reason to quit.
Diet rich in fish and vegetables also lowers risk.
Genetic Testing in Trials
Researchers genotype participants to stratify and to study response.
Some trials of complement inhibitors report subgroup results by CFH status.
Therefore, patients who enter trials may receive genotype information.
Family Screening
Because first-degree relatives share risk, advise them to have a dilated examination after age 50.
Then ask them to report new distortion or blurred vision at once.
Also stress that lifestyle measures help even when a relative has advanced disease.
For the latest studies, see the PubMed results for AMD genetics.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Klein RJ, Zeiss C, Chew EY, et al. Complement factor H polymorphism in age-related macular degeneration. Science. 2005;308:385-389.
- Haines JL, Hauser MA, Schmidt S, et al. Complement factor H variant increases the risk of age-related macular degeneration. Science. 2005;308:419-421.
- Fritsche LG, Igl W, Bailey JN, et al. A large genome-wide association study of age-related macular degeneration highlights contributions of rare and common variants. Nat Genet. 2016;48:134-143.
- Chew EY, Klein ML, Clemons TE, et al. Genetic testing in persons with age-related macular degeneration and the use of the AREDS supplements: to test or not to test? Ophthalmology. 2015;122:212-215.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.