Seborrheic keratosis is the most common benign epidermal tumor in older adults, and it often appears on the eyelids and the periocular skin.
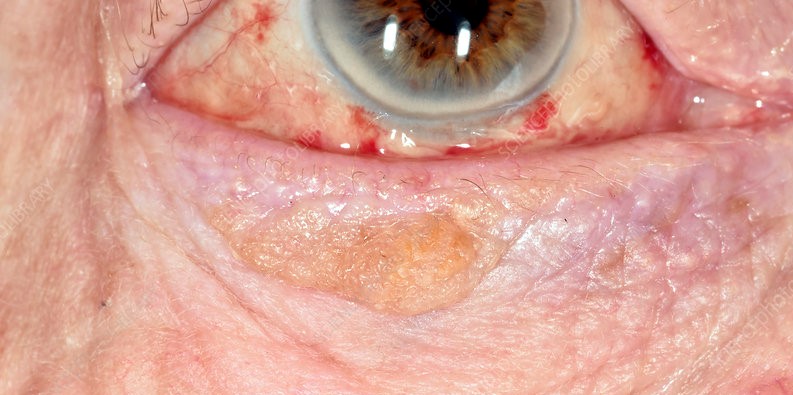
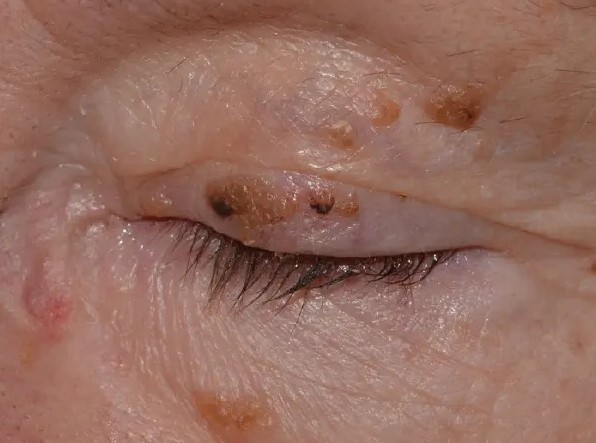
It looks waxy and appears stuck onto the skin, and it can also be brown or black, which causes worry about melanoma.
The diagnosis is usually clinical, and treatment is also for comfort or cosmetic reasons.
What Is a Seborrheic Keratosis?
The lesion is a proliferation of immature keratinocytes in the epidermis, and it is not a precancerous lesion.
It increases in number with age, and it is more common in sun-exposed areas but occurs in other locations as well.
In addition, the cause is unknown, and doctors suspect genetic factors and ultraviolet exposure.
Also, lesions may be single or multiple, and they vary in color from tan to dark brown.
Clinical Features of Seborrheic Keratosis
- A well-demarcated, raised, round or oval plaque with a waxy, verrucous, or velvety surface
- A “stuck-on” appearance, as if the lesion could be scraped off the skin
- Color varying from skin-colored to dark brown or black, with a uniform tone in most cases
- Horn cysts, small white or yellow keratin-filled spots, visible with magnification
- A pedunculated form on the eyelid margin and lid skin
- Itching or irritation if rubbed by glasses or lashes, with occasional inflammation (irritated seborrheic keratosis)
The lesion is benign, and it does not invade deeper tissue.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDermoscopy and Diagnosis
Dermoscopy may show comedo-like openings, milia-like cysts, and a cerebriform pattern, which support the diagnosis.
Slit-lamp magnification can reveal similar features.
Clinicians perform biopsy or excision with histologic examination when the diagnosis is uncertain, when the lesion has atypical features, or when it changes.
Differential Diagnosis of Seborrheic Keratosis
- Eyelid nevus: a smoother, evenly pigmented lesion without the waxy surface (see eyelid nevus)
- Pigmented basal cell carcinoma: a pearly lesion with rolled borders and telangiectasia (see basal cell carcinoma of the eyelid)
- Melanoma and lentigo maligna: irregular color and borders, with change over time
- Actinic keratosis: a rough, scaly, pink or tan patch on sun-damaged skin (see actinic keratosis)
- Squamous cell carcinoma and keratoacanthoma: a fast-growing, firm, ulcerated lesion (see keratoacanthoma)
- Verruca vulgaris and papilloma: a wart-like growth
A history of rapid growth, bleeding, or ulceration is a red flag.
Sign of Leser-Trélat
A sudden appearance of many seborrheic keratoses, accompanied by itching, has appeared in reports with internal malignancy, mostly gastrointestinal adenocarcinoma.
Also, experts debate the association, and most patients with multiple lesions do not have cancer.
A patient with a sudden eruption of lesions merits a general medical review and referral to a dermatologist.
Treatment for Seborrheic Keratosis
Treatment is not required for most lesions.
Clinicians also consider removal for irritation, cosmetic reasons, or diagnostic doubt.
- Shave excision: the surgeon removes the lesion at the level of the skin, which is quick and leaves little scar
- Curettage and electrodesiccation: used in a limited way on the lids
- Cryotherapy: brief freezing with liquid nitrogen, with care near the eye, as it can cause depigmentation
- Full excision: for pedunculated lesions and when you suspect malignancy, with histopathology
Always send removed tissue for examination if there is any doubt, because misdiagnosis of a pigmented malignancy can be dangerous.
Avoid thermal methods close to the lid margin and the eye, and protect the cornea during treatment.
Counselling
Reassure the patient that the lesion is benign, that it does not turn into cancer, and that new lesions may appear with time.
Advise protection from the sun, and ask the patient to return if a lesion changes, bleeds, or becomes irritated.
Procedural Notes for the Lids
Use local anesthesia with a small amount of lidocaine, and protect the globe with a corneal shield when using heat or freezing near the lid margin.
Also, surgeons perform shave excision with a blade or with scissors, and treat the base lightly to stop bleeding.
After the procedure, apply antibiotic ointment, and review in one to two weeks to check healing and to look at the pathology report if one was sent.
Recurrence and New Lesions
The lesion may recur if the base is left, and new lesions may appear elsewhere on the lids over time.
In addition, doctors can offer repeat treatment as needed to patients who dislike the appearance, and patients should know that the lesions are not dangerous.
Reinforce sun protection, which helps to keep the skin healthy.
Documentation
Photograph lesions before treatment, particularly pigmented ones, and keep a record of the number, size, and location.
A baseline image is valuable if a lesion changes or if there is a question later about whether the lesion has been present for a long time.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields JA, Shields CL. Eyelid, Conjunctival, and Orbital Tumors: An Atlas and Textbook. 3rd ed. Wolters Kluwer; 2016.
- Cook BE Jr, Bartley GB. Epidemiologic characteristics and clinical course of patients with malignant eyelid tumors in an incidence cohort in Olmsted County, Minnesota. Ophthalmology. 1999;106:746-750.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Oculofacial Plastic and Orbital Surgery. AAO; current edition.
Test yourself
A few questions straight from this article.
-
Seborrheic keratosis of the eyelid is a proliferation of which cells?
Seborrheic keratosis is an epidermal proliferation of immature keratinocytes, the most common benign epidermal tumor of older adults. -
What is the malignant potential of a seborrheic keratosis of the eyelid?
Seborrheic keratosis is benign, does not invade deeper tissue and does not turn into cancer, although new lesions may appear with time. -
Which appearance is characteristic of seborrheic keratosis on the eyelid skin?
The lesion is a well-demarcated, raised, waxy or verrucous plaque with a stuck-on appearance, as if it could be scraped off the skin. -
Which dermoscopic pattern supports a diagnosis of seborrheic keratosis of the eyelid?
Dermoscopy may show comedo-like openings, milia-like cysts and a cerebriform pattern, which support seborrheic keratosis; slit-lamp magnification can reveal similar features. -
In the differential of eyelid seborrheic keratosis, which lesion is a rough, scaly pink or tan patch on sun-damaged skin?
Actinic keratosis presents as a rough, scaly, pink or tan patch on sun-damaged skin, unlike the waxy, stuck-on plaque of seborrheic keratosis. -
A sudden eruption of many itchy seborrheic keratoses (sign of Leser-Trélat) has been reported mostly with which malignancy?
Reports link the sign mostly to gastrointestinal adenocarcinoma, though the association is debated; a sudden eruption merits general medical review and dermatology referral. -
Why is cryotherapy used with care near the eye when treating eyelid seborrheic keratosis?
Brief freezing with liquid nitrogen works but can cause depigmentation, and the globe should be protected with a corneal shield when freezing near the lid margin. -
When should a presumed eyelid seborrheic keratosis undergo biopsy or excision with histology?
Histology is indicated when the diagnosis is uncertain, the lesion has atypical features or it changes, because misdiagnosing a pigmented malignancy can be dangerous. -
Why may an eyelid seborrheic keratosis recur after treatment?
The lesion may recur if its base is left, and new lesions may also appear elsewhere on the lids over time; repeat treatment can be offered. -
After shave excision of an eyelid seborrheic keratosis, when should the patient be reviewed?
After applying antibiotic ointment, review in one to two weeks to check healing and to read the pathology report if tissue was sent.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.