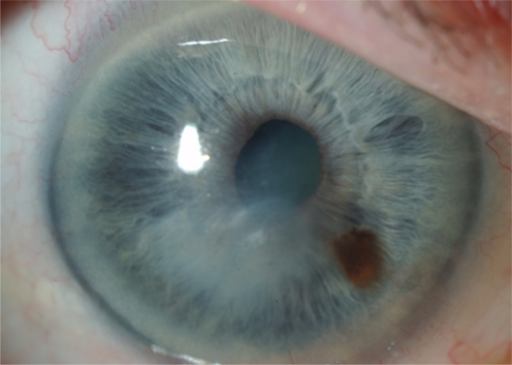
Contact lens-related microbial keratitis is the most serious complication of contact lens wear, and while the eye itself is normally quite resistant to infection, a contact lens disrupts several of the cornea’s natural defenses simultaneously, which is why a specific set of modifiable risk factors accounts for the overwhelming majority of cases and why understanding them matters more than knowing the organism list alone.
Why Contact Lenses Increase Infection Risk
A contact lens can reduce corneal oxygenation, cause subtle epithelial microtrauma with wear and removal, and create a biofilm-friendly surface where bacteria, particularly Pseudomonas aeruginosa, can adhere and multiply.
The lens itself and its storage case can also serve as a vehicle, carrying organisms into direct, sustained contact with the corneal surface in a way that does not occur with normal blinking and tear film clearance in a non-lens-wearing eye.
The Dominant Risk Factor: Overnight Wear
Sleeping in contact lenses, whether intentionally with an extended-wear lens or unintentionally with a daily-wear lens, is consistently identified as the single strongest modifiable risk factor for microbial keratitis, increasing risk severalfold compared with daily wear removed each night.
Overnight wear compounds corneal hypoxia, reduces the mechanical clearance of organisms that blinking normally provides, and extends the period of direct lens-cornea contact, all of which favor microbial adherence and invasion.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteOther Major Risk Factors
- Poor lens hygiene, including inadequate hand washing before lens handling, use of tap water for rinsing lenses or cases, and infrequent case replacement
- Topping off solution in the lens case rather than using fresh solution each time, which allows contamination to accumulate and concentrate over repeated use
- Contaminated lens cases, which can develop biofilm and serve as a persistent reservoir for organisms even when the lenses themselves are handled reasonably well
- Wearing lenses longer than their recommended replacement schedule
- Swimming or showering while wearing lenses, exposing them to waterborne organisms, including Acanthamoeba
- Smoking, which has been associated with increased microbial keratitis risk in contact lens wearers
- Prior corneal disease or ocular surface compromise
Lens Type and Material Considerations
Silicone hydrogel lenses, with their higher oxygen permeability, were developed in part to reduce hypoxia-related complications, though studies have shown that overnight wear risk with silicone hydrogel lenses, while sometimes lower than with older hydrogel materials, remains meaningfully elevated compared with daily wear removed each night, so the material itself does not eliminate the overnight wear risk.
Orthokeratology lenses, worn overnight to reshape the cornea temporarily, carry a distinct and notable association with microbial keratitis, including Acanthamoeba and Pseudomonas, related to the combination of overnight wear and the specific fitting characteristics of these lenses.
Organisms Involved
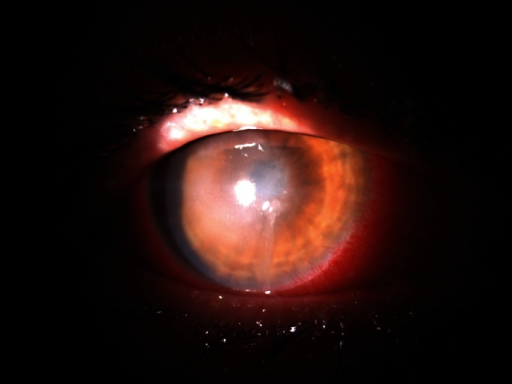
Pseudomonas aeruginosa is the most common and among the most aggressive causative organisms in contact lens-related bacterial keratitis, capable of causing rapid corneal destruction, and other gram-negative and gram-positive bacteria are also implicated.
Acanthamoeba keratitis, though less common overall, is disproportionately associated with contact lens wear, particularly with water exposure during lens wear, and is notable both for its severity and for the frequent diagnostic delay that occurs when it is initially mistaken for a more common herpetic or bacterial process (see Acanthamoeba keratitis).
Prevention Through Risk Factor Modification
- Consistent removal of lenses before sleep, for wearers not specifically fitted and monitored for extended wear
- Strict hand hygiene before any lens handling
- Using only fresh, not topped-off, contact lens solution, and replacing lens cases regularly, generally every one to three months
- Avoiding tap water contact with lenses or cases, and avoiding swimming or showering while wearing lenses
- Adhering to the manufacturer’s and prescriber’s recommended lens replacement schedule
- Prompt removal of lenses and seeking care for any new eye pain, redness, or discharge, rather than continuing to wear a lens through early symptoms
Clinical Significance
Because the majority of contact lens-related microbial keratitis cases are linked to identifiable, modifiable behaviors rather than being unpredictable or unavoidable, patient education on these specific risk factors at every contact lens fitting and follow-up visit is one of the most effective tools available for reducing the incidence of this potentially vision-threatening complication.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Stapleton F, Keay L, Edwards K, et al. The incidence of contact lens-related microbial keratitis in Australia. Ophthalmology. 2008;115:1655-1662.
- Dart JK, Radford CF, Minassian D, Verma S, Stapleton F. Risk factors for microbial keratitis with contemporary contact lenses: a case-control study. Ophthalmology. 2008;115:1647-1654.
- Stapleton F, Keay L, Jalbert I, Cole N. The epidemiology of contact lens related infiltrates. Optom Vis Sci. 2007;84:257-272.
- Cope JR, Collier SA, Rao MM, et al. Contact lens wearer demographics and risk behaviors for contact lens-related eye infections–United States, 2014. MMWR Morb Mortal Wkly Rep. 2015;64:865-870.
Test yourself
A few questions straight from this article.
-
What is the single strongest modifiable risk factor for contact lens-related microbial keratitis?
Sleeping in lenses, whether intentionally in extended-wear lenses or accidentally in daily-wear lenses, is consistently the strongest modifiable risk factor, raising risk severalfold over nightly removal. -
Which organism is the commonest and most aggressive cause of contact lens-related bacterial keratitis?
Pseudomonas aeruginosa is both the most common and among the most aggressive organisms in this setting, capable of causing rapid corneal destruction. -
Which lens property lets Pseudomonas adhere and multiply on a contact lens?
A lens creates a biofilm-friendly surface on which bacteria, particularly Pseudomonas aeruginosa, adhere and multiply, alongside reducing corneal oxygenation and causing epithelial microtrauma. -
Why does overnight contact lens wear particularly favour microbial invasion of the cornea?
Overnight wear compounds corneal hypoxia, removes the mechanical clearance of organisms that blinking provides, and extends the period of direct lens-cornea contact. -
Why is topping off contact lens solution in the case harmful?
Adding to old solution rather than using fresh solution each time lets contamination build up and concentrate in the case across repeated uses. -
How often should a contact lens storage case generally be replaced?
Regular case replacement, generally every one to three months, together with fresh solution, is part of prevention because cases develop biofilm and act as a persistent reservoir. -
What does the higher oxygen permeability of silicone hydrogel lenses achieve regarding overnight wear?
Silicone hydrogels were developed partly to reduce hypoxia-related complications, yet overnight wear risk remains meaningfully elevated versus nightly removal, so the material does not eliminate it. -
Which lens modality carries a distinct association with Acanthamoeba and Pseudomonas keratitis?
Orthokeratology lenses, worn overnight to reshape the cornea, carry a distinct and notable association with microbial keratitis including Acanthamoeba and Pseudomonas, tied to overnight wear and their fitting characteristics. -
Which wearer behaviour exposes contact lenses to Acanthamoeba?
Swimming or showering in lenses exposes them to waterborne organisms including Acanthamoeba, which is disproportionately associated with contact lens wear and water exposure. -
Which measure most effectively lowers the incidence of contact lens-related microbial keratitis?
Most cases trace to identifiable, modifiable behaviours, so teaching these specific risk factors at every contact lens fitting and follow-up is among the most effective available tools.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.