Contact lens hypoxia is a shortage of oxygen at the corneal surface caused by a lens that blocks its supply.
The cornea has no blood vessels, and it takes most of its oxygen directly from the air, so any lens that restricts this supply affects it.
Modern materials have greatly reduced the problem, but it has not disappeared.
How Contact Lens Hypoxia Develops
In the open eye, oxygen dissolves in the tear film and passes into the epithelium and stroma.
When the lid is closed, the oxygen comes from the palpebral conjunctiva, and the supply drops to about a third of the open-eye level.
A lens adds a barrier, and the amount of oxygen that passes depends on the oxygen transmissibility, written as Dk over t, which combines the material permeability and the lens thickness.
Oxygen Needs
Studies have shown that about 10 percent of oxygen at the cornea is needed to avoid edema in daily wear, and about 18 percent for extended wear (see the references).
Also, older hydrogel lenses had low transmissibility, and many failed these thresholds during sleep.
Silicone hydrogels transmit several times more oxygen, and in most daily wear conditions they meet the needs of the cornea.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteContact Lens Hypoxia: Signs of Hypoxia
- Corneal edema: blurred vision, haloes around lights, and a hazy cornea, often worse in the morning
- Epithelial microcysts: small cysts that appear after weeks of overwear
- Striae and folds in the posterior stroma from edema
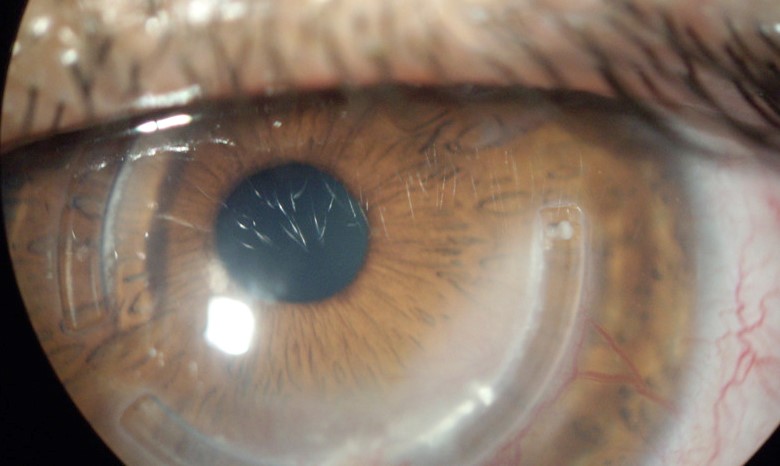
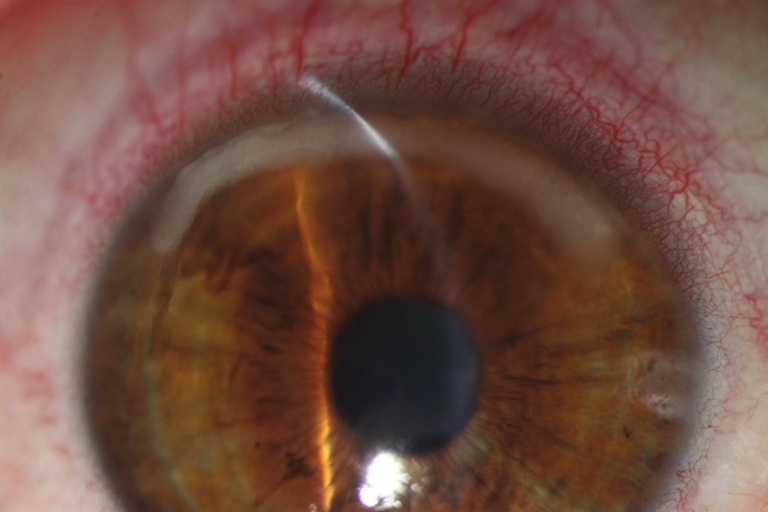
- Limbal hyperemia and neovascularization: vessels grow into the periphery (see corneal neovascularization)
- Endothelial blebs and polymegethism: changes in the size and shape of endothelial cells with long-term wear
- Reduced corneal sensation and epithelial thinning, which raise the infection risk
The changes may be subtle, so slit lamp examination is needed at each visit.
Risk Factors of Contact Lens Hypoxia
- Overnight or extended wear
- Low oxygen transmissibility lenses, such as old hydrogel or thick lenses
- Tight fitting, with little movement of the lens
- Dirty and deposited lenses
- Prolonged hours of wear, and wear while sleeping or in smoke
Differential Diagnosis of Contact Lens Hypoxia
- Toxic and solution reactions, which produce diffuse staining
- Mechanical injury, such as from a tight lens edge
- Infection, when the cornea is painful and an infiltrate is seen (see contact lens microbial keratitis risk factors)
- Corneal warpage and edema from other causes (see corneal edema causes)
The history of lens wear usually points to hypoxia.
Management and Prevention
- Stop wear until the cornea clears, and review in a few days
- Switch to a silicone hydrogel lens with high Dk over t, or to a daily disposable
- Reduce wear time and avoid sleeping in lenses
- Refit with a looser and thinner design when the fit is tight
- Teach care and hygiene, and replace lenses on schedule
- For rigid lenses, choose a high Dk material and a well-fitted design
Neovascularization often regresses after correction, though ghost vessels may remain.
Counselling
Tell patients that blurred vision after removing the lenses and red eyes at the end of the day are warning signs.
In addition, emphasize the benefit of silicone hydrogel lenses and of regular follow-up.
Dk, Dk/t, and Equivalent Oxygen Percentage
Dk is a property of the material, and Dk over t divides it by the thickness of the lens at the point of measurement.
A thick plus lens has a lower Dk over t at its center, and a minus lens is thinner in the center and thicker at the edge, so the oxygen supply differs between the center and the periphery.
The equivalent oxygen percentage is the amount of oxygen at the cornea that results from a given lens, and it is a more clinically useful number for matching a lens to the demands of the cornea.
Rigid and Hybrid Lenses
Rigid gas permeable lenses move on the cornea and allow tear exchange, which provides extra oxygen even with a lower Dk.
Large scleral lenses vault over the cornea with a fluid reservoir, and high Dk material is needed for adequate oxygen, together with a thin design and a regular check of the vault (see scleral lens fitting).
Special Groups
- Keratoconus patients often wear rigid and scleral lenses for long hours, so a review of the material and fit is useful
- Patients with a compromised cornea, such as after a graft, are more sensitive to oxygen loss
- Orthokeratology wearers sleep in lenses, and a high Dk is essential (see orthokeratology)
Follow-Up Visits
Examine for staining, edema, vessels, and endothelial changes at each visit, and measure the pachymetry if edema is suspected.
Document the vessels with a photograph, since the length of vessel growth helps to judge progress over time.
For the latest studies, see the PubMed results for contact lens hypoxia.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Holden BA, Mertz GW. Critical oxygen levels to avoid corneal edema for daily and extended wear contact lenses. Invest Ophthalmol Vis Sci. 1984;25:1161-1167.
- Efron N. Contact Lens Complications. 4th ed. Elsevier; 2018.
- Stapleton F, Keay L, Edwards K, et al. The incidence of contact lens-related microbial keratitis in Australia. Ophthalmology. 2008;115:1655-1662.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.