
Argon laser peripheral iridoplasty uses low-energy laser burns applied to the peripheral iris to contract and physically pull the iris root away from the trabecular meshwork, addressing angle closure that persists despite a patent peripheral iridotomy, discussed in its own dedicated article on this site.
It works through an entirely different mechanism than iridotomy: rather than relieving pupillary block by creating an alternate aqueous pathway, iridoplasty mechanically reshapes and flattens the peripheral iris configuration itself, making it the specific tool for angle closure driven by anatomy rather than by pupillary block.
Understanding this mechanistic difference clarifies why iridoplasty is reserved for a fairly specific subset of angle-closure presentations, mainly plateau iris syndrome, rather than being used as a general angle-closure treatment interchangeable with iridotomy.
The procedure is used considerably less often than iridotomy in everyday practice, reflecting how much less common plateau iris configuration is compared to straightforward pupillary block as a cause of angle closure overall.
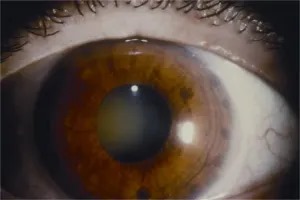
Mechanism
Low-energy, relatively large-spot laser burns applied to the peripheral iris cause localized tissue contraction, physically pulling and flattening the treated area of iris away from the adjacent trabecular meshwork and angle structures.
This mechanical effect is fundamentally different from iridotomy’s function, which relieves a pressure differential between the posterior and anterior chambers rather than physically reshaping the iris configuration itself.
Because the effect works by directly altering iris configuration and angle anatomy, iridoplasty is specifically suited to angle closure where the anatomic configuration of the peripheral iris, rather than pupillary block, is the primary mechanism causing angle crowding.
Plateau Iris Syndrome
In plateau iris configuration, the peripheral iris sits abnormally forward due to an anteriorly positioned ciliary body, crowding the angle even when pupillary block has already been fully relieved by a patent iridotomy.
Plateau iris syndrome describes this same anatomic configuration when it produces symptomatic or measurable angle closure, and it is the classic and most well-established indication for iridoplasty, since the mechanism, anatomic crowding by the iris root itself, matches exactly what iridoplasty is designed to correct.
Recognizing that an iridotomy alone will not resolve angle closure driven by plateau iris configuration is essential, since continuing to rely on iridotomy alone in this specific scenario leaves the underlying anatomic problem unaddressed.
Ultrasound biomicroscopy, discussed in relation to anterior segment imaging elsewhere on this site, is particularly useful for confirming a plateau iris configuration directly, since it can visualize the anteriorly positioned ciliary processes that standard anterior segment OCT cannot see behind the iris.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteOther Indications
- Acute angle-closure attack unresponsive to initial medical therapy, where iridoplasty can be used as an emergency measure to mechanically open the angle and break the acute attack while more definitive treatment is arranged
- Angle closure from a lens-related mechanism where the peripheral iris configuration continues contributing to angle crowding despite iridotomy
- Adjunctive use before or during laser iridotomy in an eye with a very shallow, difficult-to-access anterior chamber, where iridoplasty can temporarily deepen the chamber and facilitate safer iridotomy placement
Technique
The procedure is performed at the slit lamp using a gonioscopy-style contact lens, with low-energy, relatively large, long-duration laser spots applied circumferentially around the peripheral iris.
Energy settings are deliberately kept low, and spot size relatively large, distinguishing the technique from the higher-energy, smaller-spot settings used for iridotomy, since the goal here is gentle tissue contraction rather than creating a full-thickness perforation.
The procedure typically requires treatment around most or all of the iris circumference to achieve a meaningful, sustained widening effect on the angle.
Limitations and Complications
The effect of iridoplasty can diminish over time in some patients, sometimes requiring repeat treatment as the angle configuration gradually reverts toward its original, more crowded anatomy.
Transient intraocular pressure elevation, mild anterior chamber inflammation, and localized iris pigment changes at the treatment site are recognized, generally self-limited effects of the procedure.
Iridoplasty does not replace iridotomy when pupillary block is present, and it does not address the underlying anatomic predisposition permanently in the way that lens extraction can in an eye where the lens itself is a significant contributor to angle crowding.
For this reason, iridoplasty is often best understood as one component within a broader, individualized angle-closure management plan rather than a single definitive solution on its own.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Ritch R, Tham CC, Lam DS. Argon laser peripheral iridoplasty (ALPI): an update. Survey of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 10: Glaucoma.
- Ritch R. Plateau iris is caused by abnormally positioned ciliary processes. Journal of Glaucoma.
