
Reis-Bücklers corneal dystrophy is a rare, autosomal dominant anterior corneal dystrophy affecting Bowman’s layer, causing recurrent painful erosions and progressive superficial corneal scarring from early childhood.
It sits in a group of dystrophies once classified together as “Bowman’s layer dystrophies,” but genetic and histologic study has clarified that Reis-Bücklers and the related Thiel-Behnke dystrophy are distinct entities despite their overlapping clinical appearance.
Distinguishing the two matters mainly for prognosis and genetic counseling, since Reis-Bücklers tends to run a more severe course with earlier, more visually significant scarring.
Both conditions are rare, and most general ophthalmologists will encounter only a handful of cases across an entire career, which makes accurate classification at the time of diagnosis especially valuable for the patient’s long-term counseling.
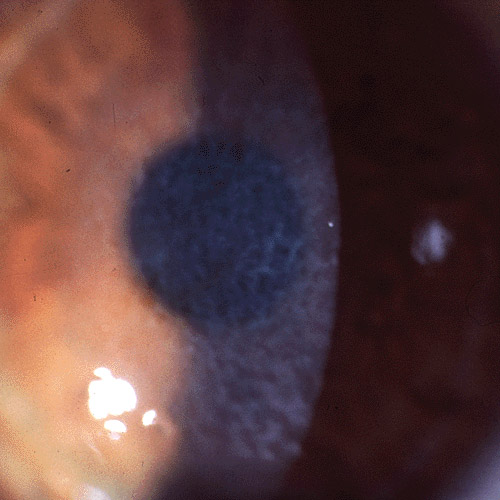
Genetics and Pathology
Reis-Bücklers dystrophy is caused by mutations in the TGFBI gene, the same gene responsible for several other corneal stromal dystrophies including granular and lattice dystrophy, though the specific mutation and the layer affected differ.
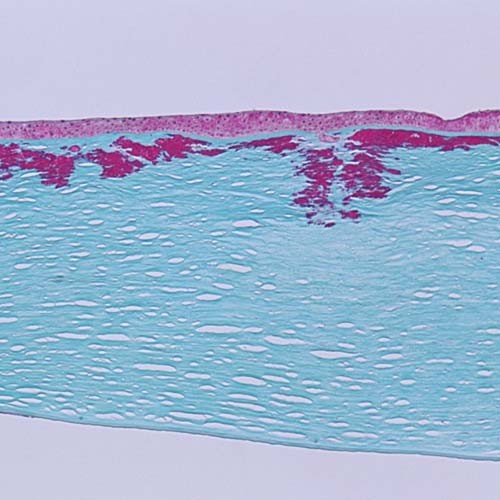
The abnormal protein deposits replace and disrupt Bowman’s layer with irregular, rod-shaped material, rather than affecting the stroma more diffusely the way granular or lattice dystrophy does.
Thiel-Behnke dystrophy, previously considered a milder variant of the same condition, is now recognized as a genetically and histologically distinct entity with a characteristic “curly fiber” pattern on electron microscopy, generally following a gentler clinical course.
Both conditions show essentially complete penetrance within affected families, so a positive family history in a child with recurrent erosions is a strong diagnostic clue even before any genetic confirmation is obtained.
Clinical Presentation
- Recurrent, painful corneal erosions beginning in early childhood, often the presenting complaint that brings the family to an ophthalmologist
- Progressive, irregular, gray-white superficial opacities concentrated in the central and paracentral cornea, coalescing over time into a honeycomb or reticular pattern
- Gradually declining vision as the opacities thicken and become more confluent, typically becoming visually significant by early-to-mid adulthood
- Reduced corneal sensation over the affected area in some patients, a secondary consequence of the recurrent epithelial disruption rather than a primary neurotrophic process
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDifferential Diagnosis
Thiel-Behnke dystrophy is the closest clinical mimic, distinguished definitively by genetic testing or, when unavailable, by the generally more indolent course and characteristic ultrastructural appearance on electron microscopy.
Granular and lattice corneal dystrophy, discussed in their own dedicated articles on this site, affect the stroma rather than Bowman’s layer specifically, producing a deeper, differently distributed pattern of opacity.
Recurrent corneal erosion syndrome from other causes, including epithelial basement membrane dystrophy, needs to be considered in any patient with recurrent erosions, though the progressive Bowman’s layer opacification of Reis-Bücklers is not a feature of those other conditions.
Diagnostic Evaluation
The diagnosis is often suspected from the characteristic clinical appearance and family history, given the autosomal dominant inheritance pattern with high penetrance.
Genetic testing for the relevant TGFBI mutation can confirm the diagnosis and distinguish it definitively from Thiel-Behnke dystrophy when the clinical picture is ambiguous.
Confocal microscopy or, when tissue is available from a prior procedure, histopathology and electron microscopy can characterize the specific deposit pattern when genetic testing is not accessible.
Corneal topography is also worth obtaining as baseline documentation, since progressive Bowman’s layer scarring can eventually induce irregular astigmatism on top of the direct visual impact of the opacity itself.
Management
Recurrent erosions are managed with the same general measures used for any erosive corneal condition: lubrication, bandage contact lenses during acute episodes, and, for frequent recurrences, anterior stromal micropuncture or phototherapeutic keratectomy to promote more durable epithelial adhesion.
Phototherapeutic keratectomy, ablating the superficial opacified tissue with an excimer laser, can improve both symptoms and vision, though the dystrophy characteristically recurs in the treated area over subsequent years since the underlying genetic defect is not corrected.
Penetrating or, more often now, lamellar keratoplasty is reserved for eyes with dense, vision-limiting scarring that has progressed beyond what surface treatment can adequately address, with the same expectation that recurrence can eventually affect the graft as well.
Families benefit from understanding early that this is a lifelong, recurring condition rather than one treated definitively at a single point, since planning around that expectation shapes how aggressively surface treatment is pursued at each stage.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Weiss JS, Møller HU, Aldave AJ, et al. IC3D classification of corneal dystrophies — edition 2. Cornea.
- Munier FL, Korvatska E, Djemai A, et al. Kerato-epithelin mutations in four 5q31-linked corneal dystrophies. Nature Genetics.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea.
