

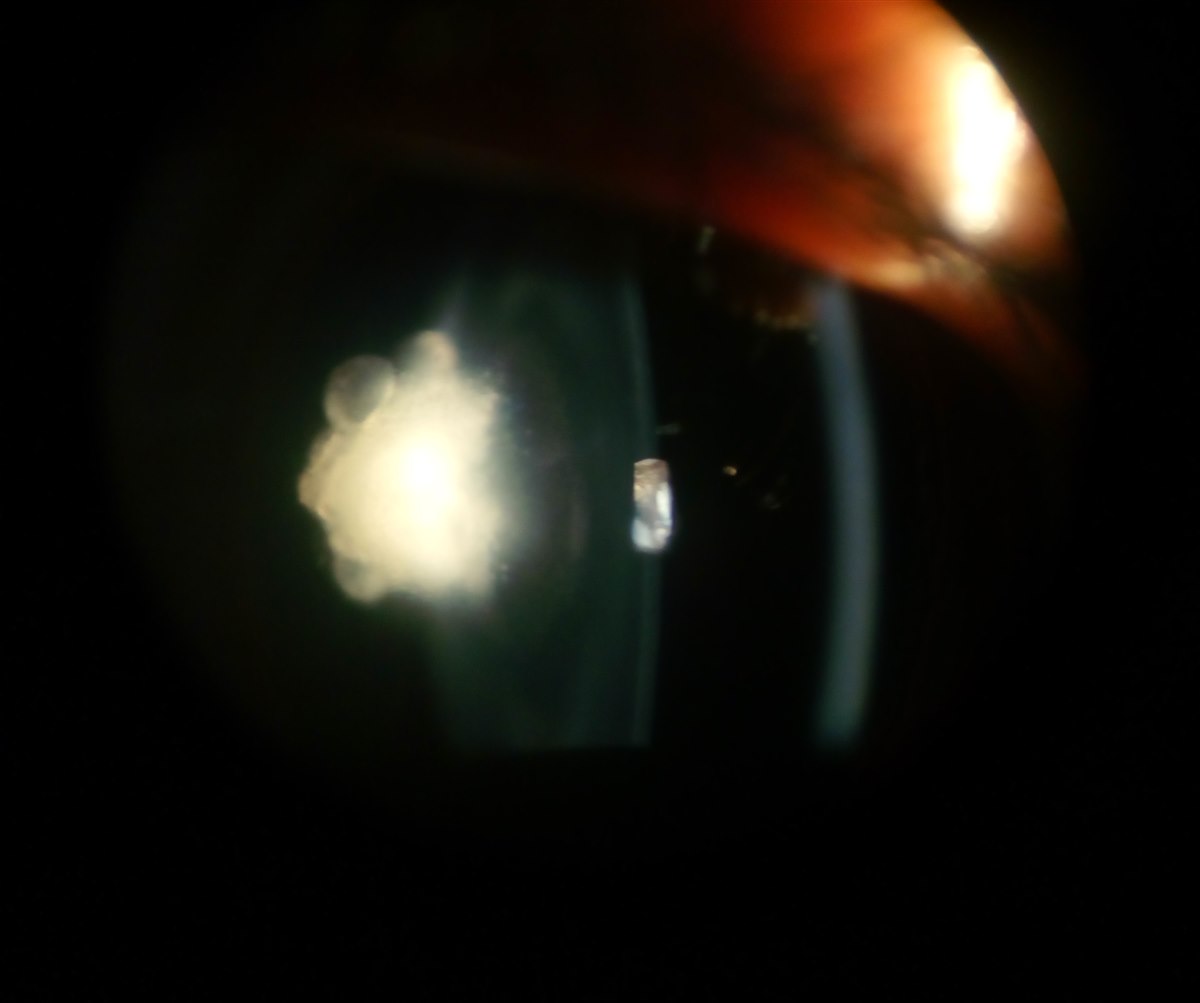
Posterior polar cataract is a congenital, typically stationary opacity located precisely at the back pole of the lens, and it punches well above its weight in surgical importance relative to its modest size.
The reason is anatomic: the posterior capsule beneath a posterior polar cataract is frequently thin, deficient, or in some cases entirely absent, which converts a routine cataract extraction into one of the higher-risk procedures in the field for posterior capsule rupture and vitreous loss.
Recognizing the pattern preoperatively — not discovering it for the first time intraoperatively — is what allows a surgeon to plan for that risk rather than react to it, and is one of the clearest examples in ophthalmology of how a careful preoperative exam directly changes intraoperative decision-making.
Pathogenesis
Posterior polar cataract is thought to arise from a persistent remnant of the fetal hyaloid vascular system or from abnormal posterior lens epithelial migration during embryonic development, resulting in a discrete plaque of opacified lens material adherent to, and often disrupting, the posterior capsule at that single point.
Most cases are sporadic, though autosomal dominant inheritance with variable expressivity occurs in some families, which is worth asking about when the finding is identified.
Unlike most other congenital cataract types, posterior polar cataract is typically unilateral or markedly asymmetric between eyes, which is itself a useful clinical clue when trying to distinguish it from other congenital lens opacities.
Clinical Presentation
Visual impact depends heavily on the density and size of the opacity: small, less dense lesions may be discovered incidentally on a routine exam with minimal effect on acuity, while larger or denser opacities cause significant, sometimes amblyogenic vision loss in a child if not identified and addressed early.
In adults, posterior polar cataracts are typically stable for years before a patient begins to notice glare and reduced vision, sometimes prompted by only a modest amount of progression.
Because the opacity sits directly in the visual axis, symptoms — when present — tend to resemble those of posterior subcapsular cataract: disproportionate glare and difficulty in bright light relative to the size of the lesion, with an earlier impact on near vision than distance vision in some patients.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteExam Findings
- A discrete, often onion-skin or plaque-like white opacity centered precisely at the posterior pole on slit-lamp or retroillumination exam
- Typically unilateral or markedly asymmetric
- Sharp, well-demarcated borders, distinguishing it from the more diffuse, granular appearance of acquired posterior subcapsular cataract
- Relatively clear surrounding lens, at least early in the course, before any secondary changes develop
The sharply demarcated, disc-like appearance and its fixed central position are what separate posterior polar cataract from acquired PSC on exam, even though the visual symptoms they produce can be similar.
Differential Diagnosis
- Posterior subcapsular cataract (acquired) — granular, less sharply defined, associated with steroid use, inflammation, or other acquired risk factors rather than present from birth
- Posterior lenticonus — a bulging, rather than opaque, posterior capsule contour, sometimes with an overlying oil-droplet reflex, though the two can coexist
- Mittendorf’s dot — a small, isolated remnant of the fetal hyaloid artery on the posterior capsule, usually incidental and visually insignificant, distinguishable by its typically smaller size and lack of associated capsular thinning
- Persistent fetal vasculature — a broader spectrum of hyaloid remnant abnormalities, of which some posterior polar cataracts may represent a mild, isolated expression
Surgical Considerations
The central surgical concern is the frequently deficient posterior capsule directly beneath the opacity; hydrodissection in the standard fashion risks forcing fluid through a pre-existing capsular defect and precipitating posterior capsule rupture with vitreous prolapse.
Modified techniques are used specifically to reduce this risk: gentle hydrodelineation rather than aggressive hydrodissection, avoiding rotational stress on the lens, and a “dry” or minimal-manipulation approach to the posterior plaque, sometimes leaving a thin layer of the opacity in place rather than attempting complete removal if the capsule appears to be at risk.
Surgeons who identify a posterior polar cataract preoperatively typically counsel patients specifically about the elevated risk of posterior capsule rupture, plan for the possibility of anterior vitrectomy, and may adjust the intraocular lens strategy (such as considering sulcus fixation) in case capsular support is compromised intraoperatively.
This preoperative planning is the single biggest factor separating a well-managed posterior polar cataract case from one complicated by unexpected vitreous loss, which is why identifying the pattern before the day of surgery, rather than discovering it at the microscope, matters so much for outcome.
Prognosis
With appropriate preoperative recognition and modified surgical technique, visual outcomes after posterior polar cataract surgery are generally good, though the complication rate remains measurably higher than for routine cataract surgery even in experienced hands, which is a useful, honest point to include when counseling a patient before surgery.
In children, prompt treatment of a visually significant posterior polar cataract — combined with amblyopia management — is important, because unilateral presentation carries a real risk of amblyopia if correction is delayed, and the elevated intraoperative risk should be weighed carefully alongside, rather than as a reason to postpone, timely surgical intervention.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Vasavada A, Singh R. Phacoemulsification in eyes with posterior polar cataract. Journal of Cataract and Refractive Surgery.
- Osher RH, Yu BC, Koch DD. Posterior polar cataracts: a predisposition to intraoperative posterior capsular rupture. Journal of Cataract and Refractive Surgery.
- Das S, Nayak S. Posterior polar cataract: is it different? Indian Journal of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 11: Lens and Cataract.
Test yourself
A few questions straight from this article.
-
Where is the opacity of a posterior polar cataract located?
It is a congenital, typically stationary opacity sitting exactly at the back pole of the lens, directly within the visual axis. -
What makes posterior polar cataract surgery unusually hazardous?
The capsule beneath the plaque is frequently thin, deficient or absent, converting a routine extraction into a high-risk case for posterior capsule rupture and vitreous loss. -
What is the presumed developmental origin of a posterior polar cataract?
The plaque is thought to arise from a persistent fetal hyaloid vascular remnant or abnormal posterior lens epithelial migration during embryonic development. -
What inheritance pattern is described for posterior polar cataract?
Most cases are sporadic, but autosomal dominant inheritance with variable expressivity occurs in some families, making a family history worth asking about. -
How does the laterality of posterior polar cataract differ from most congenital cataracts?
Unlike most other congenital lens opacities, posterior polar cataract is usually unilateral or markedly asymmetric, which is itself a useful diagnostic clue. -
Which exam feature separates posterior polar cataract from acquired posterior subcapsular cataract?
The sharply demarcated, onion-skin plaque fixed at the posterior pole distinguishes it from the diffuse, granular appearance of acquired posterior subcapsular cataract. -
Which surgical step is specifically avoided in a posterior polar cataract?
Standard hydrodissection can force fluid through a pre-existing capsular defect and precipitate rupture with vitreous prolapse; gentle hydrodelineation is used instead. -
Which intraocular lens contingency is planned before posterior polar cataract surgery?
Surgeons counsel about rupture risk, plan for possible anterior vitrectomy, and may consider sulcus fixation should capsular support fail intraoperatively. -
What should a patient be told about outcomes after posterior polar cataract surgery?
With preoperative recognition and modified technique results are generally good, though the complication rate remains measurably higher than routine surgery even in expert hands. -
Why does a visually significant posterior polar cataract in a child need timely surgery?
Because the cataract is usually unilateral, delayed correction risks amblyopia; the raised intraoperative risk is weighed alongside, not used to postpone, timely surgery.
