Eyelid cysts are common benign lesions that arise from glands, hair follicles or trapped epithelium in the lid.
Most are painless and slow growing.
However, they differ in origin, appearance and recurrence risk.
Therefore, naming the type correctly guides both counseling and surgery.
What Are Eyelid Cysts?
A true cyst is a cavity lined by epithelium and filled with fluid or keratin.
The lining determines the content, so a gland cyst holds fluid while an epidermal cyst holds keratin.
As a result, incomplete removal of the wall often leads to recurrence.
Cyst of Moll
A cyst of Moll is an apocrine hidrocystoma of the lid margin.
It appears as a smooth, round, translucent bubble near the lash line.
In addition, it contains clear fluid and transilluminates well with a slit beam.
Some lesions take a bluish tint because of light scattering through the fluid (see eyelid hidrocystoma).
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteCyst of Zeis
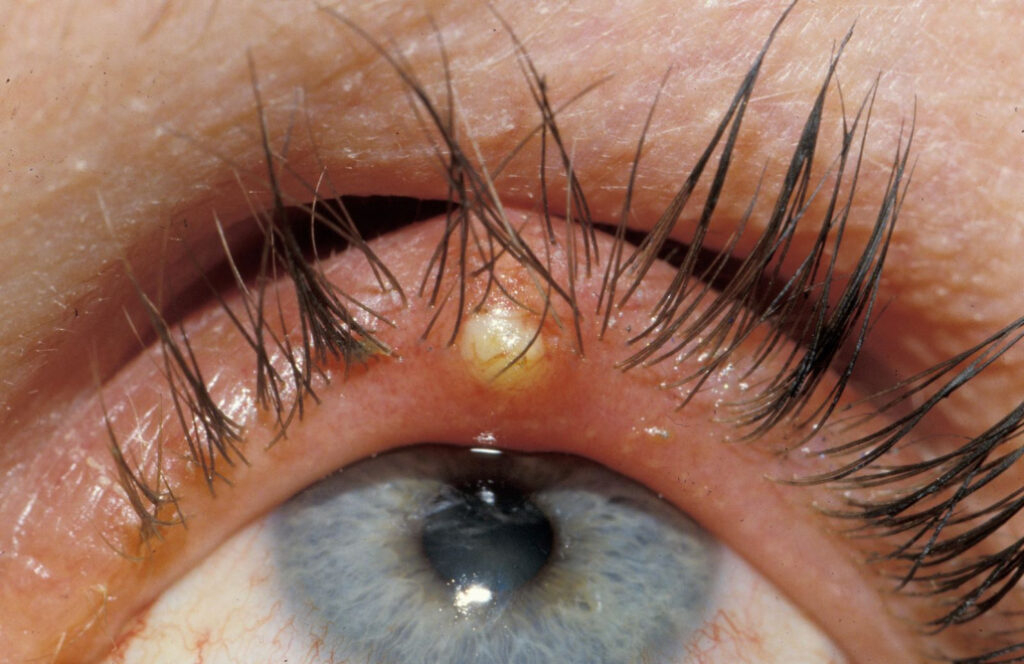
The glands of Zeis are sebaceous glands that open into the lash follicles.
When a duct blocks, a small opaque nodule forms on the anterior lid margin.
Unlike a cyst of Moll, it looks yellowish and transilluminates poorly.
Therefore, light behavior offers a quick bedside clue between the two.
Epidermoid and Inclusion Eyelid Cysts
Epidermoid cysts are firm, white or yellow nodules filled with keratin.
They often sit in the lid skin away from the margin.
Some follow trauma or surgery, because surface epithelium becomes implanted in the dermis.
These are called epidermal inclusion cysts.
Rupture can then provoke a marked inflammatory reaction that mimics infection.
Milia and Other Small Eyelid Cysts
Milia are tiny, pearly white keratin cysts, often multiple.
They are common in newborns and after skin injury in adults.
Also, they are easily confused with syringomas or xanthelasma (see eyelid syringoma).
Why a Chalazion Is Not a True Cyst
A chalazion is a lipogranuloma caused by a blocked meibomian gland.
It lacks an epithelial lining, so histology shows granulomatous inflammation.
Clinically, it sits within the tarsus and is felt away from the lid margin.
In addition, eversion may show a red or gray patch on the conjunctival side (see chalazion).
Comparing Eyelid Cysts at a Glance
- Cyst of Moll: lid margin, translucent, clear fluid, transilluminates, excision or marsupialization
- Cyst of Zeis: lid margin at a lash, opaque yellow, sebaceous content, excision
- Epidermoid cyst: lid skin, firm white, keratin filled, complete excision
- Inclusion cyst: previous wound or incision site, keratin filled, complete excision
- Milia: tiny, multiple, pearly white, de-roofing if bothersome
- Chalazion: within tarsus, firm, no true lining, compresses then incision and curettage
Slit Lamp Clues for Eyelid Cysts
First, note the exact position relative to the gray line and the lashes.
Next, use retroillumination or a narrow beam to test translucency.
Then, palpate for mobility and attachment to the tarsus.
Finally, evert the lid to inspect the conjunctival surface.
History That Narrows the Diagnosis
Duration and growth rate matter more than size.
For example, a lump present for many months with no change suggests a benign cyst.
Previous lid surgery or injury raises suspicion for an inclusion cyst.
Recurrent lumps at one site, however, need closer scrutiny.
Red Flags That Mimic Benign Lumps
Some malignant tumors present as a simple bump.
Watch for these features:
- Loss of lashes (madarosis) over the lesion
- Ulceration, bleeding or telangiectatic vessels
- Distortion of the lid margin architecture
- A “chalazion” that recurs at the same site
- Rapid growth or a violaceous color
Sebaceous carcinoma in particular can hide behind recurrent chalazia (see sebaceous gland carcinoma).
When to Biopsy
Send tissue whenever any red flag is present.
Also, submit recurrent or atypical lesions for histopathology.
Because the clinical look can deceive, a low threshold protects the patient.
Treatment of Eyelid Cysts
Small, asymptomatic cysts can simply be observed.
However, needle puncture usually gives only temporary relief, because the lining remains.
Complete excision with the intact wall offers the lowest recurrence risk.
For thin hidrocystomas, marsupialization is a reasonable alternative.
Counseling Patients With Eyelid Cysts
Most patients worry about cancer, so explain the benign nature clearly.
Also, discourage squeezing, which can rupture the cyst and inflame the lid.
Discuss recurrence risk honestly when you choose between drainage and excision.
Follow-Up
Then, reassess any recurrence at the same site with fresh suspicion.
Patients with chronic blepharitis benefit from regular lid care (see eyelid hygiene).
Pitfalls to Avoid
- Labeling every lid lump a chalazion without examining the margin
- Draining an epidermoid cyst and expecting a cure
- Skipping histology on a recurrent lesion
- Ignoring lash loss over a “benign” bump
- Damaging lash follicles during margin excision


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Elsevier; 2016.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Oculofacial Plastic and Orbital Surgery. San Francisco: AAO; 2023.
- Pe’er J. Pathology of eyelid tumors. Indian J Ophthalmol. 2016;64:177-190.
- Deprez M, Uffer S. Clinicopathological features of eyelid skin tumors: a retrospective study of 5504 cases and review of literature. Am J Dermatopathol. 2009;31:256-262.
- Yanoff M, Sassani JW. Ocular Pathology. 8th ed. Elsevier; 2020.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.