
HLA-B27 anterior uveitis is the most common identifiable cause of acute anterior uveitis in many populations, and it has a recognizable clinical pattern that should prompt a systemic workup even in a patient with no known joint disease.
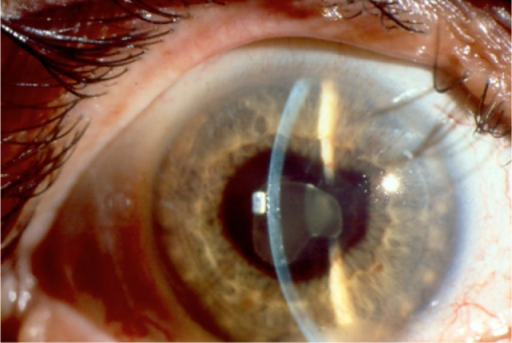
HLA-B27 anterior uveitis often brings the patient to the eye clinic first, so the ophthalmologist is often the one who opens the door to a spondyloarthropathy diagnosis.
HLA-B27 Anterior Uveitis: Clinical Pattern
HLA-B27-associated uveitis typically behaves in a characteristic way.
- Acute onset, with pain, redness, and photophobia developing over a day or two
- Unilateral in a given episode, though it may alternate sides between recurrences
- Nongranulomatous, with fine keratic precipitates rather than mutton-fat deposits
- Marked anterior chamber reaction, sometimes with fibrin and, in severe cases, a hypopyon
- Recurrent, with episodes that resolve completely between attacks in most patients
Posterior segment involvement is uncommon, though cystoid macular edema and mild vitritis can occur in more severe or recurrent disease.
Systemic Associations
HLA-B27 is strongly linked to the spondyloarthropathies.
- Ankylosing spondylitis, the classic association, with inflammatory back pain and sacroiliitis
- Reactive arthritis, following genitourinary or gastrointestinal infection
- Psoriatic arthritis
- Inflammatory bowel disease-associated arthropathy (see uveitis in inflammatory bowel disease)
Many patients with HLA-B27 uveitis have no diagnosed systemic disease at the time of their first eye episode, and a substantial proportion are found to have undiagnosed axial spondyloarthritis when specifically asked about back symptoms and referred for imaging.
Evaluation
A history focused on inflammatory back pain is worth taking in every patient with a first episode of acute anterior uveitis.
- Ask about morning stiffness lasting more than 30 minutes, back pain that improves with exercise and worsens with rest, and any personal or family history of psoriasis, inflammatory bowel disease, or arthritis
- HLA-B27 testing, which is positive in a large majority of patients with this uveitis pattern, though a negative result does not exclude the pattern clinically
- Referral to rheumatology when back symptoms or a positive HLA-B27 result raise suspicion for spondyloarthritis, since imaging of the sacroiliac joints may be needed
- Screening for other spondyloarthropathy features, including psoriasis and inflammatory bowel symptoms
Recognizing the pattern clinically is often more useful in the acute setting than waiting for a laboratory result, since treatment should not be delayed.
Differential Diagnosis
- Herpetic anterior uveitis, also unilateral and recurrent, but often with elevated IOP during the attack and sometimes corneal involvement
- Fuchs heterochromic iridocyclitis, which is chronic and low-grade, unlike the acute severe attacks of HLA-B27 disease (see Fuchs heterochromic iridocyclitis)
- Behçet disease, which tends to be more posterior and bilateral over time (see Behçet uveitis)
- Sarcoid uveitis, usually more chronic and granulomatous
Management
Topical corticosteroids and cycloplegics control most attacks quickly, and treatment should be started promptly and tapered as inflammation settles rather than stopped abruptly.
Posterior synechiae are a real risk in severe attacks, so adequate cycloplegia matters.
Frequent recurrences may warrant a discussion with rheumatology about whether treating the underlying spondyloarthropathy, including with biologic therapy for severe axial disease, could reduce the frequency of eye attacks.
Prognosis
Most attacks resolve fully with treatment, and vision is usually preserved between episodes.
Recurrent disease over years can occasionally lead to synechiae, cataract, or glaucoma, which is one more reason to identify and manage the underlying systemic disease rather than treating each attack in isolation.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Chang JH, McCluskey PJ, Wakefield D. Acute anterior uveitis and HLA-B27. Surv Ophthalmol. 2005;50:364-388.
- Rothova A, van Veenedaal WG, Linssen A, Glasius E, Kijlstra A, de Jong PT. Clinical features of acute anterior uveitis. Am J Ophthalmol. 1987;103:137-145.
- Zeboulon N, Dougados M, Gossec L. Prevalence and characteristics of uveitis in the spondyloarthropathies: a systematic literature review. Ann Rheum Dis. 2008;67:955-959.
- Haroon M, O’Rourke M, Ramasamy P, Murphy CC, FitzGerald O. A novel evidence-based detection of undiagnosed spondyloarthritis in patients presenting with acute anterior uveitis. Ann Rheum Dis. 2015;74:1990-1995.
