Congenital hereditary endothelial dystrophy (CHED) is a rare inherited disorder of the corneal endothelium that causes bilateral, diffuse corneal clouding at birth or in early infancy. In ched ophthalmology, the first job is to exclude congenital glaucoma, because the two look alike but need different, and differently urgent, care. Most affected children eventually need a corneal transplant.
CHED Ophthalmology: What the Eye Looks Like
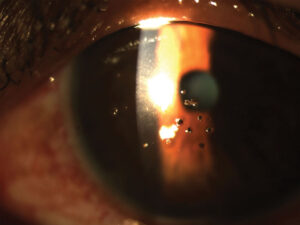
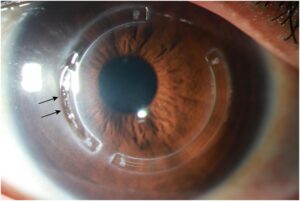
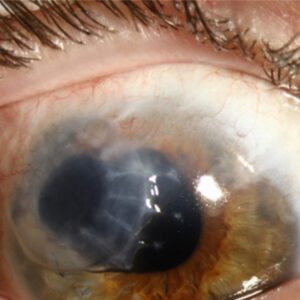
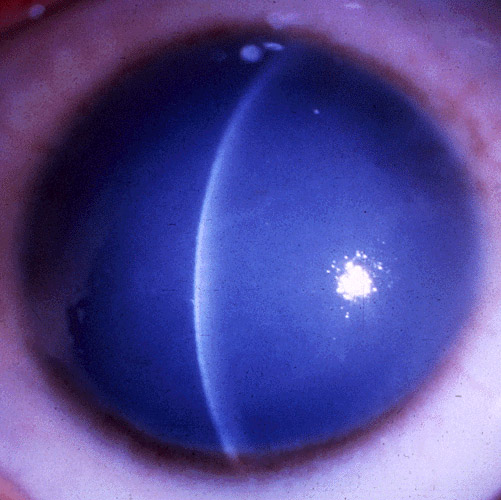
A CHED eye shows a uniformly hazy, ground-glass cornea in both eyes, usually symmetric, with a normal corneal diameter. Photographs show a milky blue-gray cornea without the enlarged, stretched look of buphthalmos. The epithelium and stroma are edematous, and the cornea is often two to three times its normal thickness.
Parents often describe cloudy or bluish eyes from the first days of life. Vision is reduced, and many infants develop nystagmus because the clouded corneas deliver poor, blurred input during the critical period of visual development.
Signs and Symptoms of CHED
- Bilateral, diffuse corneal clouding at birth or within the first weeks of life, usually symmetric between the two eyes
- Markedly increased corneal thickness, unlike congenital glaucoma, where corneal enlargement and Descemet membrane tears, rather than diffuse thickening, drive the clouding
- Photophobia and tearing, generally milder than the marked photophobia and blepharospasm of congenital glaucoma
- Nystagmus, often secondary to the blurred visual input from the clouded corneas
- Normal intraocular pressure and normal corneal diameter, the most useful features for separating CHED from congenital glaucoma
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteIs CHED a Corneal Dystrophy? Genetics and Inheritance
CHED is a corneal dystrophy, and the IC3D classification places it among the endothelial dystrophies. The form seen in practice is autosomal recessive, caused by mutations in SLC4A11. It presents with dense, opaque clouding at birth and, commonly, nystagmus.
Older schemes described a milder autosomal dominant form with later onset, photophobia and tearing, no nystagmus, and slow progression. Many authorities now regard that form as part of posterior polymorphous corneal dystrophy, so nearly all clinically significant cases are the recessive, congenital type.
SLC4A11 mutations also cause Harboyin syndrome, in which CHED accompanies progressive sensorineural hearing loss, so affected children deserve a hearing assessment. Variants in the same gene have been reported in late-onset Fuchs disease, a link explored in our review of Fuchs endothelial dystrophy genetics.
Pathophysiology
The defect impairs endothelial pump function from birth. The endothelium cannot clear fluid from the stroma, so the cornea develops diffuse, bilateral stromal and epithelial edema in the first days of life and takes on a hazy, ground-glass look. Histology shows a diffusely thickened Descemet membrane and sparse, atrophic endothelial cells.
Acquired endothelial disease such as Fuchs endothelial corneal dystrophy develops from progressive endothelial cell loss over decades. CHED instead reflects a developmental failure of endothelial function that is present from the start, which is why the clouding is already established in infancy.
CHED Versus Congenital Glaucoma
Congenital glaucoma clouds the cornea by a different mechanism. Raised intraocular pressure enlarges the globe (buphthalmos) and breaks Descemet membrane (Haab striae), letting aqueous enter and edematize the stroma. The corneal diameter is enlarged, pressure is elevated, and photophobia, tearing, and blepharospasm are usually more prominent than in CHED.
Congenital glaucoma is a true emergency that needs prompt surgery to prevent irreversible optic nerve damage. Any infant with cloudy corneas therefore needs pressure measurement and careful corneal diameter assessment, often under anesthesia, before anyone settles on CHED. A horizontal diameter above 11 mm in a newborn is suspicious for glaucoma.
Other Causes of Cloudy Corneas in Infants
- Congenital glaucoma: raised pressure, an enlarged cornea, and Haab striae; the alternative to exclude first
- Birth trauma (forceps injury): usually unilateral or asymmetric, with a history of instrumented delivery and vertical or oblique Descemet membrane tears
- Sclerocornea: an opaque, sclera-like cornea, often worse peripherally with a blurred limbus, unlike the diffuse clouding of CHED
- Peters anomaly: a central opacity with iris or lens adhesions to the posterior cornea, covered in our article on Peters anomaly
- Congenital hereditary stromal dystrophy: a dominant disorder with flaky or feathery stromal opacities, normal corneal thickness, and a clear epithelium; see our overview of corneal stromal dystrophy
- Metabolic and storage disorders (mucopolysaccharidoses): usually accompanied by systemic findings, and worth considering when clouding comes with other developmental abnormalities
- Congenital infection (herpes simplex, rubella): a maternal and perinatal history usually points to this category
Workup and Imaging
Evaluation usually needs examination under anesthesia. The team measures intraocular pressure, horizontal corneal diameter, and central corneal thickness, and inspects Descemet membrane and the angle. Anterior segment OCT shows the diffusely thick cornea, and ultrasound biomicroscopy helps exclude Peters anomaly and sclerocornea when the view is poor.
Specular microscopy is rarely possible through an edematous cornea, so imaging and clinical findings carry the diagnosis. Molecular testing for SLC4A11 confirms it, guides counseling for the family, and prompts a hearing screen.
Can CHED Recover on Its Own?
CHED does not recover on its own. The recessive form is generally stable rather than resolving, so the clouding persists and visual development stays at risk unless the cornea is treated. Hypertonic saline may reduce epithelial edema temporarily but does not correct the endothelial defect.
Transient neonatal corneal edema from birth trauma can clear over weeks, which is why delivery history and a repeat examination matter before labeling a baby with CHED. Persistent bilateral clouding with thick corneas points toward CHED.
Management
Severe amblyopia is a real risk because CHED degrades visual input from birth. Once the diagnosis is established and congenital glaucoma is confidently excluded, prompt intervention during the critical period of early visual development is generally appropriate rather than watchful waiting.
Corneal transplantation is the definitive treatment and is done as early as reasonably feasible. Penetrating keratoplasty is the traditional procedure, and endothelial keratoplasty (DSAEK or DMEK) is increasingly used in carefully selected children.
Pediatric grafting carries its own challenges, including a higher rejection risk than adult keratoplasty and the need for aggressive, coordinated amblyopia therapy after surgery. Outcomes are better when surgery happens early and follow-up is close.
Genetic counseling addresses recurrence risk, which is 25% per pregnancy with autosomal recessive inheritance. Long-term pediatric ophthalmic follow-up covers the graft, amblyopia, refractive error, and nystagmus, and continues well beyond the postoperative period into later childhood.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Kumar A, Bhattacharjee S, Prakash DR, Sadanand CS. Genetic analysis of two Indian families affected with congenital hereditary endothelial dystrophy: two novel mutations in SLC4A11. Molecular Vision.
- Weiss JS, Møller HU, Aldave AJ, et al. IC3D classification of corneal dystrophies — edition 2. Cornea.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 6: Pediatric Ophthalmology and Strabismus.
Test yourself
A few questions straight from this article.
-
Mutations in which gene underlie congenital hereditary endothelial dystrophy (CHED)?
CHED is now understood as a spectrum related to SLC4A11 mutations. -
Which inherited form of CHED is most commonly encountered and generally more severe?
The recessive, congenital-onset form accounts for the great majority of clinically significant cases and presents at birth with dense, opaque corneal clouding. -
What causes the corneal clouding in CHED?
The endothelium cannot clear fluid from the stroma from birth, producing diffuse bilateral stromal and epithelial oedema and a ground-glass cornea. -
How does CHED differ fundamentally from Fuchs endothelial dystrophy?
Fuchs dystrophy develops from progressive endothelial cell loss over decades, whereas CHED reflects endothelial function that never worked normally. -
Which combination of findings points to CHED rather than congenital glaucoma in a cloudy infant cornea?
Normal intraocular pressure and normal corneal diameter are the single most important distinguishing feature, and confirming them is the central task of the initial evaluation. -
By which mechanism does congenital glaucoma cloud the infant cornea?
Elevated intraocular pressure causes buphthalmos and breaks in Descemet's membrane known as Haab's striae, allowing aqueous to enter the stroma. -
Why does nystagmus often develop in children with CHED?
The clouded corneas give blurred visual input during the critical period, and nystagmus develops secondary to that deprivation. -
Which features suggest birth trauma rather than CHED as the cause of neonatal corneal clouding?
Forceps injury is typically unilateral or asymmetric, follows a difficult or instrumented delivery, and often shows vertical or oblique Descemet membrane tears. -
Why is prompt corneal transplantation preferred over observation once CHED is confirmed?
CHED impairs visual input from birth, so transplantation is performed as early as reasonably feasible once congenital glaucoma has been confidently excluded. -
Which challenge distinguishes paediatric corneal transplantation for CHED from adult keratoplasty?
Paediatric keratoplasty carries a higher rejection risk than adult surgery and demands aggressive, coordinated amblyopia treatment afterwards.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.