The Early Treatment for Retinopathy of Prematurity (ETROP) trial showed that treating high-risk eyes earlier than the old threshold gives better outcomes.
It created the type 1 and type 2 classification used worldwide.
It reshaped screening and treatment of premature infants (see retinopathy of prematurity diagnosis and management).
Design of the Early Treatment for Retinopathy of Prematurity Trial
The study enrolled 401 infants with bilateral high-risk prethreshold disease, and one eye of each infant was randomized to treatment at the high-risk stage, while the other was managed conventionally, with treatment at threshold disease (see the references).
In addition, risk was calculated with a model based on birth weight, the zone, stage, and presence of plus disease.
Also, the primary outcomes were visual acuity at nine months and structural outcome by retinal examination.
Early Treatment for Retinopathy of Prematurity: Results at Nine Months and Six Years
Unfavorable visual outcomes occurred in 14.3 percent of eyes with early treatment, whereas 19.5 percent had them with conventional management (see the references).
Also, unfavorable structural outcomes were 9.1 percent against 15.6 percent.
At six years, unfavorable acuity was 25 percent and 32 percent, while structural results kept the same direction (see the references).
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteType 1 Disease: Treat in Early Treatment for Retinopathy of Prematurity
- Zone I, any stage with plus disease
- Zone I, stage 3 without plus disease
- Zone II, stage 2 or 3 with plus disease
When type 1 disease appears, start treatment within 48 hours (see ROP treatment: laser and anti-VEGF).
Type 2 Disease: Observe
- Zone I, stage 1 or 2 without plus disease
- Zone II, stage 3 without plus disease
Clinicians examine these eyes often, and treat them if they progress to type 1.
Early Treatment for Retinopathy of Prematurity: Plus Disease
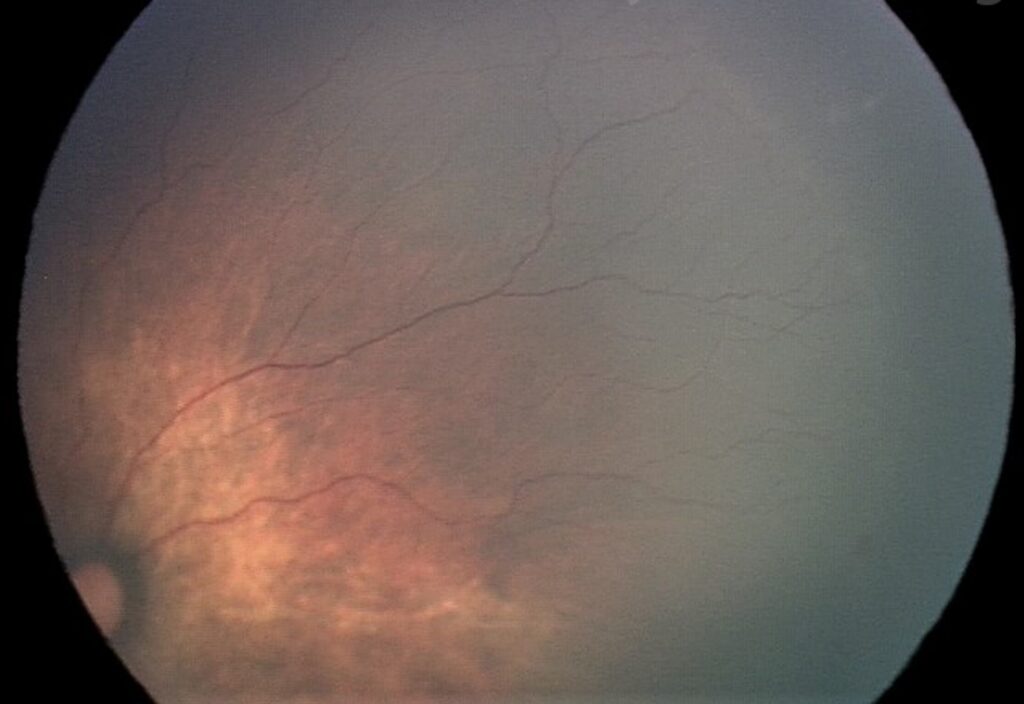
Plus disease means dilation and tortuosity of the posterior pole vessels at least as great as in a standard photograph.
Also, the recognition of plus disease varies between observers, and imaging and artificial intelligence tools are being tested to improve the consistency.
Impact on Practice
- Screening programs identify infants at risk, based on gestational age and birth weight
- Treatment moved earlier and laser became the standard until anti-VEGF drugs arrived
- The trial created a risk model that sped up decisions
Early Treatment for Retinopathy of Prematurity: Later Developments
Anti-VEGF therapy, such as bevacizumab, was tested in the BEAT-ROP and RAINBOW trials, and has become an option in some eyes, especially in zone I and posterior zone II disease.
Longer follow-up is also needed for effects on development and for late retinal changes.
Practical Use
Examine at-risk infants on schedule, document zone, stage, and plus disease, and then apply the type 1 and type 2 rules.
In addition, counsel parents about the need for long-term follow-up for refractive errors, strabismus, and amblyopia.
An Example Case
A premature infant born at 26 weeks and 760 grams is examined at 34 weeks of postmenstrual age and has stage 2 disease in zone II with plus disease in both eyes.
This is type 1 disease under the ETROP rules, so the team performs laser photocoagulation of the avascular retina within 48 hours (see rop treatment: laser and anti-VEGF).
At follow-up the vessels regress, and by term the retina is attached, with regular visits continuing for refractive error and amblyopia.
Practical Steps in the Nursery
- Screen all infants who meet birth weight or gestational age criteria
- Record zone, stage, extent, and plus disease at each exam
- Classify the eye as type 1, type 2, or below threshold, and set the next exam date
- Treat type 1 disease promptly, and review type 2 disease every week
Counselling the Parents
Explain that retinopathy of prematurity is common in very premature babies, that most cases regress by themselves, and that treatment is needed in a minority to prevent detachment.
Tell parents that eye care continues after discharge, since children have a higher risk of myopia, strabismus, and amblyopia.
Key Points to Remember
- Early treatment of type 1 disease reduces unfavorable outcomes
- Watch type 2 disease closely
- Plus disease and zone I involvement carry the highest risk
- Anti-VEGF therapy has become an option in selected eyes
Limits of the Study
The trial included infants with a high-risk prethreshold stage in both eyes, so it did not test treatment for lower-risk disease.
Surgeons did it when laser was the only choice.
Newer studies compare laser with anti-VEGF drugs.
Researchers are still studying the long-term safety of those drugs in premature infants.
For the latest studies, see the PubMed results for Early Treatment for Retinopathy of Prematurity.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Early Treatment for Retinopathy of Prematurity Cooperative Group. Revised indications for the treatment of retinopathy of prematurity: results of the early treatment for retinopathy of prematurity randomized trial. Arch Ophthalmol. 2003;121:1684-1694.
- Good WV; Early Treatment for Retinopathy of Prematurity Cooperative Group. Final results of the Early Treatment for Retinopathy of Prematurity (ETROP) randomized trial. Trans Am Ophthalmol Soc. 2004;102:233-248.
- Good WV, Hardy RJ, Dobson V, et al. Final visual acuity results in the Early Treatment for Retinopathy of Prematurity study. Arch Ophthalmol. 2010;128:663-671.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.