
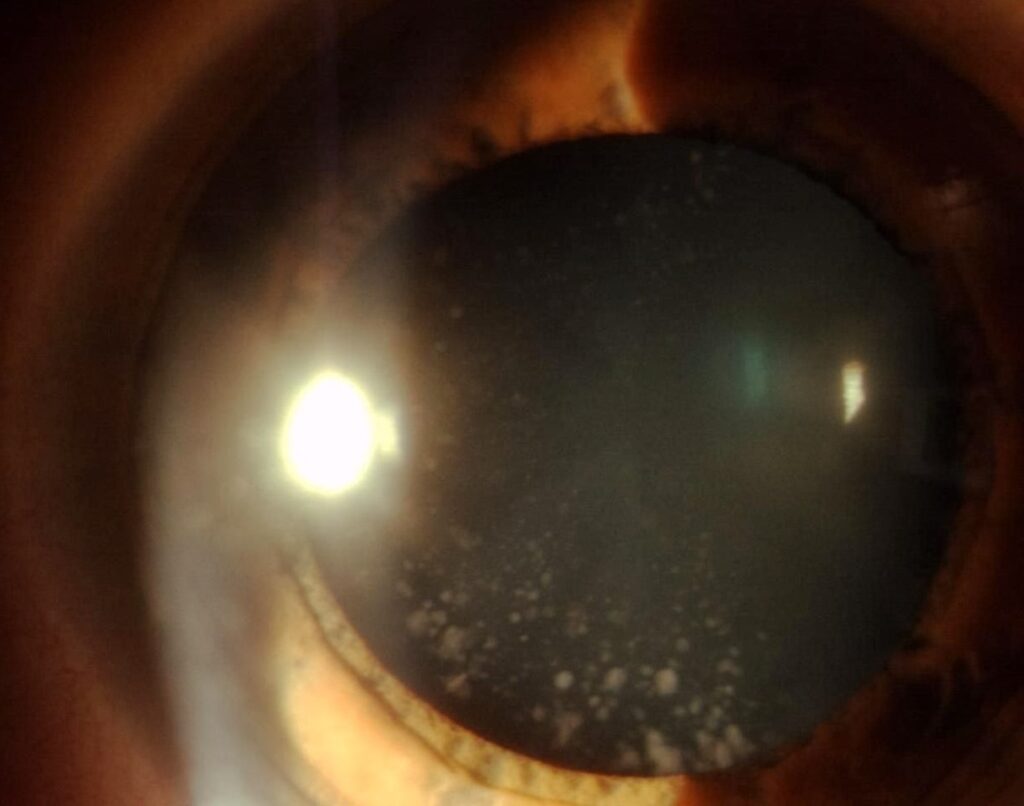
Coronary cataract is a developmental lens opacity in which a ring of club-shaped or rounded opacities surrounds the periphery of the lens, like a crown.
It usually begins around puberty, it is common, and it generally does not affect vision.
The finding is mostly a matter of recognition, so that it is not mistaken for a more serious opacity.
What Is Coronary Cataract?
The opacities lie in the deep cortex, at the level of the supranuclear zone, between the nucleus and the capsule.
They are arranged in a radial, crown-like fashion around the periphery of the lens, and they are usually bluish-white or sometimes translucent.
Coronary cataract is also called supranuclear cataract, because of its position.
The condition is often inherited as an autosomal dominant trait, and it is frequently found in several family members.
It develops during adolescence, increases slowly in number, and then stabilizes in adulthood.
Clinical Features
Most patients are asymptomatic, and the lens opacity is discovered at a routine examination, often in the teenage years or early adult life.
The central lens is clear, and the visual axis is spared, so acuity is normal.
With the pupil dilated, the slit lamp shows a ring of club- or wedge-shaped opacities with their rounded ends toward the center, and they are best seen in retroillumination.
The opacities are usually in both eyes, and they are symmetrical.
Other types of developmental cataract may coexist, such as blue-dot opacities (see cerulean cataract).
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDifferential Diagnosis
- Cortical cataract: wedge-shaped spokes in an older patient, progressing over years (see cortical cataract)
- Rosette cataract: a flower-like pattern of opacities, typically after trauma (see rosette-shaped cataract)
- Christmas tree cataract: polychromatic needle-like crystals in the deep cortex (see Christmas tree cataract)
- Snowflake cataract: flake-like opacities seen in diabetes (see snowflake cataract)
- Lamellar cataract: a shell of opacity surrounding a clear nucleus (see zonular lamellar cataract)
A coronary cataract does not involve the visual axis, so its position and shape help to separate it from these other types.
Evaluation
A dilated slit-lamp examination is enough to make the diagnosis.
Ask about family history, previous eye disease or injury, and any systemic condition that could cause lens changes.
If there is a known family history, examine relatives as appropriate.
Visual acuity and fundus examination are normal, and no further tests are required in an otherwise healthy patient.
Management
No treatment is needed, and the opacities usually remain stable for many years.
Patients can be reassured that the finding is a developmental variant and not a sign of systemic disease.
Because the opacities are peripheral, they seldom interfere with vision, even in later life.
If a visually significant cataract develops, it is usually from a different cause, and it should be assessed in the usual way.
A photograph at the first visit provides a baseline, and routine eye examinations at the usual intervals are sufficient.
The Spectrum of Developmental Lens Opacities
Many people have small, stable lens opacities that were present from the second decade, and they are usually classified by their position and shape.
Coronary and blue-dot opacities are among the commonest, and they are often found together in the same lens.
Other developmental opacities include sutural cataracts, which follow the Y-shaped sutures, and anterior polar and posterior polar cataracts (see posterior polar cataract).
Most of these are visually insignificant, but a few progress, so the examination should record the type and location carefully.
What to Tell the Patient
Reassure the patient that coronary opacities are a normal variant in many families and are not related to ageing or systemic disease.
If a young person has been told that they have cataract, explain that this is not the same as the visually significant cataract that occurs later in life.
Many patients appreciate a drawing or a photograph that shows where the opacities lie relative to the visual axis.
Surgical Relevance
In later life, a patient with a coronary cataract may need cataract surgery for an unrelated opacity.
The coronary opacities themselves do not complicate surgery, and the lens can be managed in the usual way.
If a surgeon sees a peripheral ring of opacities during preoperative assessment, a note in the chart avoids confusion.
Some patients find that the opacities increase slightly in number during their twenties and thirties, and this does not change the advice.
If vision declines in a person with a coronary cataract, look for another cause, such as refractive change, posterior subcapsular opacity, or a problem in the retina or optic nerve.
A comprehensive examination of the whole eye is the way to find it.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- Yanoff M, Duker JS, eds. Ophthalmology. 5th ed. Elsevier; 2019.
- Lambert SR, Lyons CJ, eds. Taylor and Hoyt’s Pediatric Ophthalmology and Strabismus. 5th ed. Elsevier; 2017.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 11: Lens and Cataract. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.


