
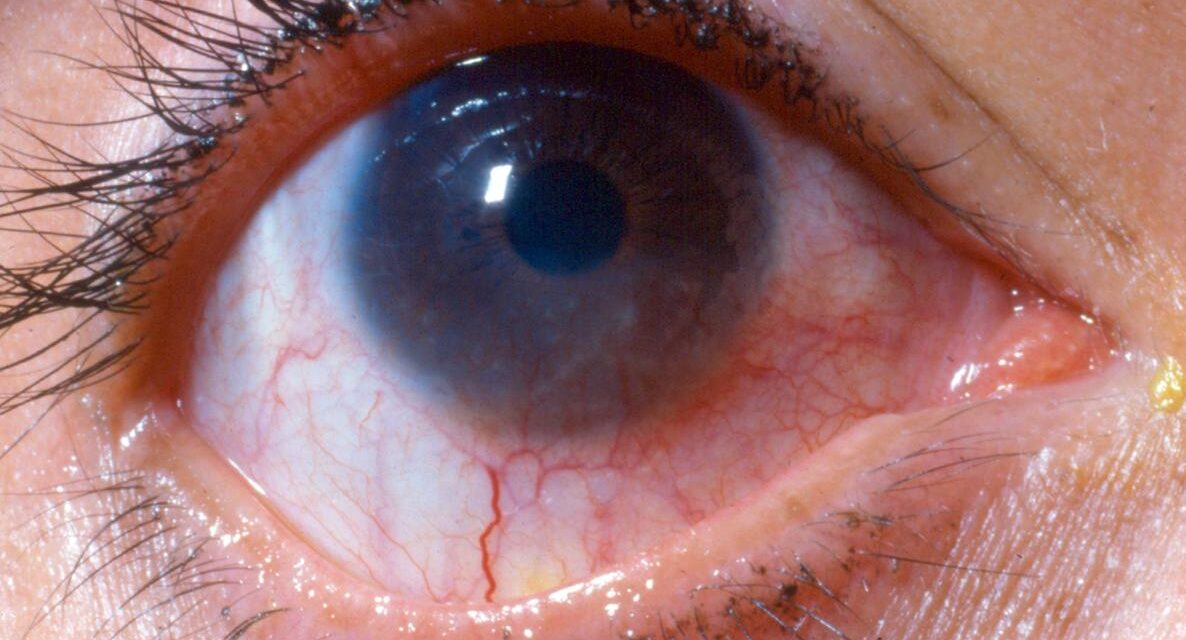
Phlyctenular keratoconjunctivitis is a delayed (type IV) hypersensitivity reaction of the conjunctiva and cornea, producing small, raised, pinkish-white nodules — phlyctenules — usually at the limbus.
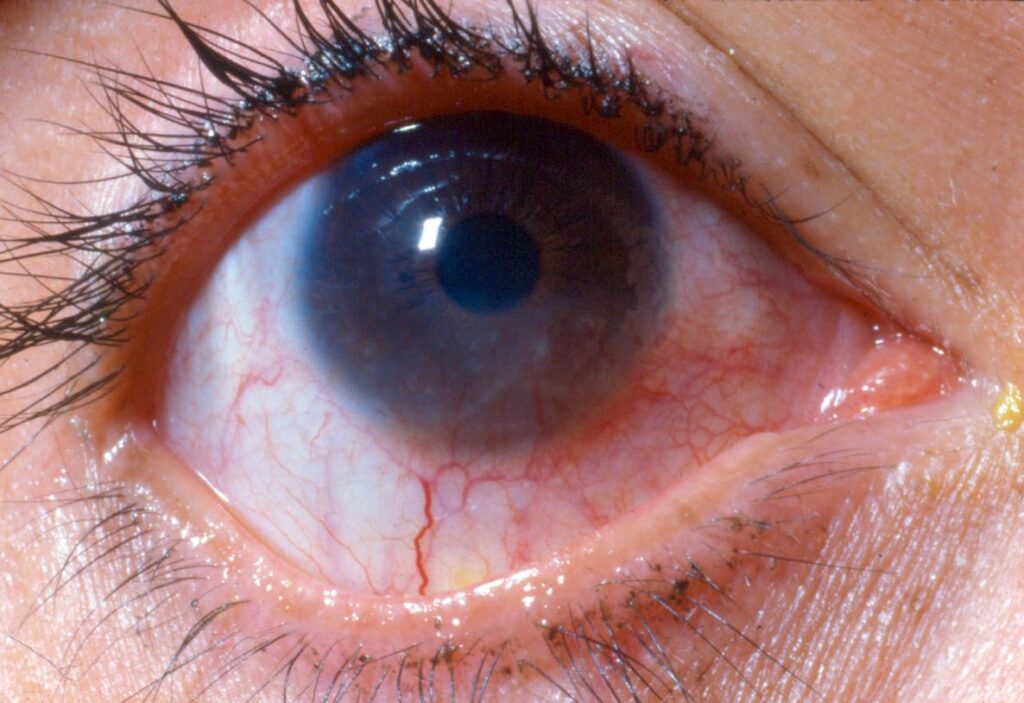
It is not an infection of the eye itself, but the eye’s immune response to a bacterial antigen that originated somewhere else in the body, most classically staphylococcal exotoxin from chronic blepharitis, or historically, tuberculoprotein.
The condition is seen across all ages but has a particular association with childhood blepharitis in the historical literature and, in regions where it is still common, with active or past tuberculosis, and recognizing it matters because treating the phlyctenule alone without addressing the underlying antigenic trigger — usually the eyelid disease — leads to recurrence.
Pathogenesis
The lesion represents a cell-mediated hypersensitivity reaction to a bacterial antigen, most often Staphylococcus aureus exotoxin from chronic anterior blepharitis, though Mycobacterium tuberculosis, Chlamydia trachomatis, and intestinal parasites have all been implicated as triggers in different populations.
The limbus is a preferred site because it sits at the junction of the conjunctival and corneal vasculature, giving circulating immune cells easy access to the tissue where the reaction plays out.
Unlike an infectious keratitis, cultures and stains of the phlyctenule itself are typically sterile, because the lesion is immunologic, not infectious, even though the trigger is usually a bacterial or mycobacterial antigen from elsewhere.
Clinical Presentation
Patients present with photophobia, tearing, and a foreign-body sensation that can be strikingly severe relative to the size of the lesion, when the phlyctenule sits on or near the cornea.
A limbal phlyctenule typically starts as a small, gray-white, raised nodule surrounded by localized conjunctival injection, and it often ulcerates centrally within a few days before resolving over one to two weeks.
When the lesion migrates onto the cornea — corneal phlyctenules tend to be more aggressive than limbal ones — it can leave a wedge-shaped scar with a trailing edge of superficial vascularization pointing back toward the limbus, a pattern that is characteristic on follow-up exams even after the acute lesion has healed.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteExam Findings
- Small, raised, pinkish-white nodule, usually 1–3 mm, at the limbus or on the cornea
- Localized conjunctival injection radiating toward the lesion
- Central ulceration of the phlyctenule as it evolves
- Associated chronic blepharitis with lid margin crusting, common as the underlying trigger
- Corneal vascularization and thinning at the site of prior lesions in recurrent disease
Differential Diagnosis
- Vernal keratoconjunctivitis — Horner-Trantas dots at the limbus, but with giant tarsal papillae and seasonal itching, distinguishing it from an isolated phlyctenule
- Marginal (staphylococcal hypersensitivity) keratitis — peripheral stromal infiltrate separated from the limbus by a clear zone, rather than a raised limbal nodule
- Episcleral nodule (nodular episcleritis) — deeper, without the epithelial breakdown seen in a phlyctenule
- Infectious keratitis — usually associated with a more acute, painful presentation and a positive culture
Evaluation
The diagnosis is largely clinical, based on the characteristic appearance and the presence of an underlying trigger such as blepharitis.
Where tuberculosis is a realistic concern based on geography or risk factors, a tuberculin skin test or interferon-gamma release assay and chest imaging are reasonable, because ocular phlyctenulosis can occasionally be the presenting sign of otherwise undiagnosed TB, and identifying it in this context carries obvious public health as well as individual patient significance.
Lid margin cultures are not routinely necessary but can be considered in recurrent or severe cases to confirm staphylococcal colonization and guide lid hygiene and antibiotic choice, particularly when initial treatment of presumed blepharitis has not produced the expected improvement.
Management
Topical corticosteroids are the mainstay of acute treatment and typically produce rapid symptomatic relief and resolution of the lesion within days; a short, tapering course is usually sufficient for an isolated episode.
Treating the underlying trigger is what prevents recurrence: aggressive lid hygiene and a topical or oral antibiotic course for staphylococcal blepharitis, or referral for systemic antituberculous therapy if active TB is identified.
Topical antibiotics are sometimes added alongside the steroid, both to treat coexisting blepharitis and as a precaution given that corticosteroids can mask a low-grade infectious component if the diagnosis is not entirely certain.
Follow-up after the acute episode has resolved should specifically confirm that the underlying blepharitis (or other identified trigger) is being adequately managed, rather than simply confirming that the phlyctenule itself has healed, since the healed lesion tells you nothing about whether the antigenic source has actually been controlled.
Recurrent or severe corneal disease with scarring may eventually need addressing on its own terms, whether astigmatism correction or, rarely, keratoplasty for dense central scars, particularly in patients whose antigenic trigger proved difficult to fully control despite repeated attempts.
Prognosis
Limbal phlyctenules generally resolve without leaving a visually significant scar, but corneal phlyctenules carry more risk, because repeated episodes at the same or nearby sites can accumulate stromal scarring and vascularization that reduce vision.
This is the main argument for controlling the underlying trigger rather than treating each flare in isolation, since durable, lasting control of the antigenic source is what genuinely protects long-term vision rather than repeated courses of topical steroid for each new episode.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Ostler HB. Phlyctenular keratoconjunctivitis. International Ophthalmology Clinics.
- Doan S, Gabison E, Gatinel D, et al. Topical cyclosporine A in severe steroid-dependent childhood phlyctenular keratoconjunctivitis. American Journal of Ophthalmology.
- Culbertson WW, Huang AJ, Mandelbaum SH, et al. Effective treatment of phlyctenular keratoconjunctivitis with oral tetracycline. Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea.
