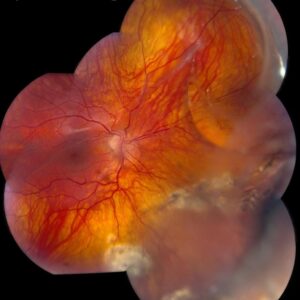
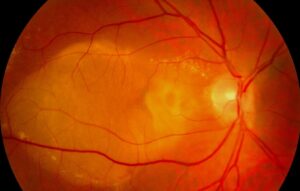
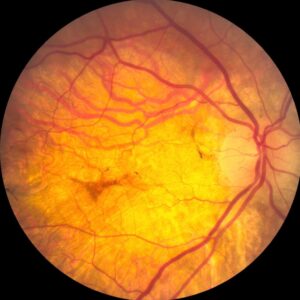
Circinate exudates are hard lipid deposits arranged in a complete or partial ring around a leaking retinal focus.
Therefore, the center of the ring usually marks the source of leakage.
As a result, the examiner should read the ring as a map and then look inward.
What Circinate Exudates Look Like
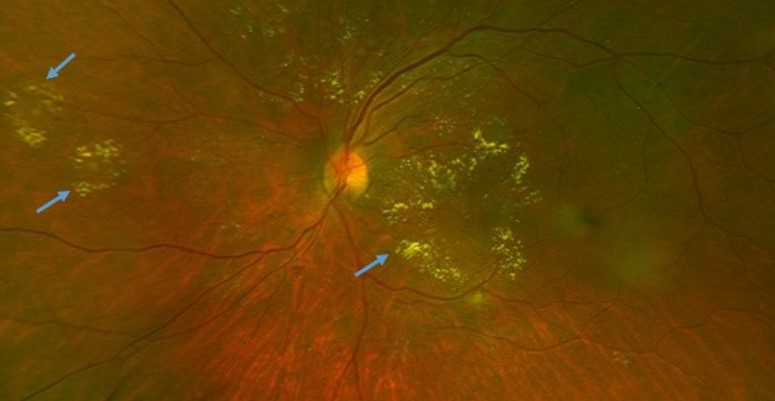
On fundus examination, sharply defined yellow deposits form a circle or an incomplete arc.
However, the retina inside the ring often looks thickened, and microaneurysms may appear there.
Also, size varies from a small cluster to a broad ring across the posterior pole.
These deposits consist of lipoproteins that escaped because vessel walls are abnormal (see hard exudates).
Why Circinate Exudates Form a Ring
First, plasma leaks from a central focus and spreads through the surrounding retina.
Next, the retinal pigment epithelium and vessels remove water and small solutes quickly.
However, large lipoproteins clear more slowly, so they concentrate at the edge of the edematous zone.
As a result, lipid precipitates near the junction of thickened and healthier retina.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteCommon Causes of Circinate Exudates
Because chronic leakage drives the ring, the causes below are common.
- Diabetic macular edema with leaking microaneurysms
- Also, retinal arterial macroaneurysm
- Chronic branch retinal vein occlusion
- In addition, Coats disease and other telangiectasias
- Radiation retinopathy
- Finally, neovascular age-related macular degeneration, including polypoidal lesions
Diabetic Macular Edema
First, diabetes is the classic setting, and a microaneurysm cluster often sits at the ring center.
Hard exudates near the fovea matter because adjacent thickening can meet the ETDRS definition of clinically significant macular edema.
Spotting a Macroaneurysm
For example, an older hypertensive patient with a unilateral ring needs careful inspection of the arterioles.
However, hemorrhage at several retinal levels can hide the saccular dilation.
Tracing the Source of Circinate Exudates
- First, identify the geometric center of the ring or the implied center of an arc.
- Next, examine that area at high magnification for microaneurysms or telangiectasia.
- Then correlate with OCT to define thickening, fluid and lesion depth.
- Finally, use angiography when the source remains uncertain.
Imaging in Circinate Exudates
On OCT, hard exudates appear as hyperreflective deposits that often shadow deeper layers.
Also, intraretinal cysts or subretinal fluid inside the ring support active leakage.
In addition, pigment epithelial detachment shifts suspicion toward a choroidal source.
Then fluorescein angiography shows leaking microaneurysms as early hyperfluorescent points with late leakage.
Finally, indocyanine green angiography helps when polypoidal lesions remain possible.
Circinate Exudates Versus Macular Star
First, a macular star follows the radial Henle fiber layer around the fovea.
It therefore points toward disc leakage, severe hypertension or neuroretinitis (see macular star).
By contrast, a circinate ring surrounds a focal leak anywhere in the posterior pole.
Symptoms and Prognosis
Because symptoms depend on location, an extramacular ring may cause none.
However, foveal involvement can cause blur or metamorphopsia.
Also, heavy subfoveal lipid may leave permanent damage despite later drying.
Treating the Source
Treatment targets the leak, because the ring only signals the underlying process.
First, anti-VEGF therapy is first-line for center-involving diabetic macular edema with vision loss, and Protocol T compared three agents.
Also, analyzes of RIDE and RISE linked ranibizumab with reduced hard exudate.
However, injections do not guarantee lipid clearance, and they carry a small risk of endophthalmitis.
In addition, focal laser reduced moderate visual loss in ETDRS eyes with clinically significant macular edema.
However, laser can cause scotoma and expanding atrophic scars near fixation.
Also, other causes need specific plans, including ablative treatment for Coats disease.
Serum Lipids and Systemic Care
First, ETDRS data associated elevated serum lipids with greater hard exudate and higher risk of vision loss.
However, this association does not prove that lipid lowering clears an established ring.
Therefore, coordinated care for lipids, glucose and blood pressure is still reasonable.
Follow-Up of Circinate Exudates
Absorption often takes months because lipid clears slowly after the leak closes.
Consequently, OCT thickness and fluid track activity better than visible lipid.
For example, lipid may look more prominent while edema resolves.
Finally, at each visit, check for encroachment toward the fovea, new leaks and fibrosis.
Counseling the Patient
First, explain that the yellow ring marks leakage and fades slowly.
Patients should also understand that treatment protects central vision, but existing damage may not recover.
Finally, ask them to report new distortion or sudden blur promptly.
Pitfalls to Avoid
- Do not treat the lipid ring while ignoring the central source
- Also avoid judging response from lipid appearance alone
- However, do not call every yellow macular deposit drusen
- Never overlook a macroaneurysm because hemorrhage can hide it


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Early Treatment Diabetic Retinopathy Study Research Group. Photocoagulation for diabetic macular edema: ETDRS report number 1. Arch Ophthalmol. 1985;103:1796-1806.
- Chew EY, Klein ML, Ferris FL, et al. Association of elevated serum lipid levels with retinal hard exudate in diabetic retinopathy: ETDRS report 22. Arch Ophthalmol. 1996;114:1079-1084.
- Diabetic Retinopathy Clinical Research Network, Wells JA, Glassman AR, et al. Aflibercept, bevacizumab, or ranibizumab for diabetic macular edema. N Engl J Med. 2015;372:1193-1203.
- Domalpally A, Ip MS, Ehrlich JS. Effects of intravitreal ranibizumab on retinal hard exudate in diabetic macular edema. Ophthalmology. 2015;122:779-786.
- Rabb MF, Gagliano DA, Teske MP. Retinal arterial macroaneurysms. Surv Ophthalmol. 1988;33:73-96.
- Shields JA, Shields CL, Honavar SG, Demirci H. Clinical variations and complications of Coats disease in 150 cases. Am J Ophthalmol. 2001;131:561-571.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.