Months or years after a successful cataract operation, some patients report that their vision has become hazy again.
The cause is rarely a new cataract, because the natural lens has been removed.
It is posterior capsule opacification (PCO), and Elschnig pearls are one of its two main forms.
What Elschnig pearls are
After surgery, the capsular bag still contains residual lens epithelial cells.
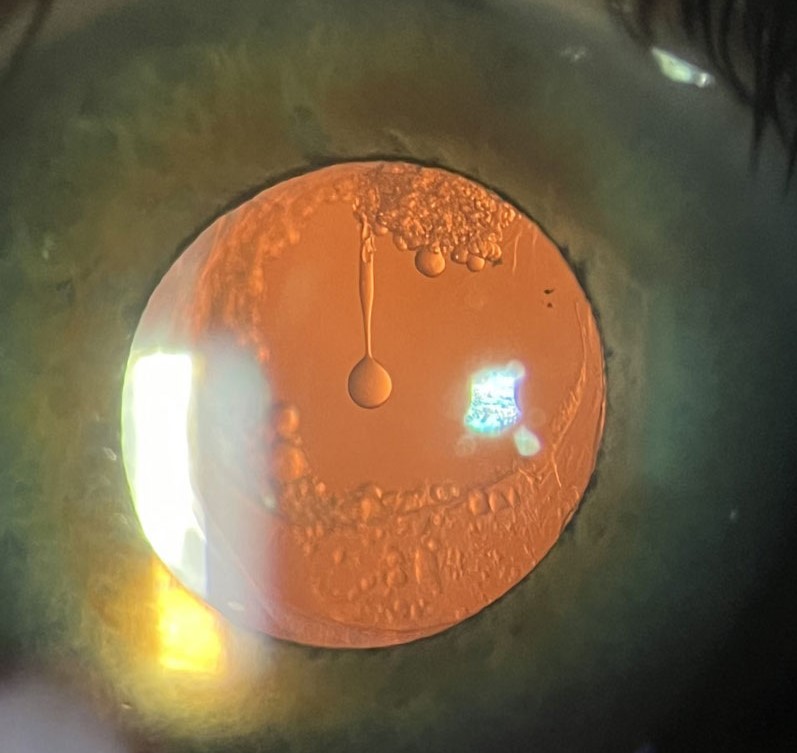
Some migrate from the equator onto the posterior capsule, and some proliferate and swell into clear, round, bladder-like cells, called Wedl or bladder cells.
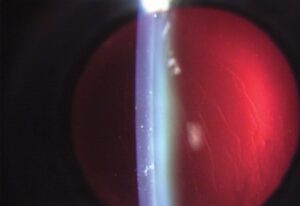
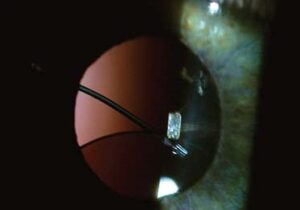
Clusters of these cells look like small translucent pearls sitting on the posterior capsule.
They were described by the Austrian ophthalmologist Anton Elschnig in the early twentieth century, which is why his name remains attached to them.
The other form of PCO is fibrosis, in which epithelial cells transform into myofibroblast-like cells that lay down collagen and wrinkle the capsule.
How the patient notices it
- Gradual decline of vision, weeks to years after surgery
- Glare, halos, and reduced contrast, particularly in bright light
- Difficulty reading, though the visual acuity may still be fairly good in the early stages
- Monocular diplopia or ghosting in some patients
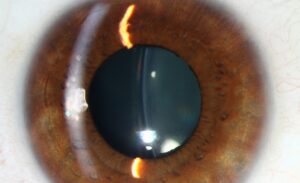
On retroillumination at the slit lamp, the pearls appear as small, round, glistening bodies, and fibrosis appears as wrinkles or striae in the capsule.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteHow common it is
Older studies reported PCO in one fifth to one half of eyes within five years of surgery.
Modern lens designs and techniques have reduced these rates considerably.
Children develop PCO faster and more often than adults, since their lens epithelial cells are more proliferative.
Risk factors
- Younger age
- Retained cortex or an incomplete cortical clean-up
- Small anterior capsulorhexis that does not overlap the IOL edge
- Intraocular lens materials and designs with a round edge
- Uveitis, diabetes, and myotonic dystrophy
- Pseudoexfoliation, which affects the capsule and zonules (see pseudoexfoliation syndrome)
Prevention
A sharp, square-edged optic acts as a barrier against cell migration, and this feature is the single most effective design change.
Hydrophobic acrylic IOLs adhere to the capsule well and reduce PCO compared with some older materials.
At the time of surgery, careful hydrodissection, removal of cortex, polishing of the posterior capsule, and a capsulorhexis that overlaps the optic all help.
Treatment
Nd:YAG laser capsulotomy opens the central posterior capsule in a few minutes as an outpatient procedure (see YAG laser capsulotomy).
Vision usually improves within hours.
Complications, though uncommon, include a transient rise in intraocular pressure, IOL pitting, cystoid macular edema, and retinal detachment, particularly in highly myopic eyes.
Patients should be warned about new floaters and flashes after the procedure, and told to return if there is a shadow in their vision.
Timing
It is usually best to wait until the opacity is clearly causing symptoms and the capsule has matured, and to avoid capsulotomy within the first few months after surgery unless there is a strong reason.
In children, early capsulotomy or primary posterior capsulorhexis may be considered to keep the visual axis clear and prevent amblyopia.
How the clinic visit goes
A patient with symptoms of late visual decline after cataract surgery should have the visual acuity measured in dim and bright light, because glare is often the first complaint. Dilate and examine the posterior capsule with retroillumination, looking for pearls, fibrosis, wrinkles, and the position of the lens. Rule out other causes of late blur, including cystoid macular edema, epiretinal membrane, and corneal edema, because treating the capsule will not help these.
What to tell patients before laser
Explain that the laser is quick and painless, that the vision often improves within a day, that a few floaters may be seen afterwards, and that the capsule does not grow back in the same way once it has been opened. Warn them that flashes, a shadow, or a sudden increase in floaters need urgent examination, and arrange a pressure check shortly after the procedure in patients at risk of a rise.
Differential diagnosis of late blur
- Cystoid macular edema, which shows retinal thickening on OCT and may coexist with PCO
- Epiretinal membrane, with distortion that persists after capsulotomy
- Corneal edema or dry eye, with fluctuating vision and surface staining
- Lens decentration or tilt, with glare and optical aberrations
- Refractive error from a biometry surprise
Treat capsule opacification only after these have been considered, since laser will not correct them.
Prognosis
Treated correctly, PCO has an excellent prognosis, and most patients return to their post-operative visual level.
Some will need a second look if the opening closes, which is rare.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Apple DJ, Solomon KD, Tetz MR, et al. Posterior capsule opacification. Surv Ophthalmol. 1992;37:73-116.
- Wormstone IM, Wang L, Liu CS. Posterior capsule opacification. Exp Eye Res. 2009;88:257-269.
- Findl O, Buehl W, Bauer P, Sycha T. Interventions for preventing posterior capsule opacification. Cochrane Database Syst Rev. 2010;(2):CD003738.
- Nibourg LM, Gelens E, Kuijer R, Hooymans JM, van Kooten TG, Koopmans SA. Prevention of posterior capsular opacification. Exp Eye Res. 2015;136:100-115.
Test yourself
A few questions straight from this article.
-
Elschnig pearls on the posterior capsule are clusters of which cell type?
Residual lens epithelial cells migrate onto the posterior capsule and swell into clear, round, bladder-like Wedl cells, whose clusters look like small translucent pearls. -
Posterior capsule opacification after cataract surgery takes which two main forms?
Elschnig pearls are one of the two main forms of posterior capsule opacification; the other is fibrosis, in which the cells transform and lay down collagen. -
What produces the fibrotic form of posterior capsule opacification?
In the fibrotic form, lens epithelial cells transform into myofibroblast-like cells that lay down collagen and wrinkle the capsule. -
Older studies reported posterior capsule opacification in what share of eyes within five years of cataract surgery?
Older series reported posterior capsule opacification in one fifth to one half of eyes within five years, though modern lens designs and techniques have reduced these rates considerably. -
Which slit-lamp technique best demonstrates Elschnig pearls on the posterior capsule?
On retroillumination the pearls appear as small, round, glistening bodies, while fibrosis shows as wrinkles or striae in the capsule. -
Which systemic condition is listed as a risk factor for posterior capsule opacification?
Uveitis, diabetes and myotonic dystrophy all increase the risk of posterior capsule opacification, as does pseudoexfoliation, which affects the capsule and zonules. -
Which intraocular lens material adheres well to the capsule and lowers posterior capsule opacification rates?
Hydrophobic acrylic intraocular lenses adhere to the capsule well and reduce posterior capsule opacification compared with some older materials. -
How quickly does vision usually improve after Nd:YAG capsulotomy for posterior capsule opacification?
Nd:YAG capsulotomy opens the central posterior capsule in a few minutes as an outpatient procedure, and vision usually improves within hours. -
Which complication of Nd:YAG capsulotomy is of particular concern in a highly myopic eye?
Uncommon complications include a transient pressure rise, lens pitting, cystoid macular oedema and retinal detachment, the last being a particular concern in highly myopic eyes. -
Which cause of late blur after cataract surgery produces distortion that persists even after capsulotomy?
An epiretinal membrane causes distortion that remains after capsulotomy, so it must be considered before the capsule is lasered.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.