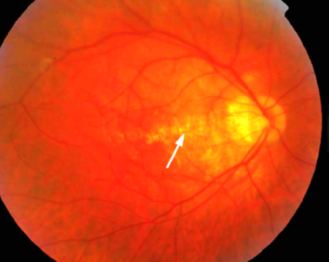
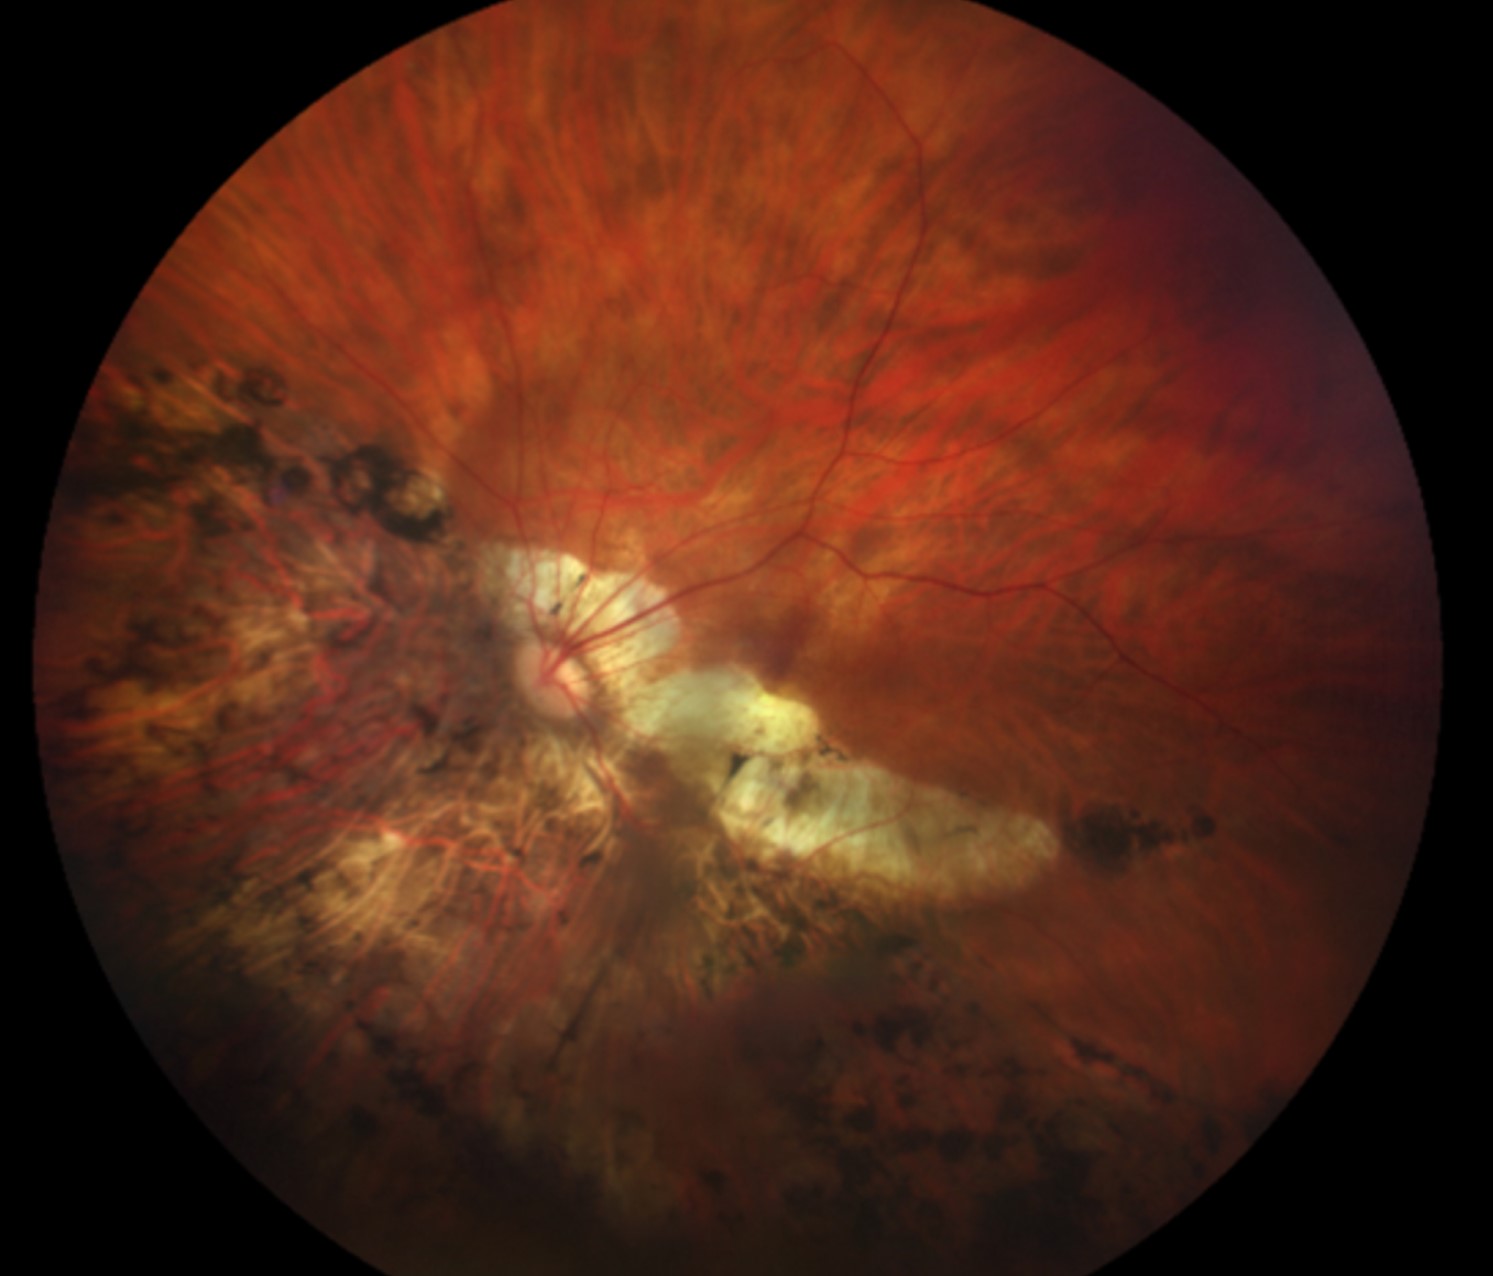
Lacquer cracks are fine, irregular, yellowish lines in the posterior pole of highly myopic eyes.
They represent mechanical breaks in the retinal pigment epithelium, Bruch membrane, and choriocapillaris complex.
They are also a marker of advanced myopic maculopathy.
Lacquer cracks predict a higher risk of macular hemorrhage and choroidal neovascularization.
Also, recognizing them gives the clinician a reason to look more carefully at the macula and to advise the patient on warning symptoms.
What Are Lacquer Cracks?
In pathologic myopia, axial elongation stretches the posterior pole, and the posterior staphyloma places mechanical stress on Bruch membrane.
Bruch membrane is thin and brittle, and it can also fracture under the strain, producing linear defects.
These breaks look like cracks in lacquer, hence the name.
They are usually seen in the posterior pole, often radiating from the fovea or crossing it.
Lacquer cracks may also arise spontaneously or follow minor trauma or a Valsalva effort.
They are also part of the myopic maculopathy classification, grouped with choroidal neovascularization and Fuchs spot as plus lesions (see META-PM classification).
Clinical Appearance
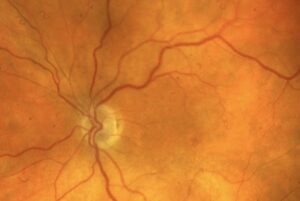
- Irregular, branching, yellowish-white lines, often a few disc diameters long
- Located in the posterior pole, sometimes in the macular area
- Often accompanied by tessellation, posterior staphyloma, and chorioretinal atrophy (see staphyloma)
- May be associated with subretinal hemorrhage, which can also occur without neovascularization
- Mostly bilateral in eyes with an axial length above about 26 to 28 millimeters
They can be difficult to see in an eye with extensive atrophy, and imaging gives a more reliable detection.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteImaging in Lacquer Cracks
Fundus autofluorescence shows lacquer cracks as linear hypoautofluorescent lines (see fundus autofluorescence).
Fluorescein angiography shows window defects along the lines, while indocyanine green angiography shows linear hypofluorescence in the early and late phases.
In addition, OCT shows a break in the RPE-Bruch membrane line, sometimes with a small hyperreflective focus above it, and subtle disruption of the outer retina.
OCT angiography can also help to detect an associated neovascular membrane without dye (see OCT angiography).
Complications of Lacquer Cracks
- Myopic choroidal neovascularization, a leading cause of vision loss in young adults with pathologic myopia (see myopic choroidal neovascularization)
- Simple hemorrhage at the site of the crack, which usually resolves with good vision
- Patchy atrophy, which often develops along the line
- Progressive widening of cracks with age
A patient who reports sudden distortion or a central blind spot needs same-week examination and OCT.
Differential Diagnosis of Lacquer Cracks
- Angioid streaks: broader, reddish-brown lines radiating from the disc, in a different systemic setting (see angioid streaks)
- Choroidal folds: parallel linear folds that change with the angle of the light (see choroidal folds)
- Chorioretinal scars and atrophy from other causes
Management
No treatment is needed for the cracks themselves.
In addition, teach the patient to use an Amsler grid for self-monitoring, and to report any new distortion.
Also, treat neovascular membranes with anti-VEGF injections, which give good results in myopic eyes with a small number of injections (see anti-VEGF therapy).
Advise protective eyewear and avoidance of activities with a high risk of ocular trauma.
In addition, review patients regularly for macular and peripheral retinal complications (see retinal detachment in high myopia).
Epidemiology and Natural History
Lacquer cracks are found in a minority of highly myopic eyes.
The frequency rises with axial length and with age.
They often appear in the third and fourth decades, and the cracks may increase in number and width over the years.
In longitudinal studies, eyes with lacquer cracks have a higher chance of developing myopic choroidal neovascularization and patchy atrophy than eyes without them.
The cracks are therefore more than a cosmetic finding in the fundus, and they signal a need for closer follow-up.
Hemorrhage Without Neovascularization
A patient with sudden blurring and a small macular hemorrhage at a lacquer crack may have a simple hemorrhage and no neovascular membrane.
Also, OCT angiography and fluorescein angiography help to exclude a membrane.
Most simple hemorrhages resolve within weeks with good visual recovery.
Because it can be hard to be sure, follow-up in a week or two is wise, with repeat OCT, and injections are given only if neovascularization is confirmed.
Advice for Patients
Patients with high myopia and lacquer cracks should be told to avoid heavy straining, and to protect their eyes during sports.
Provide an Amsler grid and ask them to check each eye once a week.
Encourage regular examinations of the macula and the peripheral retina, since detachment and other complications are also frequent in these eyes.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Klein RM, Green S. The development of lacquer cracks in pathologic myopia. Am J Ophthalmol. 1988;106:282-285.
- Ohno-Matsui K, Kawasaki R, Jonas JB, et al. International photographic classification and grading system for myopic maculopathy. Am J Ophthalmol. 2015;159:877-883.
- Ohno-Matsui K, Lai TY, Lai CC, Cheung CM. Updates of pathologic myopia. Prog Retin Eye Res. 2016;52:156-187.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
Lacquer cracks in pathologic myopia represent mechanical breaks in which tissue complex?
Lacquer cracks are fine yellowish lines that represent mechanical breaks in the RPE, Bruch membrane and choriocapillaris complex. -
What causes Bruch membrane to fracture and form lacquer cracks in pathologic myopia?
Axial elongation and the posterior staphyloma stress the thin, brittle Bruch membrane until it fractures into linear defects. -
In the myopic maculopathy classification, lacquer cracks are grouped as plus lesions with which findings?
Lacquer cracks are plus lesions in the myopic maculopathy classification, grouped with choroidal neovascularization and Fuchs spot. -
How do lacquer cracks appear on fundus autofluorescence?
Fundus autofluorescence shows lacquer cracks as linear hypoautofluorescent lines, giving more reliable detection than the fundus view in atrophic eyes. -
What does indocyanine green angiography show along lacquer cracks?
ICG angiography shows linear hypofluorescence in both early and late phases, while fluorescein shows window defects along the lines. -
Which complication of lacquer cracks is a leading cause of vision loss in young adults with pathologic myopia?
Myopic CNV, a leading cause of vision loss in young adults with pathologic myopia, is treated with anti-VEGF injections, often needing only a few. -
A highly myopic patient has a small macular hemorrhage at a lacquer crack, and imaging shows no neovascular membrane. What is appropriate?
Simple hemorrhages usually resolve within weeks; follow-up in a week or two with OCT is wise, and injections are given only if CNV is confirmed. -
How do angioid streaks differ from lacquer cracks on fundus examination?
Angioid streaks are broader, reddish-brown lines radiating from the disc in a different systemic setting; choroidal folds are parallel and change with light angle. -
What is the management of lacquer cracks themselves in pathologic myopia?
The cracks need no treatment; patients use an Amsler grid to check each eye weekly and report new distortion. -
How do lacquer cracks typically change over time in pathologic myopia?
Lacquer cracks often appear in the third and fourth decades and may increase in number and width over the years, with frequency rising with axial length and age.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.