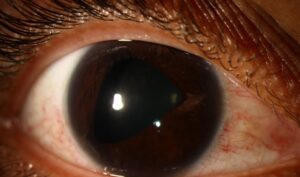
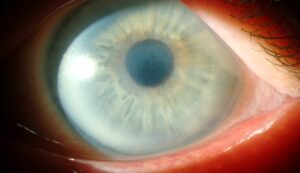
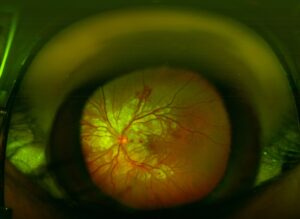
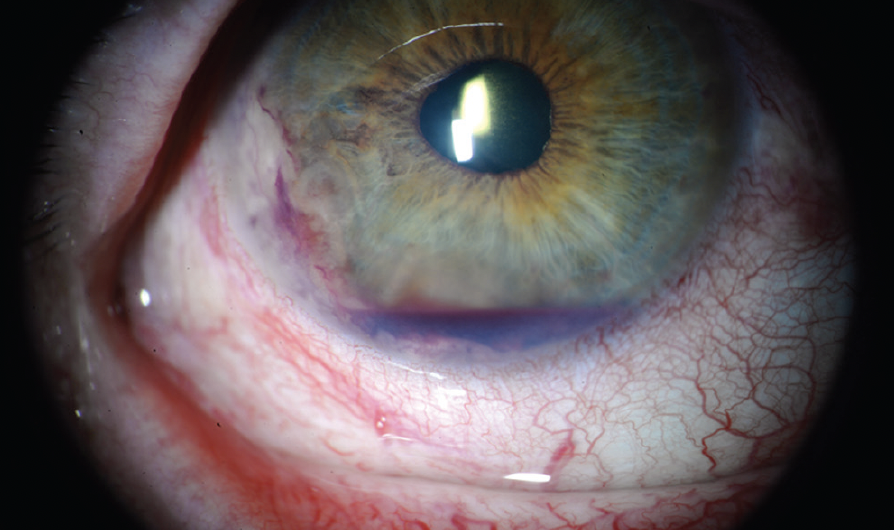
Sickle cell hyphema is blood in the anterior chamber of a patient with sickle cell disease or trait.
Even a small bleed can raise intraocular pressure (IOP) quickly.
In addition, the optic nerve tolerates that pressure poorly.
Therefore, the safe IOP threshold is lower, and several routine glaucoma drugs become hazardous.
Why Red Cells Sickle in the Anterior Chamber
Aqueous humor has low oxygen tension and becomes more acidic after trauma.
These conditions favor polymerization of hemoglobin S.
As a result, red cells become rigid and sickled within the chamber.
Goldberg demonstrated sickled erythrocytes in hyphemas from patients with trait and disease.
How Sickle Cell Hyphema Raises IOP
Normal red cells are flexible and pass through the trabecular meshwork.
However, sickled cells cannot deform enough to exit.
They plug the outflow pathway, so pressure climbs even with a modest clot.
Therefore, hyphema size predicts IOP poorly in these patients.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteWhy the Optic Nerve Is More Vulnerable
Sickled cells also impair flow in the optic nerve head and retinal microcirculation.
Raised IOP then lowers perfusion pressure further.
As a result, optic atrophy and central retinal artery occlusion can follow moderate pressures.
These injuries may develop within days.
Sickle Cell Trait Carries the Same Eye Risk
Sickle cell trait (HbAS) usually causes no systemic symptoms.
However, trait patients show the same anterior chamber sickling and outflow obstruction.
Deutsch and colleagues derived their surgical criteria in trait patients.
Treat trait and disease (HbSS, HbSC) with equal caution in the eye.
Screening for Sickle Cell Hyphema
Ask about sickle status at the first visit.
If status is unknown, order a sickle solubility test and hemoglobin electrophoresis.
Screening matters most in patients of African, Mediterranean, Middle Eastern or Indian ancestry.
Because many carriers are unaware of their trait, a negative history is unreliable.
Examination in Sickle Cell Hyphema
Record hyphema height in millimeters with the patient upright.
Next, measure IOP at every visit, and repeat it within hours if raised (see IOP measurement pitfalls).
Also, check pupils, cornea and retinal perfusion, after excluding an open globe.
Safe IOP Threshold in Sickle Cell Hyphema
Non-sickle eyes often tolerate higher pressures for several days.
Deutsch and colleagues advised surgery when mean IOP stays at or above 25 mmHg over 24 hours.
They also advised intervention for repeated spikes above 30 mmHg despite medical therapy.
Many clinicians therefore aim to keep IOP below about 24 mmHg.
First-Line Medical Therapy
Topical beta blockers are usually the first choice for pressure control.
Topical corticosteroids reduce inflammation, and cycloplegia improves comfort.
In addition, elevate the head, shield the eye and limit activity during the rebleeding window.
Drugs to Avoid in Sickle Cell Hyphema
- Oral acetazolamide, because systemic acidosis promotes sickling
- Mannitol and glycerol, because hemoconcentration raises blood viscosity
- Vasoconstrictive alpha agonists, because they may worsen anterior segment hypoxia
- Aspirin and NSAIDs, because they increase rebleeding risk
If a carbonic anhydrase inhibitor is unavoidable, many authors accept topical dorzolamide or methazolamide with caution.
Antifibrinolytic Agents
Aminocaproic acid and tranexamic acid aim to reduce rebleeding.
However, a Cochrane review found no clear benefit for final visual acuity.
Therefore, use them selectively and discuss sickle patients with hematology.
Anterior Chamber Paracentesis
Paracentesis lowers IOP quickly and removes some sickled cells.
Perform it at the slit lamp through a clear corneal tract with a fine needle.
However, the effect is often temporary.
Use it as a bridge while you arrange washout.
When to Wash Out Sickle Cell Hyphema Early
Plan washout when IOP meets the sickle threshold despite safe medical therapy.
Also, operate early for corneal blood staining, total hyphema or signs of optic nerve compromise.
During surgery, irrigate gently and avoid pulling adherent clot from the iris or lens.
Coordinate anesthesia with hematology, because hypoxia and acidosis can trigger a crisis.
Follow-Up After Sickle Cell Hyphema
Review the patient daily during the first several days.
Then, check IOP after washout, since rebleeding or ghost cells can raise it again (see ghost cell glaucoma).
Later, perform gonioscopy for angle recession and dilated fundus examination (see sickle cell retinopathy).
Counseling the Patient
Explain that sickle trait changes eye care even when the patient feels well.
Ask the patient to report pain, nausea or sudden blurring at once.
Also, explain that early surgery aims to protect the optic nerve.
Pitfalls to Avoid
- Do not judge risk by hyphema size alone
- Never give oral acetazolamide by reflex
- Do not assume a negative history excludes trait
- Avoid mannitol for pressure spikes
- Do not wait for disc pallor before operating
For the latest studies, see the PubMed results for sickle cell hyphema.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Goldberg MF. The diagnosis and treatment of sickled erythrocytes in human hyphemas. Trans Am Ophthalmol Soc. 1978;76:481-501.
- Goldberg MF. The diagnosis and treatment of secondary glaucoma after hyphema in sickle cell patients. Am J Ophthalmol. 1979;87:43-49.
- Deutsch TA, Weinreb RN, Goldberg MF. Indications for surgical management of hyphema in patients with sickle cell trait. Arch Ophthalmol. 1984;102:566-569.
- Walton W, Von Hagen S, Grigorian R, Zarbin M. Management of traumatic hyphema. Surv Ophthalmol. 2002;47:297-334.
- Gharaibeh A, Savage HI, Scherer RW, Goldberg MF, Lindsley K. Medical interventions for traumatic hyphema. Cochrane Database Syst Rev. 2019;1:CD005431.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.