Astigmatism is a very common refractive error.
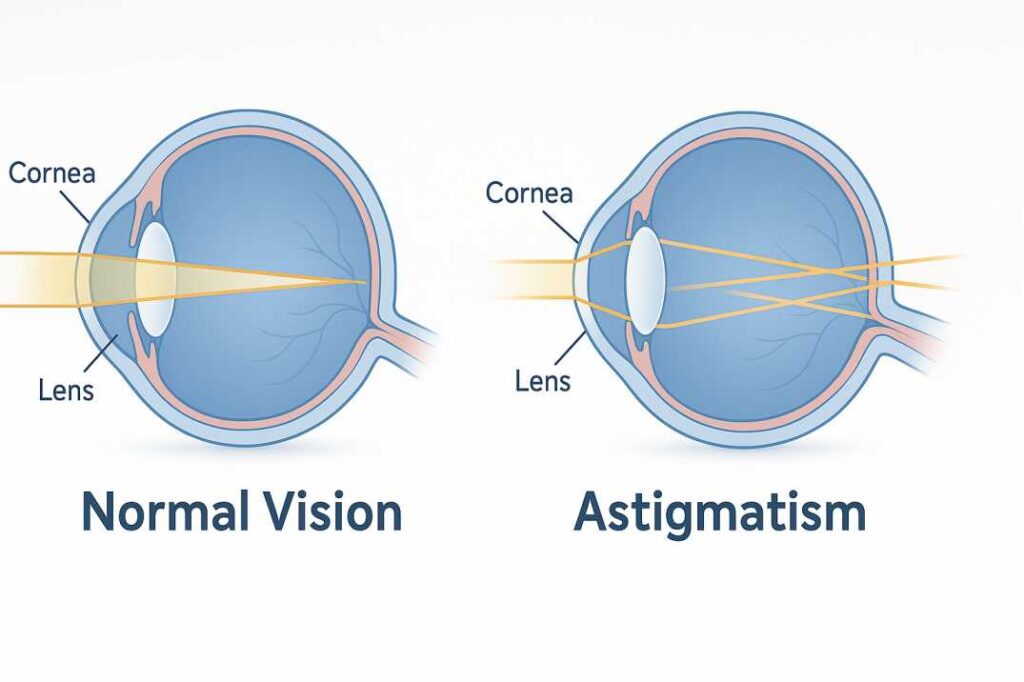
It occurs when the eye focuses light differently in different directions.
Most people can be corrected with glasses or contact lenses.
What Causes Astigmatism
The cornea is shaped more like a football than a basketball.
The lens can also be tilted or irregular.
Genetics play a major part.
Therefore, astigmatism often runs in families.
Regular vs Irregular Astigmatism
Regular astigmatism has two principal meridians at right angles.
Glasses can correct it fully.
Irregular astigmatism comes from scars or ectasia (see keratoconus progression).
So rigid lenses may be needed.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteWith-the-Rule and Against-the-Rule
With-the-rule astigmatism has a steeper vertical meridian.
It is common in young people.
Against-the-rule astigmatism is steeper horizontally and more common in older adults.
Also oblique types exist.
Symptoms
Blurred or distorted vision at all distances is typical.
Patients squint and get headaches.
Night vision may be worse.
Therefore, ask about eye strain.
Astigmatism in Children
Significant astigmatism can cause amblyopia.
Screen children with a strong family history.
Glasses prevent visual loss.
So treat early (see amblyopia overview).
Testing for Astigmatism
Refraction measures the cylinder power and axis.
Keratometry and topography map the cornea.
Cycloplegia helps in children.
Also check for irregularity.
Glasses
Cylindrical lenses correct astigmatism.
New glasses may feel strange at first.
Adaptation takes days to weeks.
So warn patients about adjustment.
Contact Lenses
Toric soft lenses correct moderate astigmatism.
Rigid gas-permeable lenses correct irregular corneas.
Fit and rotation are important.
Therefore, follow patients closely.
Surgical Correction
LASIK, PRK and SMILE reduce astigmatism.
Toric intraocular lenses correct it at cataract surgery (see toric IOL misalignment).
Relaxing incisions are an option for lower amounts.
Also discuss limits.
Astigmatism After Surgery
Cataract surgery, corneal grafts and pterygium can change astigmatism (see post-keratoplasty astigmatism).
Monitor after surgery.
Sutures or incisions can be adjusted.
So plan correction.
Astigmatism and Keratoconus
Progressive irregular astigmatism suggests keratoconus.
Topography reveals steepening.
Early treatment preserves vision.
Therefore, refer when asymmetry grows.
Living With Astigmatism
Take regular eye exams.
Use proper lighting for reading.
Take screen breaks to reduce strain.
Also update glasses as needed.
Astigmatism: Practical Summary
Measure the cylinder and axis and map the cornea.
If irregular, consider rigid lenses and screen for ectasia.
Because uncorrected astigmatism affects children, prescribe early.
Finally, explain the adjustment period.
Pitfalls to Avoid
- Do not miss keratoconus in progressive astigmatism
- Never ignore amblyopia risk in children
- Avoid prescribing full cylinder changes without warning
- Do not forget post-surgical astigmatism
Astigmatism and Eye Strain
Uncorrected astigmatism makes the eyes work harder.
Patients feel tired after reading.
Because strain can cause headache, check refraction.
Therefore, new glasses often relieve symptoms.
Lens Design
Progressive and high-index lenses can distort images.
Wrap frames add peripheral aberrations.
Because adaptation differs, choose lens designs with care.
So advise patients to keep frames similar.
Astigmatism in Cataract Surgery
Preoperative corneal astigmatism affects results.
Measure it with topography and keratometry.
If the amount is more than one diopter, consider a toric lens.
Because alignment is critical, mark the axis carefully.
Astigmatism and LASIK
Laser correction treats the cylinder along with sphere.
Wavefront-guided options reduce higher-order aberrations.
Because corneal thickness limits treatment, check topography.
Therefore, screen for ectasia risk.
Astigmatism and Dry Eye
An unstable tear film fluctuates the optics.
Measurements may be unreliable.
Because dryness blurs vision, treat the surface.
Then repeat the refraction.
Older Adults
Against-the-rule astigmatism increases with age.
Cataract changes it further.
Because glasses need updating, review them every two years.
So keep prescriptions current.
Patient Questions
Patients ask whether it gets worse with age.
It may change gradually, so check regularly.
They ask if reading in the dark causes it.
There is no evidence, so reassure them.
Corneal Reshaping Lenses
Corneal reshaping lenses can reduce low astigmatism.
Effects are temporary and require nightly wear.
Because infection risk exists, teach hygiene.
Therefore, follow patients closely.
Astigmatism in Children and Learning
Children with high astigmatism may avoid reading.
Parents may think it is laziness.
Because glasses restore clear images, test vision early.
Therefore, ask teachers about visual behavior.
Astigmatism: Key Message
Most astigmatism is easy to correct with lenses.
If the cornea is irregular, expect a longer work-up.
Because progression signals ectasia, monitor topography.
Finally, explain the adjustment to new glasses.
Astigmatism: Practical Tips for Clinics
Ask patients to bring old glasses to compare.
If the axis changes a lot, recheck the refraction.
Because small changes can feel large, explain them.
Therefore, give patients time to adapt.
For the latest studies, see the PubMed results for astigmatism.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Read SA, Vincent SJ, Collins MJ. The visual and functional impacts of astigmatism and its clinical management. Ophthalmic Physiol Opt. 2014;34:267-294.
- Hashemi H, Fotouhi A, Yekta A, et al. Global and regional estimates of prevalence of refractive errors. J Curr Ophthalmol. 2018;30:3-22.
- Wallace DK, Christiansen SP, Sprunger DT, et al. Pediatric eye evaluations preferred practice pattern. Ophthalmology. 2018;125:P184-P227.
- Rabinowitz YS. Keratoconus. Surv Ophthalmol. 1998;42:297-319.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.