DME treatment has changed dramatically since the introduction of anti-VEGF drugs.
Most eyes with vision loss now start with injections.
Steroids and laser still have clear roles.
Defining Center-Involved DME
Center-involved edema thickens the foveal center on OCT.
Non-center-involved edema spares the fovea.
This distinction guides treatment (see diabetic macular edema).
Therefore, order OCT for every suspected case.
When to Treat
Treat center-involved edema with reduced vision.
Observation is reasonable when vision is good and OCT is stable.
Close follow-up is essential.
So decide based on vision and anatomy.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteFirst-Line DME Treatment: Anti-VEGF
Ranibizumab, aflibercept and bevacizumab improve vision and reduce thickness.
Injections are given monthly at first and then spaced out.
Protocol T compared the three drugs.
Also, aflibercept performed better when baseline vision was 20/50 or worse.
Bevacizumab as a Starting Option
Bevacizumab is cheap and effective in eyes with better vision.
Many centers start with it and switch if the response is weak.
Switching is justified after several injections with little change.
Therefore, cost often guides the first choice.
Newer Agents
Faricimab targets VEGF and angiopoietin-2.
Trials showed vision gains with longer intervals between injections.
High-dose aflibercept also extends the interval.
So newer drugs may reduce treatment burden.
Role of Steroids in DME Treatment
Dexamethasone implants help eyes with a poor response to anti-VEGF.
They suit pseudophakic eyes best.
Cataract and pressure rise are the main risks (see steroid induced cataract).
Therefore, monitor pressure at each visit.
Evidence for Steroid Implants
The MEAD trials showed vision gains with dexamethasone implants.
Fluocinolone implants also help chronic edema.
Compared with anti-VEGF, effects are less rapid.
So they are second-line in most cases.
Macular Laser
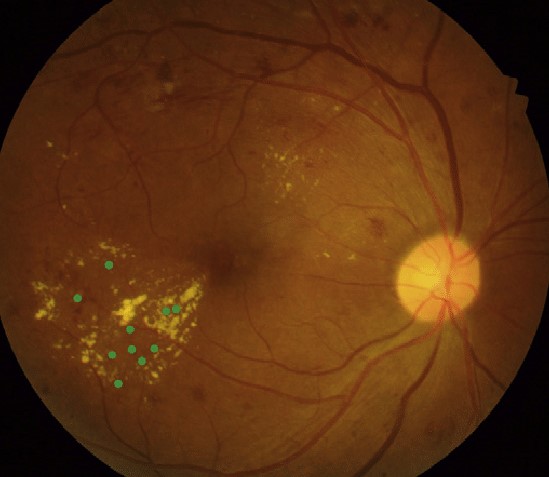
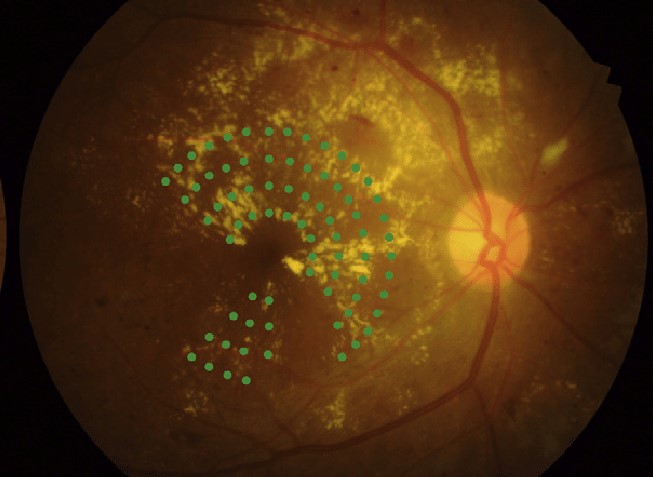
Focal laser reduces leakage from microaneurysms.
It was the standard before injections.
Now it has a limited role in non-center-involved edema.
Also, it may help some eyes with persistent leakage.
Combining Treatments
Early trials combined laser with ranibizumab.
Combined therapy reduced the number of injections in some eyes.
However, vision outcomes were similar to injections alone.
So combination treatment is selective.
Systemic Control
Good control of glucose, blood pressure and lipids supports treatment.
Kidney disease and sleep apnea also worsen edema.
Coordinate with the physician.
Therefore, treat the whole patient.
Monitoring Response
Check vision and OCT thickness at each visit.
Look for persistent fluid after three to six injections.
Consider switching if the response is poor.
Also review adherence to the schedule.
Counseling About DME Treatment
Explain that injections stabilize vision but rarely cure the disease.
Many patients need treatment for years.
Missed visits lead to worse outcomes.
So support attendance.
DME Treatment: Practical Summary
Start with anti-VEGF for center-involved edema with vision loss.
If the response is weak, change the drug or add a steroid.
Because systemic factors matter, optimize them.
Finally, follow patients closely.
Pitfalls to Avoid
- Do not rely on laser alone for center-involved edema
- Never forget cataract and pressure with steroids
- Avoid stopping injections too soon
- Do not ignore systemic control
DME Treatment and Treat-and-Extend
Treat-and-extend regimens lengthen the interval when the macula is dry.
This reduces visits without losing vision.
Because DME often relapses, keep a short interval at first.
Then extend gradually.
DME Treatment and Pregnancy
Anti-VEGF drugs are generally avoided in pregnancy.
Laser or observation may be used instead.
Because edema often improves after delivery, discuss options.
Therefore, involve the obstetric team.
DME Treatment in Patients With Heart Disease
Systemic exposure to anti-VEGF is low but not zero.
Patients with recent stroke or infarct need discussion.
Because benefits usually outweigh risks, treat carefully.
Then document the decision.
DME Treatment and Vitrectomy
Eyes with traction need surgery.
Vitrectomy may help persistent edema with vitreomacular traction.
Because results vary, use OCT to select cases.
So refer when traction is present.
DME Treatment: Practical Summary
Order an OCT, choose an anti-VEGF drug and set a schedule.
If response is poor, review adherence and systemic control.
Because steroids carry risks, use them in selected eyes.
Finally, track vision and thickness at every visit.
DME Treatment and Cost
Costs differ between drugs.
Bevacizumab is cheapest, while newer agents cost more.
If cost limits adherence, consider a staged approach.
Therefore, discuss it openly with patients.
For the latest studies, see the PubMed results for DME treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Diabetic Retinopathy Clinical Research Network; Wells JA, Glassman AR, Ayala AR, et al. Aflibercept, bevacizumab, or ranibizumab for diabetic macular edema. N Engl J Med. 2015;372:1193-1203.
- Boyer DS, Yoon YH, Belfort R Jr, et al. Three-year, randomized, sham-controlled trial of dexamethasone intravitreal implant in patients with diabetic macular edema. Ophthalmology. 2014;121:1904-1914.
- Wykoff CC, Abreu F, Adamis AP, et al. Efficacy, durability, and safety of intravitreal faricimab with extended dosing up to every 16 weeks in patients with diabetic macular oedema (YOSEMITE and RHINE). Lancet. 2022;399:741-755.
- Elman MJ, Aiello LP, Beck RW, et al. Randomized trial evaluating ranibizumab plus prompt or deferred laser or triamcinolone plus prompt laser for diabetic macular edema. Ophthalmology. 2010;117:1064-1077.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.