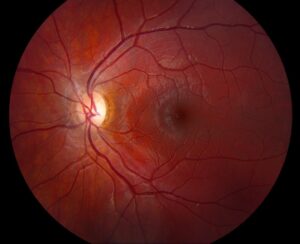
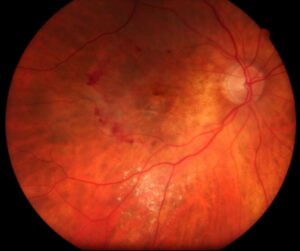
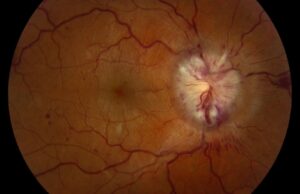
Pediatric retinal detachment is uncommon, and it differs from adult detachment in its causes, in the anatomy of the vitreous, and in the course after repair.
A child often presents late, because young patients do not report visual symptoms and may have lost vision in one eye for a long time before anyone notices.
The surgeon must consider trauma, inherited vitreoretinopathies, and congenital anomalies before assuming a typical rhegmatogenous mechanism.
What Is Pediatric Retinal Detachment?
Detachments in children are classified as rhegmatogenous, tractional, or exudative, as in adults, but the causes are very different.
Trauma is the most common cause in many series, followed by congenital and developmental abnormalities such as colobomas, high myopia, and persistent fetal vasculature (see persistent fetal vasculature).
Inherited vitreoretinopathies include Stickler syndrome, familial exudative vitreoretinopathy, and X-linked retinoschisis (see Stickler syndrome and X-linked retinoschisis).
Retinopathy of prematurity can leave a tractional detachment in infancy or later (see retinopathy of prematurity).
The detachment in a child is often caused by a retinal dialysis, a giant tear, or an atrophic hole, and less often by a horseshoe tear.
How Children Present
- Leukocoria or a new strabismus in a small child
- A parent noticing that the child does not see with one eye
- Reduced school performance or difficulty with sports
- Headache, squinting, or a head tilt
- Findings after trauma, such as hyphema, cataract, or vitreous hemorrhage
In older children, the history may include prior eye surgery, trauma, or known retinal disease.
Because the vitreous in a child is firmly attached and formed, the detachment often proceeds slowly and the retina may be less mobile than in adults.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteExamination
A complete examination of a child with suspected detachment often requires sedation or general anesthesia.
Perform indirect ophthalmoscopy with scleral depression, and use widefield imaging if it is available.
Examine the fellow eye, because many of the underlying conditions are bilateral and the other eye may need prophylaxis.
B-scan ultrasonography helps when the media are opaque because of hyphema, cataract, or vitreous hemorrhage (see B-scan ultrasonography).
A systemic and family history looks for connective tissue disease, hearing loss, cleft palate, and early-onset myopia that would suggest Stickler syndrome.
Management Principles
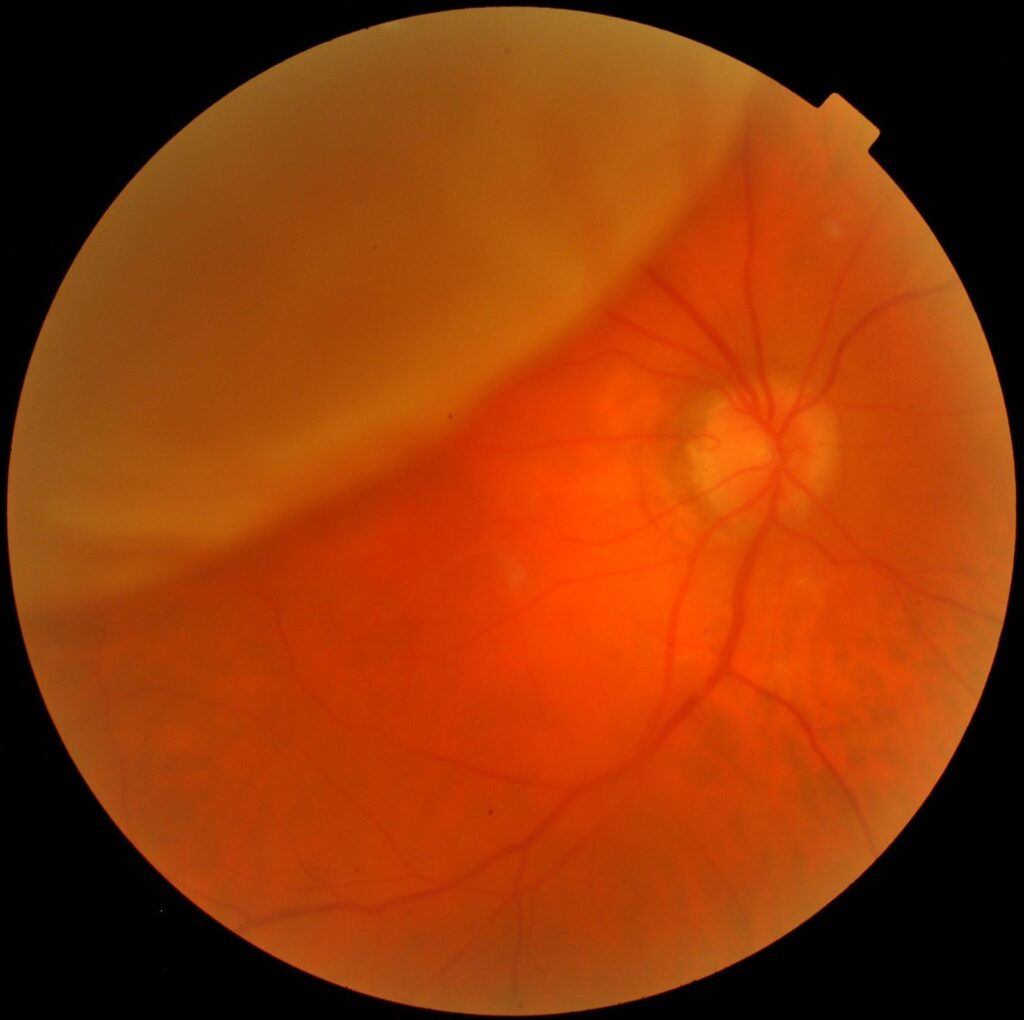
Surgical repair is the standard, and the timing depends on the type of detachment and on the child’s visual potential.
- Scleral buckle: commonly used for dialysis and atrophic holes in young phakic eyes with attached vitreous (see scleral buckle surgery)
- Vitrectomy: needed for tractional detachment, giant tears, and eyes with proliferative vitreoretinopathy (see pars plana vitrectomy)
- Silicone oil: frequently used when postoperative positioning is difficult in a young child
Gas is less convenient in young children who cannot posture, and silicone oil often requires a second operation to remove.
Proliferative vitreoretinopathy is more common and more aggressive in children, and the rate of redetachment is higher than in adults.
Visual Outcome and Amblyopia
Anatomical success is lower than in adults, and visual results depend on the duration of detachment and on the cause.
Children need amblyopia therapy after surgery, correction of refractive error, and protection of the fellow eye.
Regular follow-up is required for years, because late redetachment and cataract formation are common.
Families should receive written advice about trauma prevention, symptoms to report, and the need for genetic counselling when an inherited disorder is identified.
Special Situations
Retinal dialysis in a young patient is often related to trauma, and the inferotemporal quadrant is the common location (see retinal dialysis).
Detachments in Stickler syndrome often involve giant tears with a high rate of bilateral disease, and prophylactic laser or cryotherapy of the fellow eye is frequently advised.
Coats disease and familial exudative vitreoretinopathy can produce exudative or tractional detachments that need different management (see Coats disease).
Follow-Up and Counselling
Children need frequent early follow-up because redetachment and proliferative vitreoretinopathy are more likely, and the child may not describe symptoms.
Parents should be taught to look for squinting, covering one eye, or a change in behavior.
Protective eyewear for sports, and safe habits around toys and tools, are part of the advice.
Refer families to visual support services early if vision remains reduced, and arrange genetic evaluation when a hereditary condition is found.
The surgeon should also plan for the long term, since a child who has been repaired once may need further procedures, silicone oil removal, cataract surgery, and years of amblyopia care.
Setting this expectation with parents from the start improves cooperation with a long course of treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wenick AS, Barañano DE. Evaluation and management of pediatric rhegmatogenous retinal detachment. Saudi J Ophthalmol. 2012;26:255-263.
- Ryan SJ, Schachat AP, Wilkinson CP, et al, eds. Retina. 6th ed. Elsevier; 2018.
- Lambert SR, Lyons CJ, eds. Taylor and Hoyt’s Pediatric Ophthalmology and Strabismus. 5th ed. Elsevier; 2017.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
What is the most common cause of pediatric retinal detachment in most reported series?
Trauma leads the causes of detachment in children, followed by congenital and developmental abnormalities such as coloboma, high myopia and persistent fetal vasculature. -
Which retinal break types most often underlie a rhegmatogenous detachment in a child?
Childhood detachments usually arise from a dialysis, a giant tear or an atrophic hole; the horseshoe tear of adult life is a less frequent culprit. -
Why does a retinal detachment in a child often progress slowly with a relatively immobile retina?
A child's vitreous remains formed and firmly adherent, so fluid spreads slowly and the detached retina moves less than in an adult eye. -
Which presentation in a small child should raise suspicion of retinal detachment?
Young children do not report lost vision, so leukocoria or a new squint is often the first sign a parent or clinician notices. -
What does a complete retinal examination of a young child with suspected detachment usually require?
Indirect ophthalmoscopy with scleral depression in a child commonly needs sedation or general anesthesia, and the fellow eye is examined at the same sitting. -
Which systemic features in a child with retinal detachment point toward Stickler syndrome?
The family and systemic history looks for connective tissue disease, hearing loss, cleft palate and early myopia, which together suggest Stickler syndrome. -
In Stickler syndrome with a detachment in one eye, what is frequently advised for the fellow eye?
Stickler detachments often involve giant tears and are frequently bilateral, so prophylactic laser or cryotherapy of the fellow eye is commonly recommended. -
Why is silicone oil frequently preferred over gas tamponade in young children?
Gas depends on posturing that a young child cannot maintain, so oil is often chosen, accepting that a second operation is usually needed to remove it. -
Which postoperative complication is both more common and more aggressive in children than in adults?
Proliferative vitreoretinopathy behaves more aggressively in children, and the redetachment rate after repair is higher than in adult eyes. -
Beyond reattaching the retina, what does a child need for the best visual result?
Anatomical success alone is not enough; children require amblyopia treatment, correction of refractive error and protection of the fellow eye.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.