Glaucoma progression is the signal that treatment is not enough.
Deciding whether a field has truly worsened is hard.
Variability, learning effects and artifacts all mislead.
Why Progression Matters
Slowing progression is the goal of treatment.
Patients who progress quickly may go blind within their lifetime.
Detecting it early allows treatment to change in time.
Therefore, track change systematically (see primary open-angle glaucoma).
Baseline Fields and Glaucoma Progression
Obtain two to three tests in the first year.
This builds a reliable baseline.
Early fields have more learning effect.
So do not judge a single test.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteEvent-Based Analysis of Glaucoma Progression
Event analysis flags a new defect that exceeds test variability.
It answers whether a change happened.
It does not give the speed of loss.
Also confirm any event on repeat testing.
Trend-Based Analysis of Glaucoma Progression
Trend analysis plots the visual field index against time.
The slope shows the rate of loss.
A steep negative slope means rapid progression.
Therefore, trends help with prognosis.
How Many Fields Detect Glaucoma Progression
Studies suggest about six tests in the first two years help detect fast progressors.
More frequent testing gives faster detection.
Costs and patient burden limit this.
So tailor the frequency to risk.
Causes of False Glaucoma Progression
Cataract, small pupils and poor attention lower sensitivity.
Fatigue and learning effects also play a part.
Always review reliability indices.
Also check the pupil and media.
Optic Disc and OCT Change
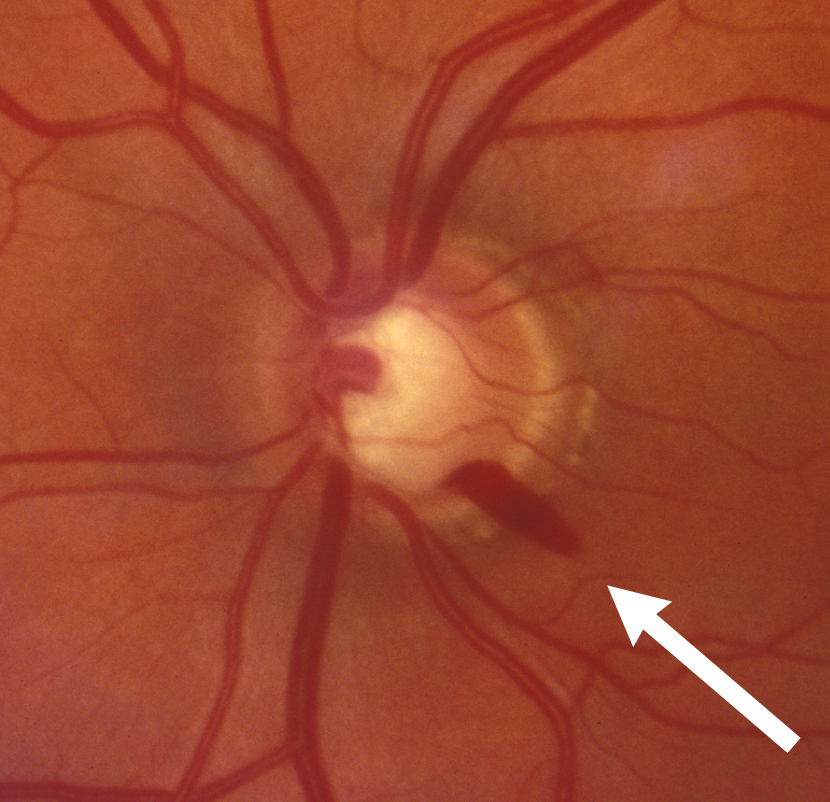
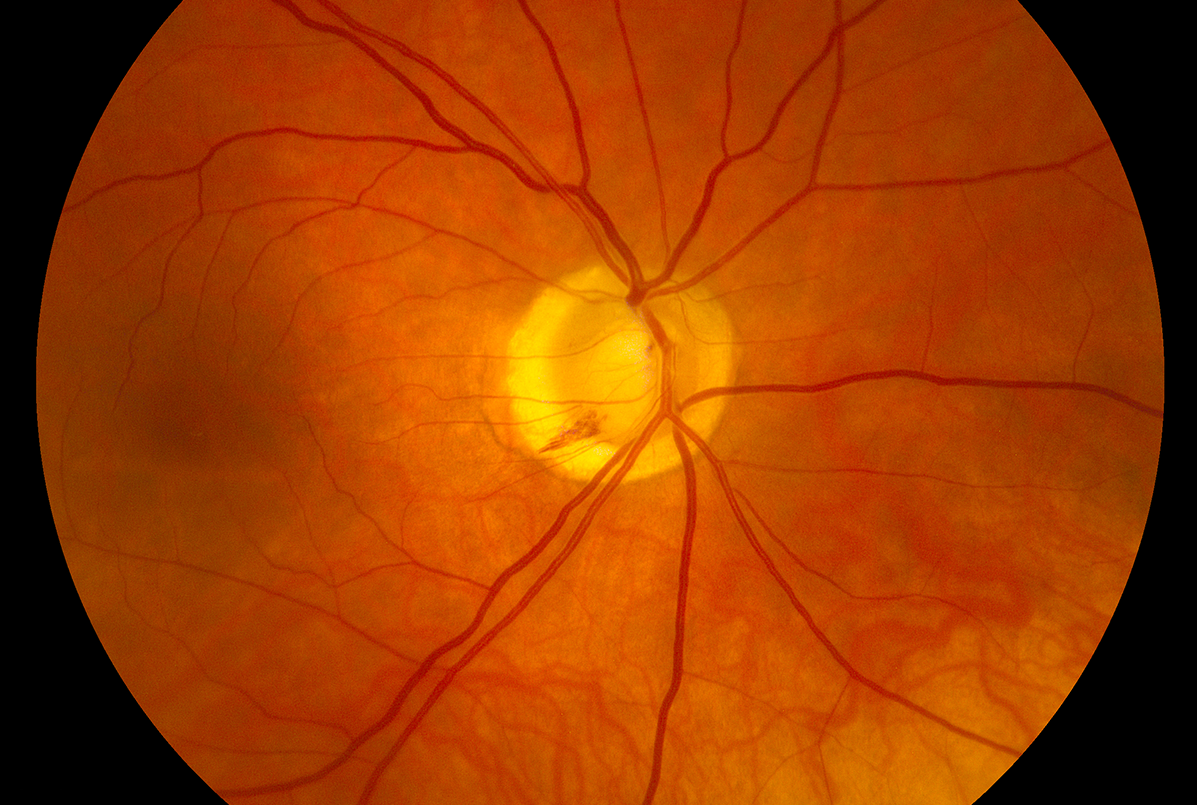
Disc photographs show enlarging cupping or new hemorrhages.
OCT shows thinning of the nerve fiber layer.
A disc hemorrhage often precedes field loss.
So combine structure with function.
Structure Versus Function
Structure may change before function in early disease.
In advanced disease, OCT reaches a floor.
Fields then become more informative.
Therefore, use both across the disease course.
Intraocular Pressure and Glaucoma Progression
Higher mean pressure and large fluctuations increase risk.
The Early Manifest Glaucoma Trial showed progression falls with each millimeter of pressure reduction.
Check pressure at each visit.
Also reset the target when progression occurs.
Risk Factors for Fast Glaucoma Progression
Older age, thin cornea and exfoliation raise risk.
Disc hemorrhages and cardiovascular disease also contribute.
Pseudoexfoliation needs close care (see pseudoexfoliation syndrome).
Therefore, identify these patients early.
Responding to Progression
Check adherence and technique first.
Then lower the target pressure with added drops, laser or surgery.
Repeat fields to confirm the new course.
So act on confirmed change.
Communicating With Patients
Show patients their trend lines.
Explain that glaucoma is slow but can accelerate.
Discuss lifestyle and treatment adherence.
Also set realistic goals.
Pitfalls to Avoid
- Do not change treatment based on one field
- Never ignore reliability indices
- Avoid overlooking cataract as a cause of field loss
- Do not forget disc hemorrhages
Glaucoma Progression in Normal-Tension Disease
Patients with normal pressure can still progress.
Because pressure is already low, further reduction is harder.
If progression continues, look for vascular factors.
Therefore, review blood pressure and sleep (see normal-tension glaucoma).
Glaucoma Progression and Cataract Surgery
Cataract surgery can lower pressure and lift field sensitivity.
When you compare fields, note the surgery date.
Because the baseline changes, reset it after surgery.
Then continue trend analysis from the new baseline.
Glaucoma Progression and Central Fixation
Early central involvement carries a high risk to daily function.
Because small central defects matter, add 10-2 testing.
If central points are involved, treat more aggressively.
Therefore, check the macula in all patients.
Glaucoma Progression and Life Expectancy
A slow rate may be acceptable in an older patient.
However, the same rate in a young patient threatens vision.
Because remaining life matters, estimate the future loss.
Then set the target accordingly.
Glaucoma Progression and Imaging Artifacts
OCT segmentation errors can mimic change.
When images look different, review the scans manually.
Because myopia affects thickness, interpret with care.
Therefore, confirm with the field.
Glaucoma Progression: Practical Summary
Obtain a strong baseline and repeat tests at set intervals.
If a trend appears, confirm it on repeat testing.
Because adherence is a common cause, review it first.
Finally, adjust the target pressure.
Glaucoma Progression and Patient Education
Explain that treatment slows the disease but does not restore lost vision.
If patients understand the goal, they keep up with the drops.
Because fast progressors need action, share the trend lines.
Then book the next test before the patient leaves.
For the latest studies, see the PubMed results for glaucoma progression.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Chauhan BC, Garway-Heath DF, Goni FJ, et al. Practical recommendations for measuring rates of visual field change in glaucoma. Br J Ophthalmol. 2008;92:569-573.
- Heijl A, Leske MC, Bengtsson B, et al. Reduction of intraocular pressure and glaucoma progression: results from the Early Manifest Glaucoma Trial. Arch Ophthalmol. 2002;120:1268-1279.
- Leske MC, Heijl A, Hussein M, et al. Factors for glaucoma progression and the effect of treatment: the Early Manifest Glaucoma Trial. Arch Ophthalmol. 2003;121:48-56.
- Gedde SJ, Vinod K, Wright MM, et al. Primary open-angle glaucoma preferred practice pattern. Ophthalmology. 2021;128:P71-P150.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.