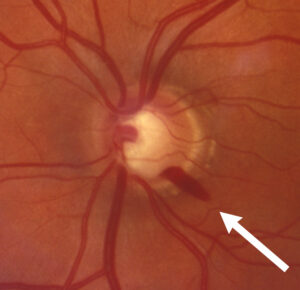
Uveitic glaucoma is elevated intraocular pressure occurring in the setting of intraocular inflammation, and it is genuinely complex to manage because it can arise from several different, sometimes coexisting, mechanisms, and because one of the standard treatments for the underlying uveitis, corticosteroids, can itself raise pressure further, creating a situation where controlling one problem risks worsening the other.
Mechanisms of Elevated Pressure in Uveitis
- Trabeculitis: direct inflammation of the trabecular meshwork itself, reducing aqueous outflow
- Inflammatory cells and debris mechanically obstructing the trabecular meshwork
- Posterior synechiae, causing pupillary block and, if extensive (iris bombe), acute angle closure
- Peripheral anterior synechiae, forming over time from chronic inflammation and progressively closing the angle
- Neovascular glaucoma, from chronic ischemia in severe or prolonged uveitis
- Steroid-induced ocular hypertension, from the anti-inflammatory treatment itself, in susceptible patients (see steroid-induced glaucoma)
- Rarely, hypotony alternating with pressure spikes in eyes with fluctuating ciliary body function
More than one mechanism is often present simultaneously, which is part of why management requires a broader assessment than simply lowering pressure with the usual glaucoma medications.
Clinical Evaluation
- Gonioscopy is essential, to assess for synechial angle closure, neovascularization, and the degree of open, functioning angle remaining
- Assessment of anterior chamber activity, to determine whether active inflammation is contributing to current pressure elevation
- A careful medication history, including the type, potency, route, and duration of any corticosteroid use, since steroid response varies by individual and by formulation
- Optic nerve and visual field assessment, interpreted with the understanding that uveitic eyes may have baseline optic nerve or macular changes from the underlying inflammatory disease that complicate standard glaucoma assessment
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteManagement
Treating the Underlying Inflammation
When active inflammation is a significant contributor to elevated pressure, controlling the uveitis itself is a core part of pressure management, not a separate issue, since resolving trabeculitis and clearing inflammatory debris can substantially lower pressure without escalating glaucoma-specific treatment.
Choosing a Steroid Strategy That Limits Pressure Risk
- Where possible, using the lowest effective corticosteroid potency and route for adequate inflammatory control, recognizing that some patients need potent or prolonged steroid treatment regardless
- Considering steroid-sparing systemic immunosuppression earlier in patients who show a pronounced steroid pressure response, to reduce reliance on corticosteroids for long-term control
- Close IOP monitoring after starting or escalating any corticosteroid, particularly in known steroid responders
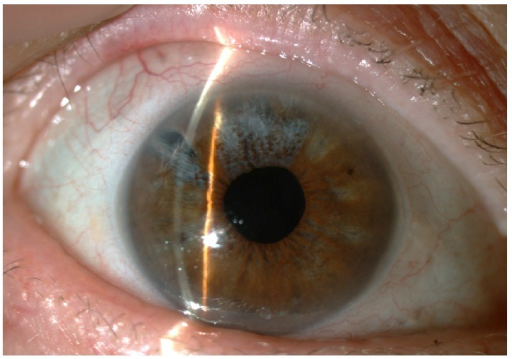
Medical IOP-Lowering Therapy
- Aqueous suppressants, including topical beta-blockers and carbonic anhydrase inhibitors, are generally preferred as first-line pressure-lowering agents in uveitic glaucoma
- Prostaglandin analogues are used more cautiously, given a theoretical concern about promoting further intraocular inflammation in some patients, though they are still used in many cases, particularly when inflammation is well controlled
- Miotics are generally avoided, since they can worsen posterior synechiae formation and pupillary block risk in an inflamed eye
Managing Synechiae and Angle Closure
Laser peripheral iridotomy addresses pupillary block from posterior synechiae or iris bombe, and prompt recognition and treatment of this mechanism is important given its potential for rapid, severe pressure elevation (see Nd:YAG laser peripheral iridotomy).
Surgical Management
When medical therapy and treatment of the underlying inflammation are insufficient, surgical options include trabeculectomy, often with antimetabolite use, and glaucoma drainage device implantation, which is frequently favored in uveitic glaucoma given generally better outcomes than trabeculectomy in eyes with a history of significant intraocular inflammation, along with cyclophotocoagulation for refractory cases.
Surgery in an actively inflamed eye carries a higher risk of complications, so achieving reasonable inflammatory control before elective surgical intervention, when the clinical situation allows, improves the likelihood of a good outcome.
Prognosis
Outcomes depend heavily on how well the underlying uveitis can be controlled and on the specific mechanism or mechanisms driving pressure elevation in a given patient.
Uveitic glaucoma tends to require more intensive, individualized, and closely monitored management than primary open-angle glaucoma, reflecting the interplay between two active disease processes rather than a single, more predictable pathway to optic nerve damage.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Sng CC, Ang M, Barton K. Uveitic glaucoma: a review. Clin Exp Ophthalmol. 2015;43:1-14.
- Kesav N, Palestine AG, Kahook MY, Pantcheva MB. Current management of uveitis-associated ocular hypertension and glaucoma. Surv Ophthalmol. 2020;65:397-407.
- Sallam A, Sheth HG, Habot-Wilner Z, Lightman S. Outcome of trabeculectomy with mitomycin C in uveitic glaucoma. Ophthalmology. 2010;117:1655-1660.
- Ceballos EM, Beck AD, Lynn MJ. Trabeculectomy with antiproliferative agents in uveitic glaucoma. J Glaucoma. 2002;11:189-196.
Test yourself
A few questions straight from this article.
-
What makes uveitic glaucoma particularly difficult to manage?
Pressure can rise by several coexisting mechanisms, and the steroids used to control the inflammation may raise it further, so treating one problem risks worsening the other. -
What is trabeculitis as a mechanism of raised pressure in uveitis?
Trabeculitis is inflammation of the trabecular meshwork itself, which reduces outflow, distinct from mechanical blockage by inflammatory cells and debris. -
How does iris bombe raise intraocular pressure in uveitis?
Posterior synechiae produce pupillary block, and when extensive enough to cause iris bombe they can precipitate acute angle closure. -
Why is gonioscopy essential in assessing uveitic glaucoma?
Gonioscopy assesses synechial angle closure, angle neovascularization, and how much open, functioning angle is left to drain aqueous. -
Which agents are generally first-line for lowering pressure in uveitic glaucoma?
Aqueous suppressants, namely topical beta-blockers and carbonic anhydrase inhibitors, are preferred as first-line pressure-lowering therapy in uveitic glaucoma. -
Why are miotics generally avoided in uveitic glaucoma?
In an inflamed eye miotics promote posterior synechiae formation and increase the risk of pupillary block, so they are generally avoided. -
Why are prostaglandin analogues used cautiously in uveitic glaucoma?
There is a theoretical concern that prostaglandin analogues promote further intraocular inflammation, although they are still used in many cases once inflammation is well controlled. -
How is pupillary block from posterior synechiae treated in uveitic glaucoma?
Laser peripheral iridotomy relieves pupillary block from posterior synechiae or iris bombe, and prompt recognition matters because pressure can rise rapidly and severely. -
In which patients with uveitis is steroid-sparing immunosuppression considered earlier?
Patients with a marked steroid pressure response are moved toward systemic steroid-sparing immunosuppression earlier, to reduce reliance on corticosteroids long term. -
Which glaucoma operation is frequently favoured in eyes with uveitic glaucoma?
Drainage devices generally give better outcomes than trabeculectomy in eyes with a history of significant intraocular inflammation, with cyclophotocoagulation kept for refractory cases.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.