
B-scan ultrasonography gives a cross-sectional view of the eye and orbit using sound rather than light, which makes it the tool of choice whenever the ocular media are too opaque to see through directly.
A dense cataract, a vitreous hemorrhage, or a hazy cornea will defeat a dilated fundus exam and an OCT scan alike, but none of them meaningfully block ultrasound.
That single property is why B-scan remains indispensable in a subspecialty otherwise dominated by optical imaging.
It also requires no pupillary dilation, no patient fixation on a target, and very little cooperation beyond keeping the eye still for a few seconds, which makes it usable in settings where OCT or fundus photography simply cannot be performed.
How It Works
A handheld probe placed against the closed eyelid, or directly on the anesthetized globe, emits high-frequency sound waves and records the echoes that return from tissue interfaces of differing density.
The B-scan format displays these echoes as a two-dimensional cross-sectional image, in contrast to the older A-scan format, which shows the same information as a one-dimensional spike pattern used mainly for axial length and lesion reflectivity measurements.
Most clinical B-scan units let the examiner scan through multiple planes in real time, which is what allows a kinetic exam rather than a single static picture.
A-scan and B-scan are complementary rather than competing: many examiners still obtain an A-scan trace through an area of interest identified on B-scan, since the spike pattern gives a more precise readout of internal reflectivity than the grayscale B-scan image alone.
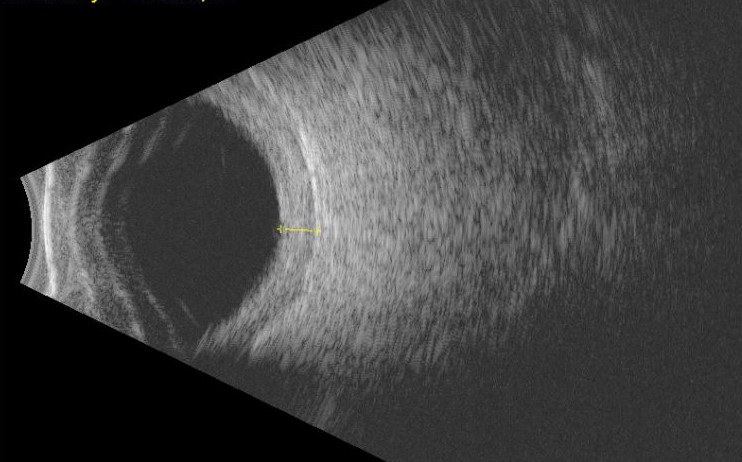
Core Clinical Uses
The single most common trigger for ordering a B-scan in everyday practice is simply a fundus that cannot be adequately visualized, whatever the specific cause.
- Detecting retinal detachment behind a dense cataract or vitreous hemorrhage, where the retina appears as a highly reflective, mobile membrane attached at the optic disc and ora serrata
- Distinguishing vitreous hemorrhage from other causes of a poor view, based on echo pattern and mobility on kinetic scanning
- Identifying and measuring intraocular tumors such as choroidal melanoma, including their internal reflectivity, shape, and any extrascleral extension
- Evaluating posterior vitreous detachment, particularly when it needs to be distinguished from a shallow retinal detachment
- Assessing globe integrity and detecting an intraocular foreign body after trauma, when direct visualization is limited by hyphema, corneal edema, or lid swelling
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteReading the Scan: Basic Principles
Echo reflectivity is described relative to the sensitivity gain of the machine, with a highly reflective structure like sclera or a fibrous membrane appearing bright and a low-reflectivity structure like clear vitreous appearing largely dark.
Mobility is assessed dynamically by asking the patient to move the eye and watching how a structure behaves afterward: a detached retina snaps back into a taut, folded configuration and remains tethered at the disc, while a posterior vitreous detachment moves more freely and does not carry that fixed attachment.
Shape and internal characteristics matter most for mass lesions, where a choroidal melanoma classically shows low-to-medium internal reflectivity with a mushroom or dome configuration, features that help separate it from a hemorrhagic or inflammatory mass with a very different acoustic signature.
Kinetic Versus Static Technique
A kinetic exam, in which the probe is moved across the globe while the patient shifts gaze in different directions, is what allows the examiner to trace the full extent of a detachment or mass rather than relying on one fixed cut.
Static images are useful for documentation and for precise measurements once the area of interest has been located, but a static-only exam risks missing a lesion or a detachment confined to a quadrant that was never directly imaged.
Both techniques are complementary in a complete exam, and an experienced examiner moves fluidly between the two rather than treating them as separate steps.
Limitations
B-scan resolution is coarser than optical imaging, so it cannot resolve fine retinal layer detail the way OCT does, and it is a poor tool for anything requiring micron-level precision.
Interpretation is also fairly operator-dependent, since accurate probe positioning and angle materially change what structures are actually being sampled, and a poorly performed scan can both miss real pathology and generate artifacts that mimic disease.
Building real proficiency takes deliberate practice under supervision, in much the same way that slit-lamp and indirect ophthalmoscopy skills do, and it is not a technique that translates reliably from reading about it alone.
It remains, despite these limits, the only practical way to look behind media too opaque for any optical method, which is precisely the clinical gap it was designed to fill.
Once the media clear, whether after cataract surgery or resolution of a vitreous hemorrhage, findings suggested on B-scan are routinely reconfirmed with direct examination and optical imaging, since ultrasound findings alone rarely dictate a final treatment plan on their own.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Byrne SF, Green RL. Ultrasound of the Eye and Orbit.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous.
- Coleman DJ, Silverman RH, Chabi A, et al. High-resolution ultrasonic imaging of the posterior segment. Ophthalmology.
- Shields JA, Shields CL. Atlas of intraocular tumors. Lippincott Williams & Wilkins.
Test yourself
A few questions straight from this article.
-
Why is B-scan ultrasonography the imaging tool of choice when the ocular media are opaque?
A dense cataract, vitreous haemorrhage or hazy cornea defeats both a dilated fundus exam and OCT, but none of them meaningfully blocks ultrasound. -
What does an A-scan trace add once a lesion has been located on B-scan?
The A-scan shows echoes as a one-dimensional spike pattern, which quantifies internal reflectivity more precisely than the grayscale B-scan image can. -
How does a retinal detachment appear on B-scan behind a dense cataract?
The detached retina shows as a brightly reflective, mobile membrane that stays anchored at the optic disc and the ora serrata. -
Which kinetic feature separates a retinal detachment from a posterior vitreous detachment on B-scan?
On kinetic scanning a detached retina snaps back into a taut, folded shape and remains fixed at the disc, whereas a posterior vitreous detachment moves freely without that attachment. -
Which acoustic pattern on B-scan is classically described for choroidal melanoma?
Choroidal melanoma typically shows low-to-medium internal reflectivity in a mushroom or dome configuration, an acoustic signature distinct from haemorrhagic or inflammatory masses. -
How do clear vitreous and sclera differ in appearance on a B-scan image?
Reflectivity is read relative to machine gain: highly reflective structures such as sclera or a fibrous membrane appear bright, while low-reflectivity clear vitreous appears largely dark. -
What is B-scan used for after ocular trauma when hyphema and lid swelling block the view?
When hyphema, corneal oedema or lid swelling prevents direct visualisation, B-scan is used to check that the globe is intact and to detect a retained intraocular foreign body. -
What advantage does kinetic B-scan technique offer over a static-only examination?
Moving the probe while the patient shifts gaze follows a lesion across its whole extent. A static-only exam can miss pathology confined to a quadrant that was never imaged. -
Which limitation applies to B-scan ultrasonography compared with optical coherence tomography?
B-scan resolution is coarser than optical imaging, so it cannot resolve individual retinal layers and is a poor choice when micron-level precision is needed. -
What is done with B-scan findings once opaque media clear after cataract surgery or haemorrhage resolution?
Ultrasound findings alone rarely dictate a final treatment plan, so once the view improves they are routinely rechecked with direct examination and optical imaging.
