
An episcleral nevus is a benign, typically flat, pigmented lesion sitting beneath the conjunctiva at the level of the episclera, and distinguishing it correctly from conjunctival melanoma and from other causes of ocular surface pigmentation is one of the more common practical challenges in evaluating a pigmented lesion at the slit lamp, since the stakes of missing a genuinely malignant lesion make careful, systematic assessment worthwhile even for lesions that look reassuringly stable.
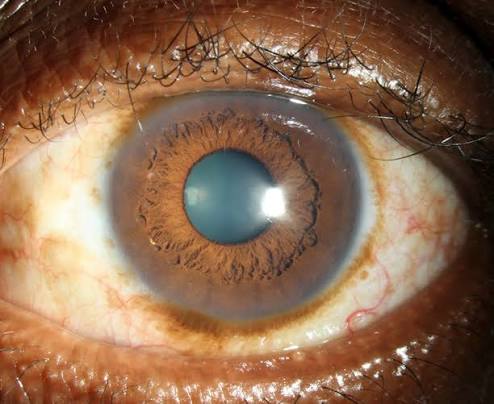
Where Episcleral Nevi Sit
Unlike a conjunctival nevus, which arises within the conjunctival epithelium itself and is typically mobile over the underlying sclera when the conjunctiva is gently moved with a cotton-tip applicator, an episcleral nevus sits at a deeper level, beneath the conjunctiva, and does not move independently when the overlying conjunctiva is manipulated, a distinction that can be a useful clinical clue during examination.
Clinical Features
- A flat, well-demarcated, typically slate-gray to brown pigmented patch
- Located beneath an intact, freely mobile conjunctiva, which itself moves independently over the fixed pigmented lesion below
- Generally stable in size and appearance over long-term follow-up, a key reassuring feature distinguishing a benign nevus from a growing, potentially malignant process
- Usually asymptomatic and discovered incidentally during routine examination
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDifferential Diagnosis
- Conjunctival nevus, which is more superficial, within the conjunctiva itself, and characteristically mobile with the conjunctiva rather than fixed beneath it
- Conjunctival or, more rarely, episcleral melanoma, which requires careful exclusion given the serious implications of missing this diagnosis, though episcleral melanoma is considerably less common than nevus
- Ocular (or oculodermal) melanocytosis, which typically produces a more diffuse, patchy, slate-gray pigmentation pattern across a broader area of episclera and sclera, rather than the discrete, localized patch typical of a solitary nevus, and carries its own distinct implications for uveal melanoma surveillance (see iris mammillations for a related discussion of this association)
- Foreign body or other exogenous pigment deposition, relevant when there is a compatible history
Features That Favor a Benign, Stable Nevus
- Flat or minimally elevated profile
- Sharply demarcated borders
- Documented stability in size and appearance over serial examinations
- Absence of associated feeder vessels, surface irregularity, or secondary changes such as adjacent conjunctival injection out of proportion to a simple pigmented patch
Evaluation
- Careful slit-lamp examination assessing the lesion’s depth (superficial conjunctival versus deeper episcleral), mobility relative to the overlying conjunctiva, borders, and any associated vascularity
- Baseline photographic documentation, valuable for objectively assessing any future change, given how difficult subtle growth can be to judge from memory or written description alone
- Periodic follow-up examination, with the interval determined by the initial level of clinical suspicion, to confirm ongoing stability
When to Consider Biopsy
Biopsy is generally reserved for lesions showing documented growth, atypical features such as surface irregularity or prominent feeder vessels, or other findings raising genuine concern for a malignant process, rather than being routinely performed for a lesion with a reassuring, stable clinical appearance, since biopsy itself carries a small risk of inducing local tumor seeding if a genuinely malignant lesion is incompletely excised through an inappropriately planned procedure.
Prognosis
The great majority of episcleral pigmented lesions encountered in clinical practice are benign nevi that remain entirely stable and asymptomatic throughout a patient’s lifetime, requiring no treatment beyond periodic observation and reassurance.
A systematic approach, assessing depth, mobility, borders, and stability over time, allows the rare genuinely concerning lesion to be identified for biopsy while sparing the majority of patients with clearly benign findings from unnecessary intervention.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields CL, Fasiudden A, Mashayekhi A, Shields JA. Conjunctival nevi: clinical features and natural course in 410 consecutive patients. Arch Ophthalmol. 2004;122:167-175.
- Shields JA, Shields CL, Mashayekhi A, et al. Primary acquired melanosis of the conjunctiva: risks for progression to melanoma in 311 eyes. Ophthalmology. 2008;115:511-519.
- Shields CL, Demirci H, Karatza E, Shields JA. Clinical survey of 1643 melanocytic and nonmelanocytic conjunctival tumors. Ophthalmology. 2004;111:1747-1754.
- Damato B, Coupland SE. Conjunctival melanoma and melanosis: a reappraisal of terminology, classification and staging. Clin Exp Ophthalmol. 2008;36:786-795.
