Dry eye diagnosis relies on symptoms plus objective signs, because no single test confirms the disease.
The TFOS DEWS II report recommends a validated questionnaire and at least one marker of disturbed tear homeostasis, but the order of testing changes the results. A fixed sequence also helps separate aqueous deficiency from evaporative disease.
Why Dry Eye Diagnosis Needs a Sequence
Each test disturbs the tear film to some degree. For example, fluorescein shortens breakup time and a Schirmer strip triggers reflex tearing, so perform the least invasive tests first, then move to tests that touch the eye.
Step 1: Symptom Questionnaires in Dry Eye Diagnosis
Start with a validated tool such as the OSDI or the DEQ-5, since DEWS II uses an OSDI score of 13 or more, or a DEQ-5 score of 6 or more, as a positive screen. Also ask about screen use, contact lenses and when symptoms peak during the day.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteStep 2: History and Medications
Next, review drugs that dry the surface, such as antihistamines, antidepressants and isotretinoin, and ask about dry mouth, joint pain and prior refractive surgery. In addition, preserved glaucoma drops can create a toxic surface picture.
Step 3: Tear Osmolarity Before Drops
Measure osmolarity before you instill any dye or anesthetic. A value of 308 mOsm/L or more, or an interocular difference above 8 mOsm/L, supports dry eye, however, readings vary between visits, so treat a single borderline value with caution.
Step 4: Tear Breakup Time
Noninvasive breakup time comes first if a keratograph or topographer is available. Otherwise, instill a small volume of fluorescein, then ask the patient to blink and stare.
A breakup time under 10 seconds is generally considered abnormal, so average three readings, because single values fluctuate.
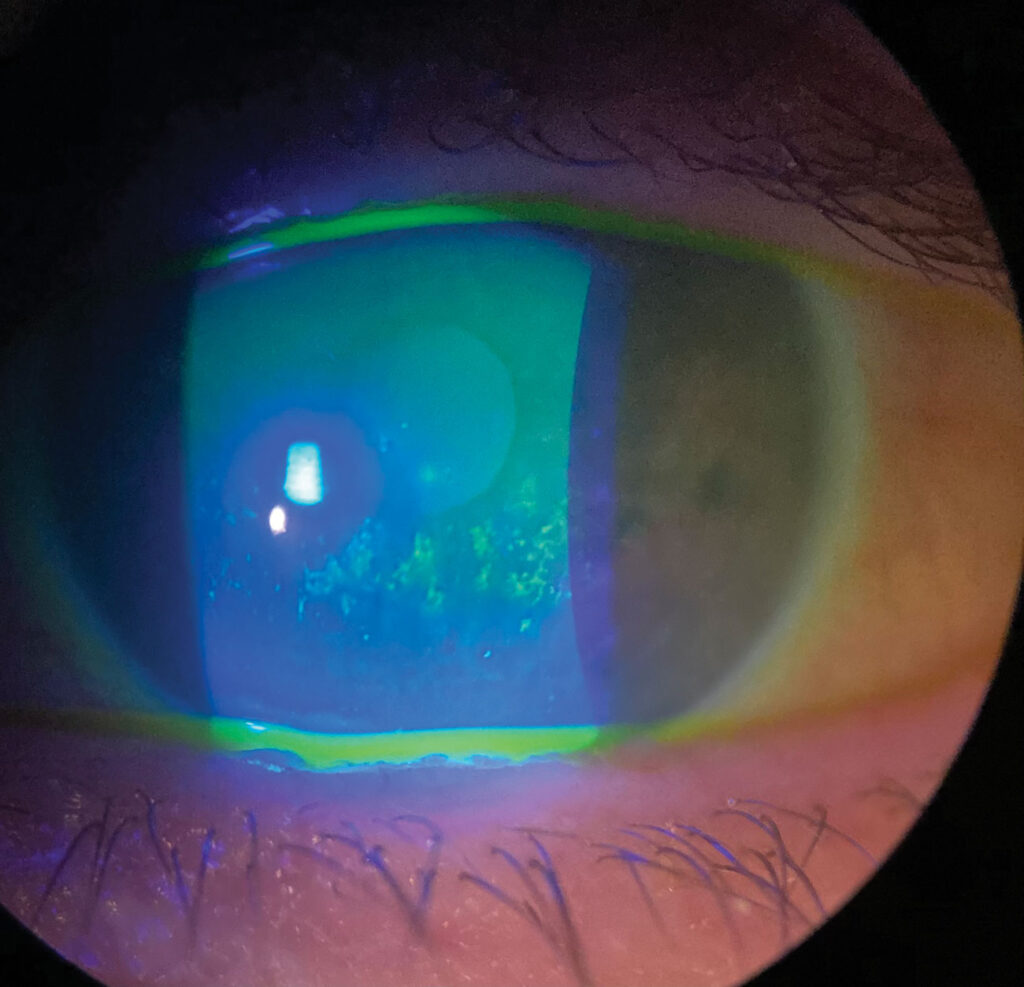
Step 5: Ocular Surface Staining in Dry Eye Diagnosis
Grade corneal fluorescein staining first, then conjunctival lissamine green staining. DEWS II thresholds include more than 5 corneal spots, more than 9 conjunctival spots, or lid wiper staining of 2 mm or longer.
In addition, location matters, since inferior staining suggests exposure (see staining patterns).
Step 6: Schirmer Testing in Dry Eye Diagnosis
Perform Schirmer last among the tear tests, because the strip irritates the conjunctiva. Without anesthesia, 5 mm or less in 5 minutes suggests marked aqueous deficiency.
However, repeatability is poor, and values overlap widely with normal eyes (see Schirmer normal values).
Step 7: Meibography and Lid Margins
Examine the lid margin for telangiectasia, plugged orifices and an irregular mucocutaneous junction. Then express the glands and grade the secretion.
As a result, infrared meibography adds a view of gland dropout and shortening. Lid margin disease often drives symptoms even when tear volume is normal.
Classifying the Subtype
Low Schirmer values with clear meibum point toward aqueous deficiency. In contrast, short breakup time with gland dropout points toward evaporative disease, and many patients show both, so treat the dominant component first.
When Symptoms and Signs Disagree
Symptoms and signs often correlate poorly in dry eye. For example, a patient may report severe burning with a nearly quiet surface, and in that case you should consider neuropathic ocular pain and check the response to topical anesthetic.
Conversely, neurotrophic corneas may stain heavily with few complaints.
When Tests Conflict in Dry Eye Diagnosis
High osmolarity with normal staining may reflect early disease. Meanwhile, a normal Schirmer with short breakup time usually means evaporative dry eye.
If results stay inconsistent, repeat testing on another day before you assign a label.
Red Flags and Mimics
Look for features that point away from simple dry eye:
- Unilateral symptoms or signs
- Vision that does not clear with blinking
- Corneal infiltrate, ulcer or thinning
- Itching with papillae, suggesting allergy
- Lagophthalmos or floppy eyelids
Systemic Workup in Dry Eye Diagnosis
Severe aqueous deficiency, especially with dry mouth, warrants a search for Sjögren disease. Therefore, order anti-SSA and anti-SSB antibodies and involve rheumatology when indicated, and also consider graft-versus-host disease and ocular cicatricial pemphigoid.
Explaining the Results to Patients
Explain that dry eye is chronic and that test results fluctuate. Show staining photos or meibography images when available.
Then link each abnormal test to a treatment step (see stepwise treatment). Finally, repeat the same tests in the same order at follow-up to judge trends.
Pitfalls to Avoid
- Do not instill fluorescein before measuring osmolarity
- Never diagnose dry eye from one Schirmer value
- Do not ignore lid margins when tear volume is normal
- Avoid labeling neuropathic pain as resistant dry eye


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wolffsohn JS, Arita R, Chalmers R, et al. TFOS DEWS II diagnostic methodology report. Ocul Surf. 2017;15:539-574.
- Craig JP, Nichols KK, Akpek EK, et al. TFOS DEWS II definition and classification report. Ocul Surf. 2017;15:276-283.
- Bron AJ, Evans VE, Smith JA. Grading of corneal and conjunctival staining in the context of other dry eye tests. Cornea. 2003;22:640-650.
- Lemp MA, Bron AJ, Baudouin C, et al. Tear osmolarity in the diagnosis and management of dry eye disease. Am J Ophthalmol. 2011;151:792-798.
- Nichols KK, Nichols JJ, Mitchell GL. The lack of association between signs and symptoms in patients with dry eye disease. Cornea. 2004;23:762-770.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.