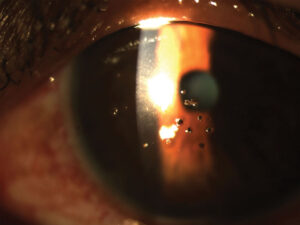
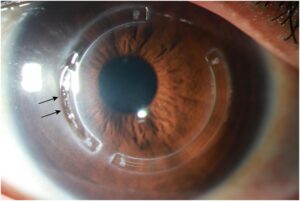
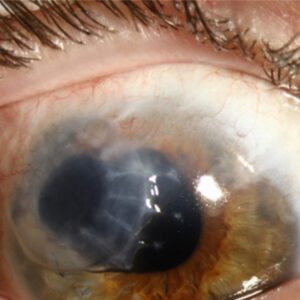
Staining the ocular surface is one of the most useful quick tests in the eye clinic.
A drop of fluorescein shows epithelial defects on the cornea, and lissamine green stains devitalized cells on the conjunctiva.
The location and shape of the staining are not random.
They show where the problem is, and they often point to the diagnosis before any further testing.
What the dyes show
- Fluorescein stains areas where the epithelium has lost its barrier function or is missing. It is best seen with a cobalt blue light and a yellow barrier filter.
- Lissamine green stains dead and degenerate cells and areas lacking mucin, and it is especially useful on the conjunctiva and lid margin. It stings less than rose bengal.
- Staining is graded by number and location, with several standard schemes, including the Oxford scheme (see dry eye disease).
Patterns by location
Superior
Staining on the upper cornea and conjunctiva suggests problems related to the upper lid:
- Superior limbic keratoconjunctivitis (see superior limbic keratoconjunctivitis)
- Vernal keratoconjunctivitis with giant papillae, or a shield ulcer (see vernal keratoconjunctivitis)
- Floppy eyelid syndrome (see floppy eyelid syndrome)
- Contact lens-related reactions and toxic reactions to solutions
- A foreign body under the upper lid, which creates vertical linear scratches
Inferior
Staining in the lower third of the cornea is common in:
- Exposure keratopathy and lagophthalmos (see exposure keratopathy)
- Blepharitis and meibomian gland dysfunction (see meibomian gland dysfunction)
- Topical drug toxicity, particularly from preserved drops
- Entropion or other lid malposition
Interpalpebral
Staining in the horizontal band exposed between the lids, on the cornea and the conjunctiva, is typical of dry eye disease and of neurotrophic problems.
Three and nine o’clock
Staining at the corneal edge, at the horizontal limbus, is characteristic of rigid gas-permeable contact lens wear, where the lens edge disturbs the tear film (see contact lens overwear syndrome).
Diffuse punctate
Widespread, fine punctate staining over the whole cornea suggests toxic keratopathy, viral keratoconjunctivitis, or severe dry eye.
Central or paracentral
Central staining suggests contact lens complications, recurrent erosions, or early neurotrophic keratitis.
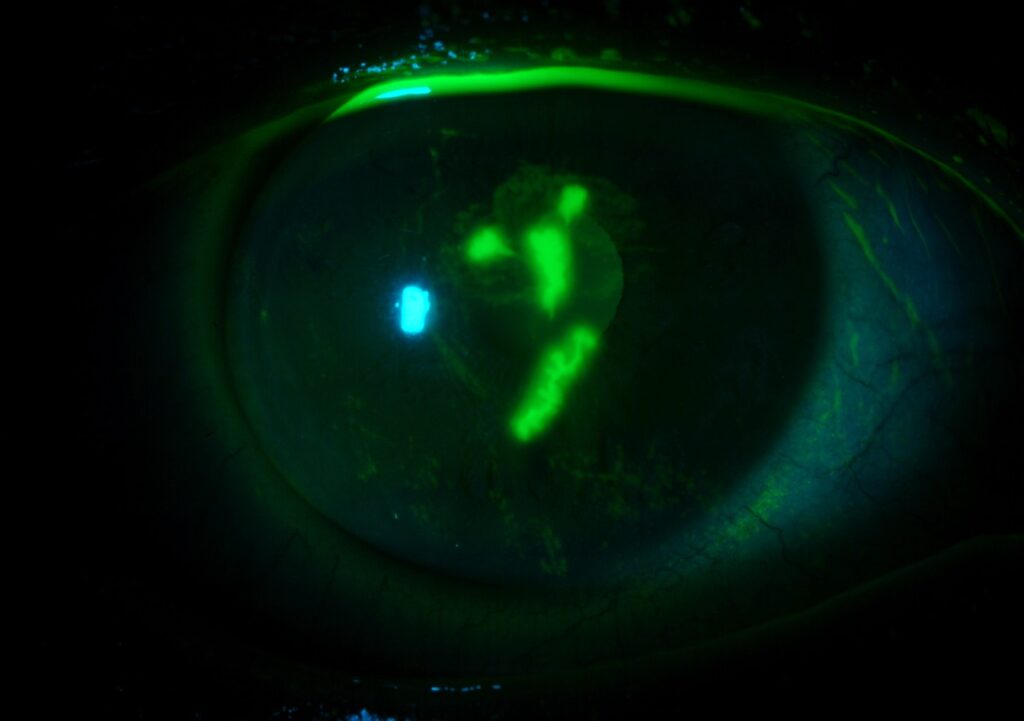
Dendritic and geographic
Branching, linear lesions with terminal bulbs are seen in herpes simplex epithelial keratitis, and they are different from the pseudodendrites of other conditions.
Geographic ulcers occur in more extensive herpes disease.
Whorl-like patterns suggest limbal stem cell deficiency or drug toxicity.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this sitePractical tips
- Instill the minimum amount of dye, and wait one to two minutes before looking for better visualization.
- Use a strip with a drop of saline, or a small drop of dye, to avoid dilution.
- Take photographs for follow-up.
- Remember that fluorescein can stain a damaged conjunctiva and that lissamine green requires a different filter or white light.
- Avoid wearing contact lenses after staining, as soft lenses can absorb the dye.
Why it matters
A well-read staining pattern shortens the path to diagnosis and prevents unnecessary treatment.
It can also guide the choice of management: lubrication, lid treatment, lens refit, topical antivirals, or surgery.
Technique and timing
Use a moistened fluorescein strip and ask the patient to blink several times to spread the dye. Examine after one minute, using the cobalt blue filter, and again at three to five minutes if needed. Lissamine green is better for the conjunctiva and the lid margin, and it can be examined in white light as well. Staining before applanation tonometry, or in a dry eye, should be done with a small amount of dye to avoid false results.
Grading
Count the dots, record the area, and use a standard scheme such as Oxford, so that follow-up visits are comparable. Photographs are helpful, particularly for patients with chronic ocular surface disease. A record of the pattern and the grade helps to judge whether treatment is working, which is often more informative than the symptoms.
Common mistakes
- Staining after the patient has rubbed the eye, which causes artifactual dots
- Using too much dye, which hides fine staining
- Confusing a tear film break with a defect
- Missing superior staining because the lid was not lifted
- Not recording the pattern, so that change cannot be judged later
Putting the pattern together with other findings
A pattern is a clue, and not a diagnosis. Combine it with the history, the lid examination, the tear break-up time, and the presence of discharge or papillae. For example, inferior staining with lagophthalmos suggests exposure, while the same staining with lid margin disease suggests blepharitis. Superior staining with large papillae suggests vernal disease or a contact lens problem. Think of the dye as a map that tells you where to look next, and a simple drawing in the notes increases the value of the test.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Bron AJ, Evans VE, Smith JA. Grading of corneal and conjunctival staining in the context of other dry eye tests. Cornea. 2003;22:640-650.
- Wolffsohn JS, Arita R, Chalmers R, et al. TFOS DEWS II diagnostic methodology report. Ocul Surf. 2017;15:539-574.
- Lemp MA. Report of the National Eye Institute/Industry workshop on clinical trials in dry eyes. CLAO J. 1995;21:221-232.
- Efron N. Contact Lens Complications. 4th ed. Edinburgh: Elsevier; 2018.
Test yourself
A few questions straight from this article.
-
Fluorescein staining of the cornea is best seen with which illumination?
Fluorescein marks areas where the epithelium has lost its barrier function or is missing, and it is best seen with a cobalt blue light and a yellow barrier filter. -
What does lissamine green stain on the ocular surface?
Lissamine green stains dead and degenerate cells and mucin-deficient areas, which makes it especially useful on the conjunctiva and lid margin, and it stings less than rose bengal. -
Vertical linear corneal scratches on fluorescein staining point to which cause?
A foreign body lodged under the upper lid drags across the cornea with each blink and creates vertical linear scratches. -
Which condition is suggested by staining confined to the upper cornea and conjunctiva?
Superior staining points to upper lid related disease such as superior limbic keratoconjunctivitis, vernal disease with giant papillae, floppy eyelid syndrome or contact lens reactions. -
Staining limited to the lower third of the cornea is characteristic of which problem?
Inferior third staining is common in exposure keratopathy and lagophthalmos, blepharitis and meibomian gland dysfunction, preserved drop toxicity and lid malposition. -
Staining in the horizontal band exposed between the lids is typical of what?
Staining across the interpalpebral band of cornea and conjunctiva exposed between the lids is typical of dry eye disease and of neurotrophic problems. -
Staining at the 3 and 9 o'clock positions on the cornea is characteristic of what?
Staining at the horizontal limbus is characteristic of rigid gas-permeable lens wear, where the lens edge disturbs the tear film. -
Branching linear epithelial lesions with terminal bulbs indicate which diagnosis?
Branching linear lesions with terminal bulbs are the dendrites of herpes simplex epithelial keratitis, and more extensive herpetic disease produces geographic ulcers. -
A whorl-like pattern of corneal staining suggests which problems?
Whorl-like staining patterns suggest limbal stem cell deficiency or drug toxicity, in contrast to the dendritic pattern of herpes simplex. -
Which examination step prevents superior corneal staining from being missed?
Superior staining is missed when the upper lid is not lifted, one of the common errors alongside using too much dye and staining an eye the patient has just rubbed.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.