Specular microscopy images the corneal endothelium and counts its cells.
It tells you how much reserve the cornea has before surgery or in disease.
Therefore, it supports decisions about cataract surgery, transplants and follow-up.
How Specular Microscopy Works
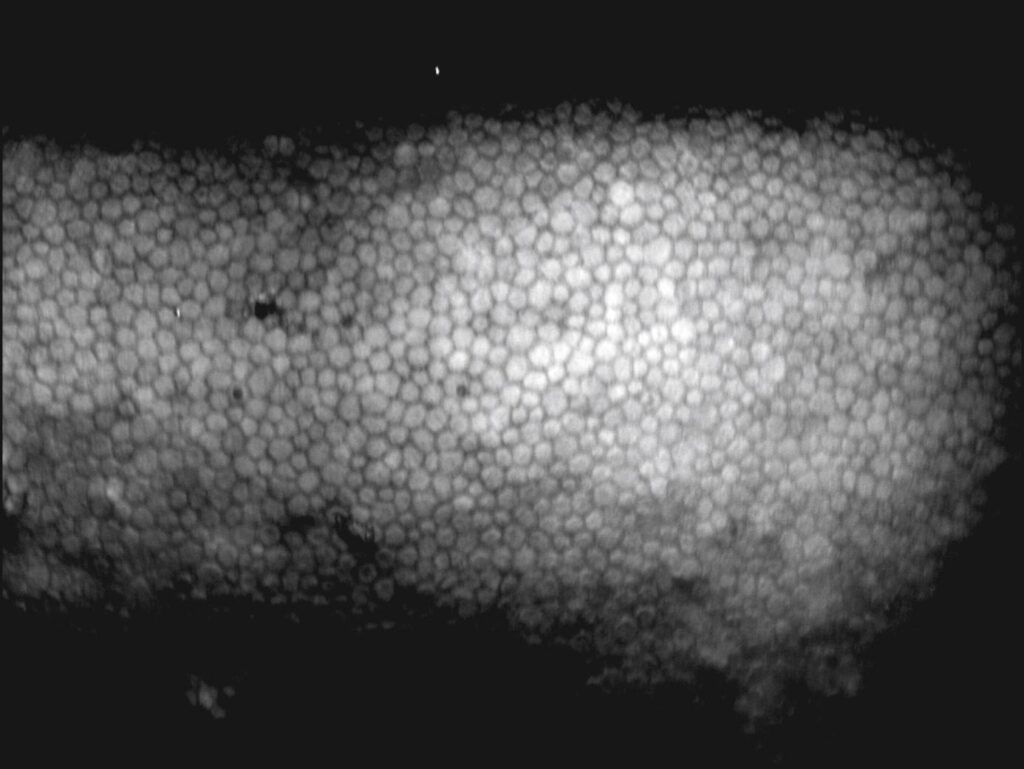
The instrument lights the cornea and captures the reflection at the boundary between the endothelium and the aqueous.
The cell borders appear dark against a bright mosaic.
Contact and non-contact devices exist, and both are quick and painless.
Also, software marks the cells and calculates the indices.
Indices From Specular Microscopy
Endothelial cell density counts cells per square millimeter.
The coefficient of variation measures variation in cell size, which is called polymegathism.
Hexagonality measures the share of six-sided cells and reflects pleomorphism.
Because these indices reflect stress, they matter beyond the number.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteNormal Values and Age
Young adults have about 3000 cells per square millimeter.
The density falls with age by roughly half a percent a year.
Also, healthy older adults often keep 2000 to 2500 cells and a clear cornea.
Therefore, interpret the count against the age and the clinical state.
Specular Microscopy in Fuchs Dystrophy and Guttae
Guttae appear as dark bodies that mask neighbouring cells.
The software may under-count or fail to count the area (see corneal guttae).
Also, cell borders become indistinct when the cornea swells.
Because a sample may be unrepresentative, repeat measurement and compare with pachymetry (see Fuchs endothelial dystrophy).
When to Order Specular Microscopy
Order it before cataract surgery in patients with guttae, prior intraocular surgery or a history of uveitis or glaucoma.
Eye banks use it to assess donor tissue.
Also, use it after trauma, in suspected iridocorneal endothelial syndrome and in contact lens wearers with long-term hypoxia (see iridocorneal endothelial syndrome).
Using the Result in Surgical Planning
No single threshold applies to all patients.
Many surgeons become cautious below about 1000 cells per square millimeter before phacoemulsification.
Also, a low count with high variability raises the risk of decompensation.
Therefore, discuss the risk of corneal edema and a future transplant before surgery.
Limits and Pitfalls
Poor images result from edema, scarring and poor fixation.
Small sampled areas and manual counting methods differ between machines.
Because devices vary, compare serial measurements on the same machine.
Alternatives and Adjuncts
Pachymetry shows function indirectly through corneal thickness (see corneal pachymetry).
Confocal microscopy and anterior segment optical coherence tomography help when specular images fail.
Also, slit-lamp findings remain essential for the overall assessment.
Endothelial Cell Loss After Surgery
Cataract surgery causes a loss of endothelial cells that varies with the technique and the nucleus density.
Also, intraocular lens position and complications add to the loss.
Therefore, serial counts show the real effect of surgery in a given eye.
Cell Density in Disease
Fuchs dystrophy, posterior polymorphous dystrophy and iridocorneal endothelial syndrome lower the count.
Also, chronic uveitis and glaucoma surgery can reduce it.
Because contact lens hypoxia changes cell shape, hexagonality may fall before the count does.
Eye Bank Use
Eye banks screen donor corneas with specular microscopy.
Also, many banks require a minimum count for transplantation.
Therefore, results guide the choice of tissue for each recipient.
Reading the Image
Look for sharp borders, a clear mosaic and few dark spots.
Also, avoid images with shadows or folds, and reject poorly focused frames.
Reporting Specular Microscopy Results
Record the count, the coefficient of variation and the hexagonality for each eye.
Also, note the device and the date, so results can be compared.
Specular Microscopy After Keratoplasty
After a graft, specular microscopy tracks the endothelial cell loss over time.
Also, a steep fall in density can warn of failure before edema appears (see corneal graft rejection).
Because rejection and chronic loss differ in cause, correlate the count with clinical findings.
Children and Special Groups
Cell density is higher in children and falls quickly in the first years of life.
Also, patients with congenital glaucoma and aniridia may show abnormal cells.
Therefore, use age-matched norms when you interpret the numbers.
Why Specular Microscopy Does Not Replace Clinical Judgment
A low count does not always cause edema, and a normal count does not exclude disease.
Slit-lamp signs, pachymetry and symptoms complete the picture.
Also, the same cornea can show different counts at different sites.
Therefore, use specular microscopy to support decisions and not to make them alone.
Then discuss the findings openly with the patient.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Bourne WM, Nelson LR, Hodge DO. Central corneal endothelial cell changes over a ten-year period. Invest Ophthalmol Vis Sci. 1997;38:779-782.
- McCarey BE, Edelhauser HF, Lynn MJ. Review of corneal endothelial specular microscopy for FDA clinical trials of refractive procedures, surgical devices, and new intraocular drugs and solutions. Cornea. 2008;27:1-16.
- Doughty MJ, Muller A, Zaman ML. Assessment of the reliability of human corneal endothelial cell-density estimates using a noncontact specular microscope. Cornea. 2000;19:148-158.
- Zoega GM, Fujisawa A, Sasaki H, et al. Prevalence and risk factors for cornea guttata in the Reykjavik Eye Study. Ophthalmology. 2006;113:565-569.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.