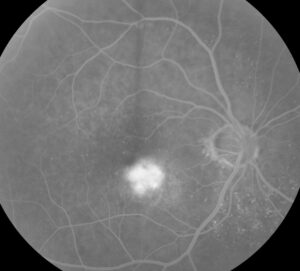
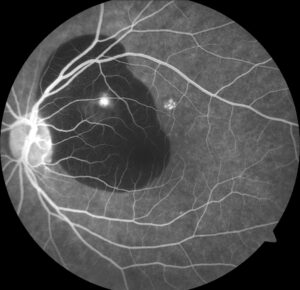
Thrombophilia testing in retinal vein occlusion has a low yield in most patients.
Most cases arise from age, hypertension and vascular disease.
Therefore, testing should be selective and based on risk.
Why Thrombophilia Testing Is Considered
Retinal vein occlusion is a venous thrombosis in the eye.
Clotting disorders cause thrombosis elsewhere in the body.
Also, young patients often have no obvious cause.
As a result, clinicians ask if an inherited disorder is present.
Common Causes First
Hypertension, diabetes, hyperlipidemia and glaucoma are the main risk factors (see central retinal vein occlusion).
Atherosclerosis damages the arteries that compress the veins.
Also, these causes explain most cases in older adults.
Therefore, check them before any specialized testing.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteWhat Thrombophilia Means
Thrombophilia is a tendency to form clots.
Inherited forms include factor V Leiden, prothrombin G20210A and deficiency of protein C, protein S or antithrombin.
Also, acquired forms include antiphospholipid syndrome and high homocysteine.
As a result, the list of tests is long.
Evidence for Thrombophilia Testing
Janssen and colleagues found that thrombophilic factors play a smaller role in retinal vein occlusion than in other venous clots.
Hyperhomocysteinemia and antiphospholipid antibodies show the clearest links.
Also, inherited defects show weaker or inconsistent associations.
Therefore, results in the eye differ from those in the leg.
Factor V Leiden and Prothrombin Mutation
Rehak and colleagues found activated protein C resistance more often in patients without general risk factors.
The finding was strongest in young patients.
Also, the absolute risk from a single mutation remains low.
As a result, a positive test seldom changes eye care.
Antiphospholipid Antibodies
These antibodies carry a higher risk of recurrence and arterial events.
They may change the choice of anticoagulation (see antiphospholipid syndrome).
Also, repeat positive tests are required for diagnosis.
Therefore, this is the most useful test in selected patients.
Homocysteine
High homocysteine levels raise the risk of vein occlusion.
Vitamin B treatment lowers the level.
Also, trials show no clear benefit on events.
As a result, treat when the level is high but do not expect a cure.
Who Needs Thrombophilia Testing
Consider testing in patients under 50 without hypertension, diabetes or other causes.
Test those with bilateral or recurrent occlusion.
Also, test those with a family history of thrombosis or a past clot elsewhere.
Therefore, a short list of triggers guides decisions.
Who Does Not Need Thrombophilia Testing
Older patients with hypertension and diabetes seldom need thrombophilia tests.
A single typical branch occlusion usually needs no extra tests.
Also, testing adds cost and anxiety.
As a result, avoid routine panels.
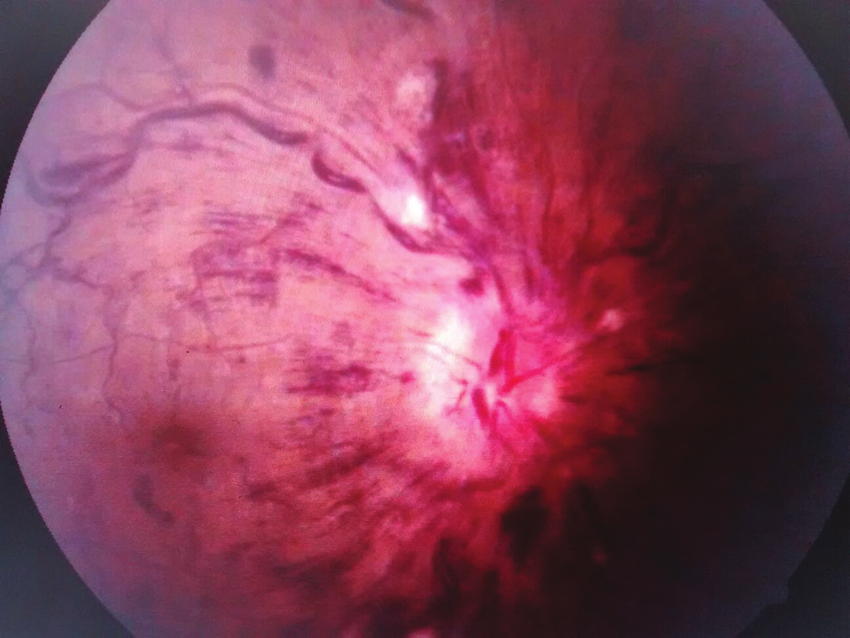
Suggested Panel for Thrombophilia Testing
Order antiphospholipid antibodies, homocysteine and factor V Leiden.
Add prothrombin mutation, and protein C and S, and antithrombin where indicated.
Also, add a blood count and a viscosity screen.
In addition, time the tests away from acute clots and anticoagulants.
Timing of Thrombophilia Testing
Acute thrombosis lowers protein C, protein S and antithrombin levels.
Warfarin lowers protein C and S levels.
Also, pregnancy and estrogen change levels.
Therefore, repeat abnormal results before acting.
Medical Referral
Refer positive results to a hematologist.
They weigh the need for anticoagulation.
Also, eye findings help them judge risk.
As a result, shared care improves decisions.
Role of Anticoagulation
Anticoagulation does not help most patients with retinal vein occlusion.
It carries risk of bleeding in the eye.
Also, it may be needed for other thrombotic events.
Therefore, base it on systemic indications.
Eye Treatment Does Not Depend on Results
Anti-VEGF drugs and laser treat edema and ischemia regardless of the cause.
The thrombophilia result informs systemic care only.
Also, follow the eye as in any vein occlusion.
In addition, treat modifiable risk factors.
Counseling Patients
Explain that most vein occlusions have common causes.
Describe why tests are done only in some cases.
Also, tell relatives that results may matter for them.
Therefore, communicate clearly and avoid fear.
Pitfalls to Avoid
- Do not order a full panel on every patient
- Never interpret protein C and S levels during acute clots or warfarin
- Do not start anticoagulation for eye disease alone
- Never forget to check blood pressure and glucose first
Cost and Value
A full panel costs a lot and seldom changes management.
Selective tests give better value.
Also, unneeded results cause anxiety.
Therefore, order only tests that may change care.
For the latest studies, see the PubMed results for thrombophilia testing.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Janssen MCH, den Heijer M, Cruysberg JRM, Wollersheim H, Bredie SJH. Retinal vein occlusion: a form of venous thrombosis or a complication of atherosclerosis? A meta-analysis of thrombophilic factors. Thromb Haemost. 2005;93:1021-1026.
- Rehak M, Rehak J, Müller M, et al. The prevalence of activated protein C (APC) resistance and factor V Leiden is significantly higher in patients with retinal vein occlusion without general risk factors. Thromb Haemost. 2008;99:925-929.
- Scott IU, Campochiaro PA, Newman NJ, Biousse V. Retinal vascular occlusions. Lancet. 2020;396:1927-1940.
- Rehak J, Rehak M. Branch retinal vein occlusion: pathogenesis, visual prognosis, and treatment modalities. Curr Eye Res. 2008;33:111-131.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.