CRISPR gene editing in the eye reached human patients before most other organs, because the retina is small, accessible, and partly isolated from the immune system.
The first in vivo trial treated a severe form of Leber congenital amaurosis by cutting out a harmful mutation in the cells of the retina.
It showed that the idea is feasible, and also how far the field has to go.
How CRISPR Gene Editing in the Eye Works
CRISPR uses a guide RNA and a Cas enzyme to cut DNA at a chosen place (see the references).
- The cell repairs the cut, which can also delete a sequence, disable a gene, or in other versions, change a single base
- Delivery to the retina uses viral vectors that carry the editing machinery
- The edit is permanent in the treated cells
This contrasts with standard gene therapy, which adds a working copy of a gene without changing the mutation (see gene therapy for inherited retinal disease).
CRISPR Gene Editing in the Eye: Why the Eye Is a Good Target
- The retina is accessible with a subretinal injection
- A small dose is enough, and spread to the rest of the body is limited
- The other eye provides a control
- Photoreceptors do not divide, so the edit lasts
- Clinicians can measure outcomes with imaging and functional tests
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteThe EDIT-101 Trial
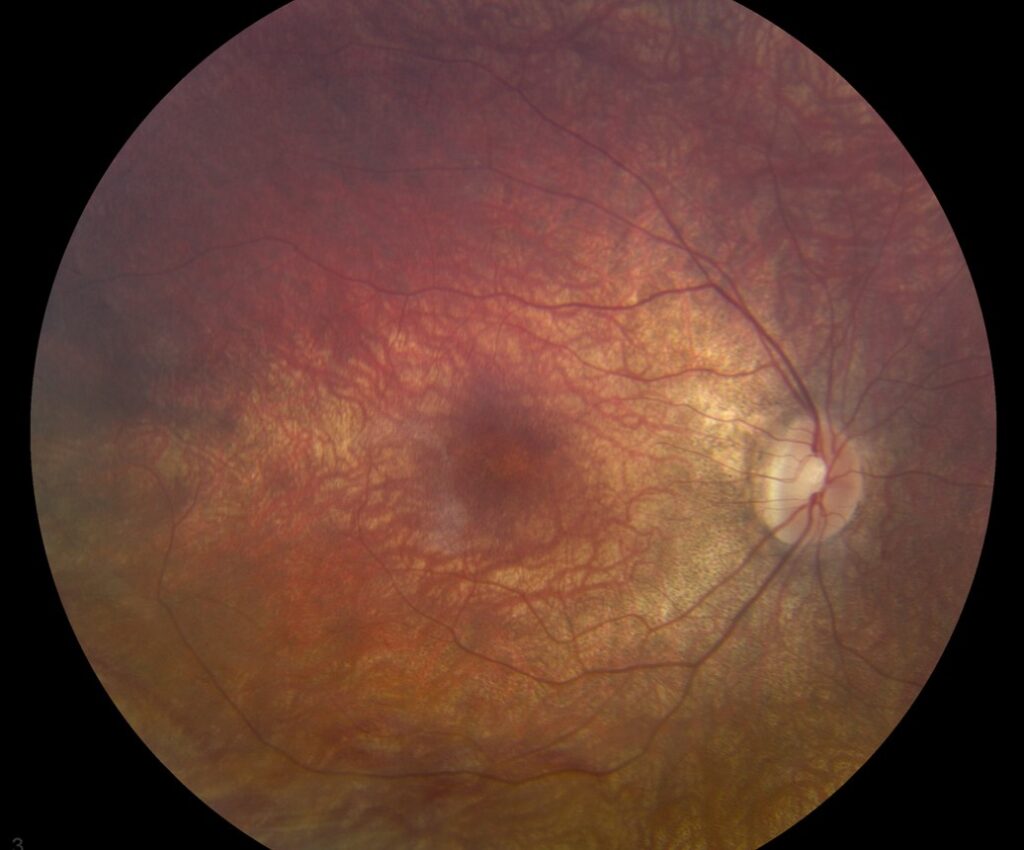
Leber congenital amaurosis type 10 is caused by a deep intronic mutation in CEP290, which creates a faulty splice site and a defective protein.
In addition, EDIT-101 used an AAV5 vector to carry a Cas9 enzyme and two guide RNAs, to remove the mutation and restore normal protein production (see the references).
- It was injected under the retina in patients with the mutation, in the BRILLIANCE trial
- The treatment was well tolerated, with no serious safety signals reported
- Some patients showed improvements in light sensitivity, mobility, or visual acuity, though the effects were modest and not uniform (see the references)
CRISPR Gene Editing in the Eye: Lessons From the Trial
- Editing in the human retina works, and it is safe at the dose tested
- Functional benefit was limited, perhaps because many photoreceptors were already lost or because editing was incomplete
- Enrollment of less advanced patients, and higher doses, could improve results
- Commercial decisions also affect programs, and development of this product was paused after the first study
Safety Concerns
- Off-target cuts at unintended sites in the DNA
- Immune responses to the Cas protein or vector
- Long-term effects of an enzyme that persists in cells
- Irreversibility of an edit
Newer approaches, such as base editing and prime editing, aim to change single letters without cutting both strands, which may be safer.
CRISPR Gene Editing in the Eye: Other Targets
- Dominant diseases, where a harmful gene must be silenced
- Mutations in large genes that do not fit in a standard vector
- Common mutations in diseases such as Stargardt disease and retinitis pigmentosa
- Regulation of angiogenic genes in AMD, as an experimental idea
Practical Message for Clinicians
Patients may ask about gene editing, and clinicians can explain that it is in early trials, that it is not yet an established treatment, and that genetic testing opens the door to trial eligibility.
CRISPR Gene Editing in the Eye: Counselling
Reassure patients that research is active, and encourage them to register with a center that follows inherited retinal diseases.
A Closer Look at the Challenge of Dose
Editing needs enough cells to be edited to change function, and delivery to all affected photoreceptors is difficult.
In the EDIT-101 trial, the treated area of the retina was limited by the size of the bleb, which may also partly explain the small clinical effect.
Higher doses and bigger blebs raise the risk of inflammation and thinning, so the balance is delicate.
Ethical and Regulatory Points
- Edits are permanent, so consent must explain risks and unknowns
- Long-term follow-up for many years is required by regulators
- Equal access should be planned, since costs of such therapies are very high
- Germline editing is not part of eye trials
Future Targets
Base editors could fix single-letter mutations, and prime editors could write small insertions, which would be good for common point mutations in genes such as ABCA4 and RHO.
Also, delivery by smaller vectors or by lipid nanoparticles to the retina is an active area of research.
Key Messages for Colleagues
Gene editing is an active area, and patients may find news that overstates progress.
Clinicians can also keep a balanced view, support interest in trials, and make sure that patients with inherited disease have genetic testing and counselling.
The first human trial showed safety and a signal of benefit.
The next steps are about dose, delivery, and patient selection.
For the latest studies, see the PubMed results for CRISPR gene editing in the eye.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Jinek M, Chylinski K, Fonfara I, Hauer M, Doudna JA, Charpentier E. A programmable dual-RNA-guided DNA endonuclease in adaptive bacterial immunity. Science. 2012;337:816-821.
- Maeder ML, Stefanidakis M, Wilson CJ, et al. Development of a gene-editing approach to restore vision loss in Leber congenital amaurosis type 10. Nat Med. 2019;25:229-233.
- Pierce EA, Aleman TS, Jayasundera KT, et al. Gene editing for CEP290-associated retinal degeneration. N Engl J Med. 2024;390:1972-1984.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.