
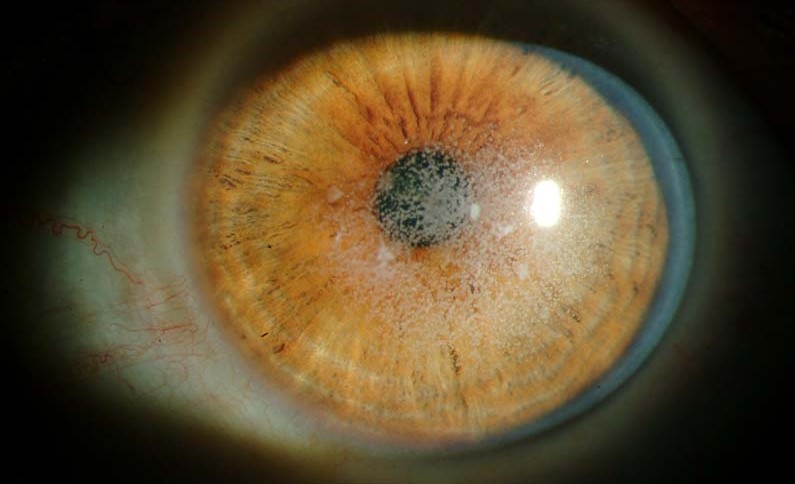
Avellino corneal dystrophy, also called granular corneal dystrophy type 2, combines the discrete stromal deposits of granular dystrophy with the branching, refractile lines of lattice dystrophy in the same cornea.
It is caused by a specific mutation in the same gene responsible for classic granular and lattice dystrophy, which is why its clinical appearance sits genuinely between the two rather than resembling either one cleanly.
Recognizing this hybrid pattern matters most acutely around refractive surgery, where Avellino dystrophy has a particular reputation for causing a severe, vision-threatening reaction if the diagnosis is missed beforehand.
The dystrophy is uncommon overall but disproportionately represented in certain populations, including individuals of Korean and Italian ancestry, reflecting founder-effect genetics in those groups.
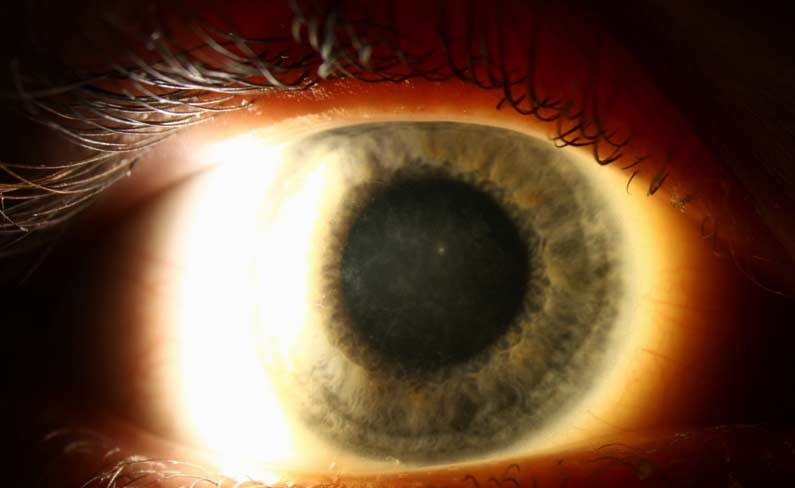
Genetics
Avellino dystrophy results from a specific mutation, most commonly Arg124His, in the TGFBI gene, the same gene that, with different mutations, causes classic granular dystrophy and lattice dystrophy type 1.
Inheritance is autosomal dominant with high penetrance, and the name derives from the Avellino region of Italy, where the founder mutation was first extensively characterized in an affected family.
Homozygous individuals, inheriting the mutation from both parents, tend to have a dramatically more severe phenotype than heterozygotes, underscoring how directly the genetic dose predicts clinical severity in this dystrophy.
Genetic counseling for affected families should reflect this gene-dose relationship, since two carrier parents, even both mildly affected themselves, have a meaningful chance of a child inheriting the more severe homozygous form.
Clinical Presentation
- Discrete, white, granular-appearing stromal opacities, similar in early appearance to classic granular dystrophy, typically noted in the first two decades of life
- Branching, refractile lattice-like lines appearing later, usually in the third or fourth decade, giving the combined pattern its hybrid appearance
- Progressive accumulation of both deposit types over time, with gradually worsening glare and, eventually, reduced visual acuity as the central cornea becomes involved
- Recurrent erosions are less prominent than in classic lattice dystrophy but can still occur, particularly once deposits reach the anterior stroma
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteThe Refractive Surgery Warning
Excimer laser refractive surgery, whether PRK or LASIK, has been reported to trigger a severe, sometimes dramatic worsening of Avellino dystrophy deposits in the treated cornea, occasionally within days of an otherwise unremarkable procedure.
The mechanism is thought to involve the surgical or laser-induced stromal wound-healing response accelerating deposition of the abnormal protein, essentially converting a slowly progressive condition into an acutely aggressive one localized to the treated area.
Because early, subtle Avellino deposits can be easy to overlook on a routine preoperative slit-lamp exam, especially in a young patient who has not yet developed the more obvious lattice-line component, a careful family history and a high index of suspicion for any atypical stromal haze matters before proceeding with refractive surgery.
Differential Diagnosis
Classic granular dystrophy shows only the discrete white deposits without the later lattice-line component, and it does not carry the same well-documented refractive surgery risk.
Lattice dystrophy type 1 shows the branching refractile lines without the granular component, and is also associated with systemic amyloidosis in some cases, unlike Avellino dystrophy.
The combined presence of both deposit patterns in the same cornea, especially with a positive family history, should specifically raise suspicion for Avellino dystrophy rather than either classic pattern alone.
Management
Genetic testing confirms the diagnosis definitively and is particularly valuable before any consideration of refractive surgery in a patient with an atypical or subtle stromal opacity pattern, or any family history of a corneal dystrophy.
Phototherapeutic keratectomy can be used to remove superficial deposits and improve vision, though, as with the other TGFBI-related dystrophies, recurrence in the treated area is expected over time.
Penetrating or lamellar keratoplasty is reserved for eyes with dense, vision-limiting central opacification, again with the expectation that recurrent deposits can eventually affect the graft as the underlying genetic process continues.
Screening family members of an affected patient, even asymptomatic ones, has real practical value given how directly a missed diagnosis can affect a future decision about refractive surgery in that relative.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Kim TI, Kim T, Kim SW, et al. Comparison of corneal deposits after LASIK and PRK in eyes with granular corneal dystrophy type II. Journal of Refractive Surgery.
- Weiss JS, Møller HU, Aldave AJ, et al. IC3D classification of corneal dystrophies — edition 2. Cornea.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea.
