
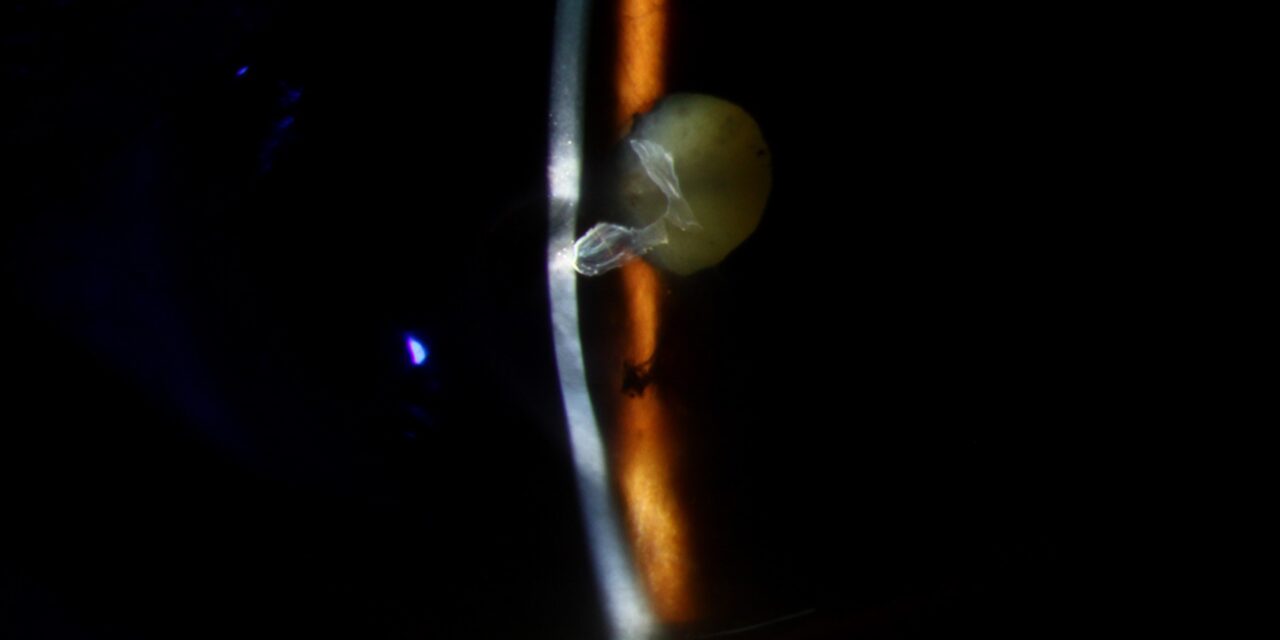
A descemetocele is a bulging protrusion of Descemet’s membrane through a region of the cornea that has lost all of its overlying stroma, leaving only the membrane and endothelium — held in place by intraocular pressure from behind — separating the anterior chamber from the outside world.

It represents one of the most urgent findings in all of cornea and external disease, because the tissue holding the eye closed at that point is a single, extremely thin layer with no stromal reinforcement, and any further insult can cause frank perforation.
How It Develops
A descemetocele forms as the end stage of progressive stromal thinning from an underlying corneal ulcer, whatever the cause: infectious keratitis (bacterial, fungal, or, less commonly, viral or parasitic), severe neurotrophic keratopathy, or a sterile immune-mediated melting process such as that seen in severe dry eye, vitamin A deficiency, or autoimmune peripheral ulcerative keratitis.
As stromal collagen is progressively destroyed by the underlying process, the tissue thins from its normal thickness down toward zero.
Once the entire stromal layer is gone at the thinnest point, only Descemet’s membrane remains, bulging forward under the eye’s internal pressure.
Because this endpoint can be reached through so many different underlying disease processes, the rate of progression varies considerably: an aggressive bacterial or fungal ulcer can produce a descemetocele within days, while a slower, chronic neurotrophic or autoimmune process may take weeks to reach the same critical point.
Clinical Findings
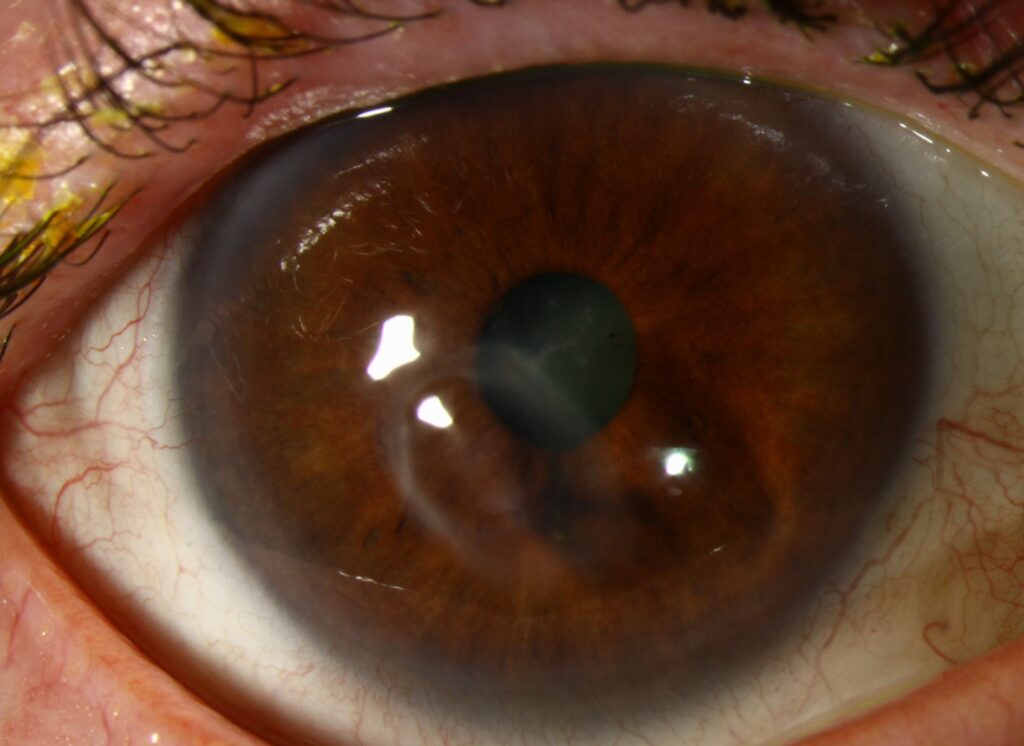
- A clear, thin, dome-shaped protrusion at the base of a corneal ulcer, distinct from the surrounding hazier, infiltrated stroma
- The classic “dark room” or slit-lamp appearance of a smooth, glistening, transparent bulge — Descemet’s membrane itself does not scar or infiltrate the way stroma does, so it looks strikingly different from the ulcerated tissue around it
- A positive Seidel test may or may not be present depending on whether there is already a microperforation; a negative Seidel test does not rule out an impending rupture
- Signs of the underlying cause — hypopyon and stromal infiltrate in infectious keratitis, reduced corneal sensation in neurotrophic disease, or other markers of autoimmune disease in sterile melting
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteWhy This Is an Emergency
A descemetocele can rupture with minimal additional stress — a sneeze, eye rubbing, or even normal fluctuations in intraocular pressure — resulting in acute perforation, sudden collapse of the anterior chamber, and a real risk of intraocular infection, iris prolapse, and permanent vision loss.
Unlike a simple corneal ulcer, which generally allows some time for treatment to take effect, a descemetocele requires urgent intervention specifically aimed at preventing perforation, in parallel with treating whatever underlying process caused the thinning.
Patients with a known descemetocele should be specifically counseled about protective measures — avoiding eye rubbing, using a protective shield, particularly during sleep — since these simple precautions meaningfully reduce the risk of an avoidable mechanical trigger for perforation while definitive treatment is being arranged, and should be told explicitly to seek immediate care if they notice sudden pain, a gush of fluid, or abrupt vision change.
Differential Diagnosis
- Deep stromal ulcer without descemetocele — still has some remaining stromal tissue, generally less immediately urgent though still requires aggressive treatment
- Corneal perforation — the descemetocele has already ruptured; a flat or shallow anterior chamber and positive Seidel test confirm this more advanced, even more urgent stage
- Keratoconus with acute hydrops — a break in Descemet’s membrane in an already ectatic cornea, a different mechanism producing acute edema rather than an impending perforation
Management
Treatment addresses two goals simultaneously: controlling the underlying cause of stromal loss (targeted antimicrobial therapy for infectious keratitis, aggressive lubrication and surface protection for neurotrophic or exposure-related thinning, immunosuppression for autoimmune melting) and mechanically reinforcing or protecting the thinned area to prevent perforation.
A bandage contact lens or tissue adhesive (cyanoacrylate glue) can temporarily stabilize a small descemetocele while the underlying process is brought under control, buying time without committing to a larger surgical procedure.
More extensive or progressive descemetoceles, or those that fail to stabilize with medical management and adhesive, require surgical intervention: a corneal patch graft or emergency penetrating keratoplasty to restore structural integrity, if perforation has already occurred or appears imminent despite maximal medical therapy.
The choice between these options depends on the size of the defect, the status of the surrounding cornea, and how urgently the eye needs to be stabilized.
Amniotic membrane transplantation is sometimes used as an intermediate option, providing a biologic scaffold that can support re-epithelialization and offer some structural support in cases where a bandage lens or glue alone is insufficient but a full surgical graft is not yet warranted.
Prognosis
Outcomes depend heavily on how quickly the underlying process is controlled and the descemetocele is stabilized, along with the extent and location of the thinning.
A small, peripheral descemetocele carries a far better prognosis than an extensive, central one.
Even with successful stabilization, significant corneal scarring in the visual axis is common in eyes that have progressed this far.
Many patients ultimately require optical or even penetrating keratoplasty later to restore vision once the acute emergency has resolved, and setting expectations about this likely second, elective stage of treatment early — during the acute, emergency phase — helps patients understand that stabilizing the eye and restoring vision are often two separate steps rather than a single procedure.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wilhelmus KR. Descemetocele. In: Cornea.
- Yin J, Jurkunas U. Bowman layer transplantation in the United States. Cornea.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea.
- Bagheri N, Wajda B, eds. The Wills Eye Manual.
