Myopic crescent is a pale, sharply defined zone at the optic disc edge of an axially long eye.
It usually lies temporally and often causes no symptoms.
However, myopic eyes can also develop glaucoma, so this sign needs careful interpretation.
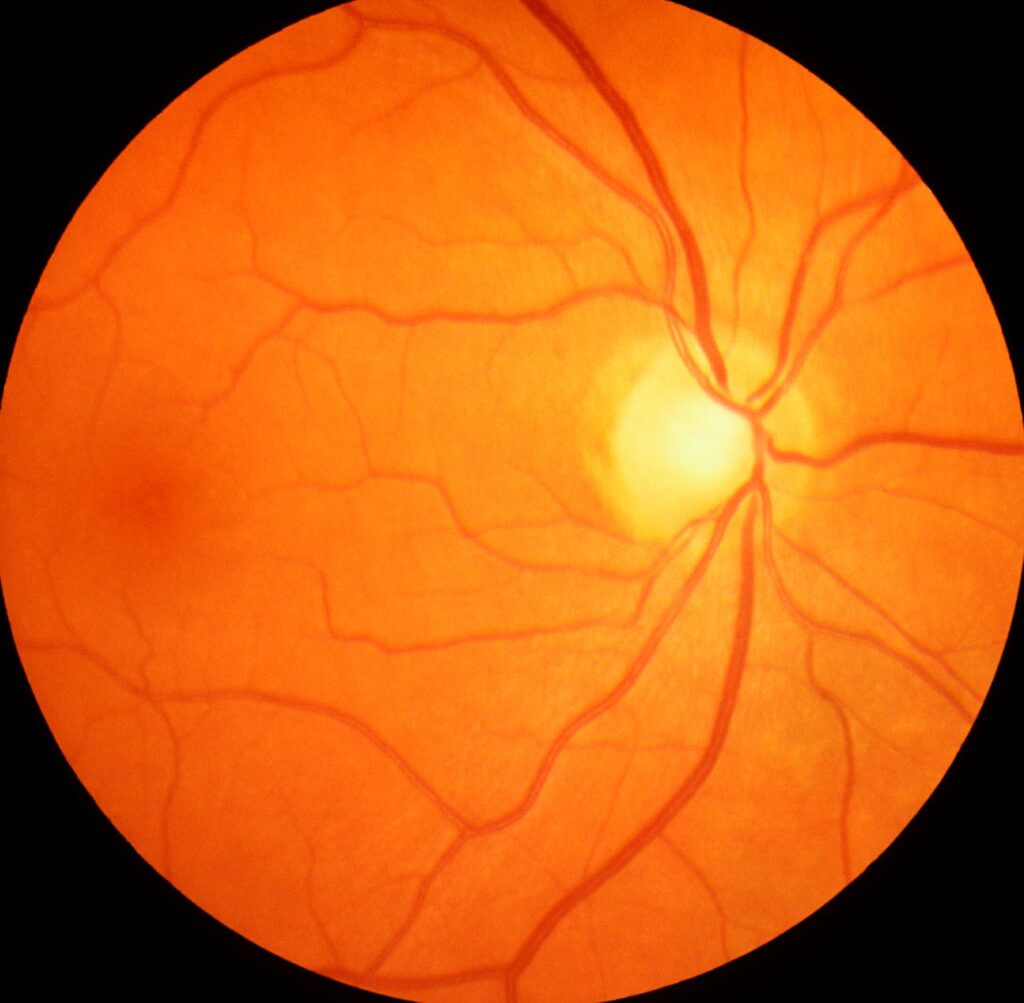
What a Myopic Crescent Looks Like
The examiner sees a white or yellow-white band beside the temporal disc margin.
Its outer border often looks crisp, and pigment may outline it.
In addition, large choroidal vessels may cross the zone when some choroid persists.
How Axial Elongation Forms a Myopic Crescent
As the globe lengthens, the posterior coats do not shift uniformly.
Bruch’s membrane opening appears to move, usually toward the macula.
As a result, the temporal disc edge can lose its Bruch’s membrane, RPE and choriocapillaris cover.
For example, Kim and colleagues documented progressive disc tilt and temporal atrophy in children developing myopia.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteBeta and Gamma Zones in Myopic Crescent
Histologic work divides parapapillary atrophy into zones with different associations.
Beta zone has Bruch’s membrane but lacks RPE, and it has been linked with glaucoma.
Gamma zone lacks Bruch’s membrane, and it correlates with axial elongation.
Finally, delta zone marks a thinned peripapillary scleral flange in highly myopic eyes.
Disc Tilt in Myopic Crescent
Elongation commonly rotates the disc around its vertical axis.
Therefore, the temporal rim may look flat while the nasal edge appears elevated.
Congenital tilt has a different pattern (see tilted disc syndrome).
Myopic Crescent on OCT
Radial scans through the disc edge show where Bruch’s membrane ends.
If it stops short of the disc margin, the scan supports gamma zone.
However, very long eyes can produce segmentation errors.
Myopic Crescent Versus Glaucomatous Atrophy
Size and shape alone cannot settle this question.
Jonas and colleagues found larger, more frequent beta zones in glaucoma, yet normal eyes also show them.
Therefore, treat parapapillary atrophy as supporting evidence and never as a diagnosis.
Next, look for rim loss, nerve fiber defects and a matching field defect.
Reading the Neuroretinal Rim
Glaucoma damages the rim, while simple myopic stretching should leave no focal notch.
Disc hemorrhage also favors active glaucomatous damage.
In addition, Bruch’s membrane opening minimum rim width offers an anatomically based measure.
RNFL and Visual Field Traps
Myopia can shift the peripapillary nerve fiber peaks temporally.
As a result, a normative map may flag healthy tissue as abnormal.
Meanwhile, staphyloma-related field defects may not respect glaucoma patterns.
Repeatable change across serial tests therefore carries more weight than one printout.
When Both Conditions Coexist
Myopia is a recognized risk factor for open-angle glaucoma.
Therefore, a benign-looking crescent should never close the glaucoma evaluation.
Measure pressure, perform gonioscopy and review family history.
Other Disc Edge Lookalikes
An inferior crescent suggests tilted disc syndrome, especially with superotemporal field loss.
Chorioretinal scars usually have irregular margins and may lie away from the disc.
Then consider the whole fundus, including tessellation, lacquer cracks and staphyloma.
Assessing a Myopic Crescent in Clinic
A structured examination reduces errors and supports later comparison.
- Record refraction and axial length
- Check pressure and perform gonioscopy
- Inspect rim, nerve fiber layer and disc hemorrhage
- Obtain disc photographs and OCT
- Perform perimetry with the correct lens
- Examine the macula and posterior pole
Does a Myopic Crescent Threaten Vision?
The crescent itself usually causes no central visual loss.
However, a large crescent can accompany marked axial elongation and posterior pole disease.
Therefore, check the macula, using a structured system when pathologic myopia is suspected.
A coexisting posterior staphyloma also changes imaging and follow-up.
Management of Myopic Crescent
No treatment reverses the crescent or restores the missing tissue.
Management therefore targets refractive correction, associated disease and accurate documentation.
Treat glaucoma when structure, function and risk support the diagnosis.
In children, myopia control aims to slow axial growth.
However, evidence that it prevents crescent formation remains limited, so avoid that promise.
Follow-Up and Counseling for Myopic Crescent
Base the interval on glaucoma risk and myopic complications.
Then compare new photographs and OCT scans with the baseline set.
Rim thinning or progressive field loss should prompt a glaucoma reassessment.
Also reassure patients that the sign alone does not establish glaucoma.
Finally, ask them to report new distortion, flashes, floaters or a field shadow promptly.
Pitfalls to Avoid
- Do not label every temporal crescent as harmless
- Do not diagnose glaucoma from crescent size alone
- Avoid relying on OCT color maps in long eyes
- Never skip gonioscopy because the disc looks myopic
- Compare serial images before calling progression
For the latest studies, see the PubMed results for myopic crescent.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Jonas JB, Jonas SB, Jonas RA, et al. Parapapillary atrophy: histological gamma zone and delta zone. PLoS One. 2012;7:e47237.
- Dai Y, Jonas JB, Huang H, et al. Microstructure of parapapillary atrophy: beta zone and gamma zone. Invest Ophthalmol Vis Sci. 2013;54:2013-2018.
- Kim TW, Kim M, Weinreb RN, et al. Optic disc change with incipient myopia of childhood. Ophthalmology. 2012;119:21-26.
- Jonas JB, Nguyen XN, Gusek GC, et al. Parapapillary chorioretinal atrophy in normal and glaucoma eyes. I. Morphometric data. Invest Ophthalmol Vis Sci. 1989;30:908-918.
- Chauhan BC, O’Leary N, AlMobarak FA, et al. Enhanced detection of open-angle glaucoma with an anatomically accurate optical coherence tomography-derived neuroretinal rim parameter. Ophthalmology. 2013;120:535-543.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.