Bacterial keratitis is an ophthalmic emergency that can scar the cornea within days.
Contact lens wear is the main risk factor in developed countries.
Prompt scraping and broad-spectrum drops give the best results.
Risk Factors for Bacterial Keratitis
Contact lenses, trauma and ocular surface disease all raise risk.
Overnight lens wear is especially dangerous.
Previous corneal surgery and steroid use also contribute.
Therefore, take a full lens history (see contact lens overwear syndrome).
Common Organisms
Pseudomonas aeruginosa is common in lens wearers.
Staphylococcus and Streptococcus species cause many other ulcers.
Resistance patterns vary by region.
So know your local data.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Features of Bacterial Keratitis
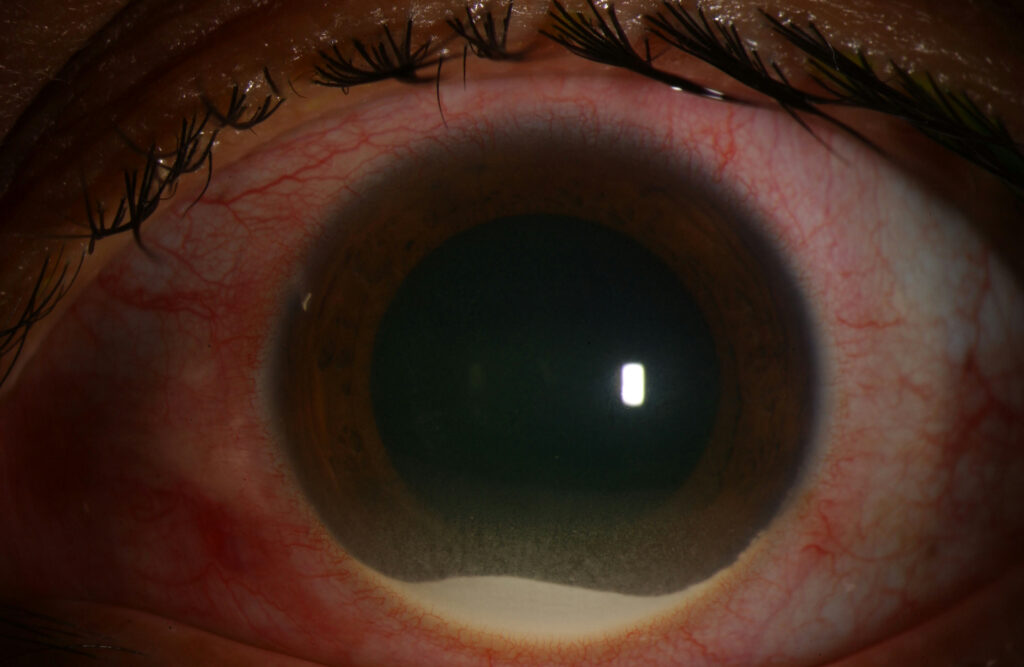
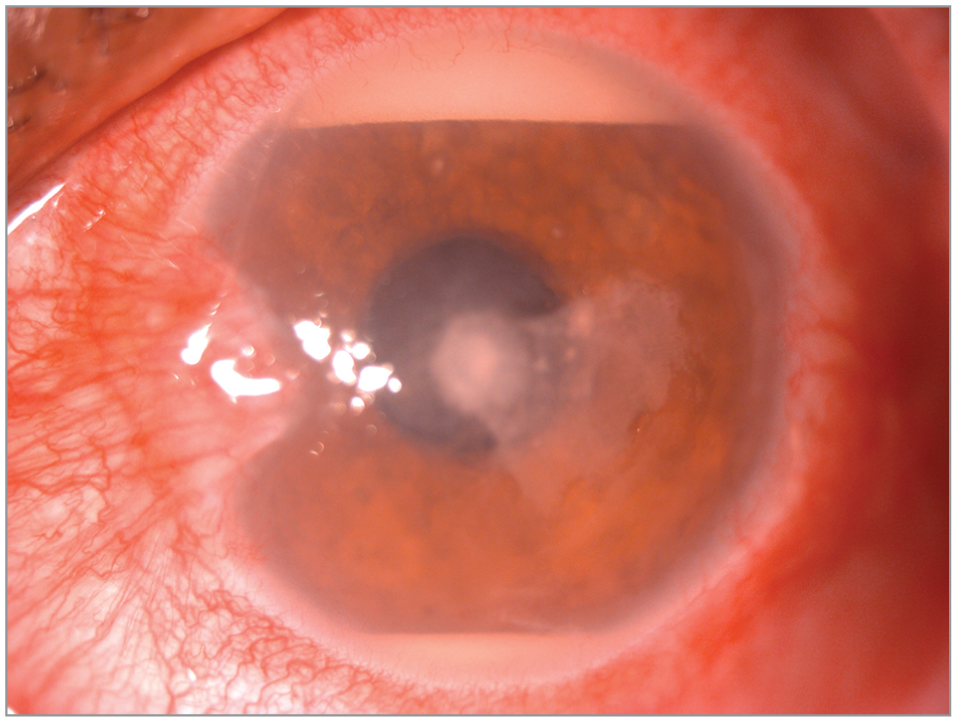
A focal white infiltrate with an overlying epithelial defect is typical.
Pain, redness and discharge are common.
A hypopyon signals severe inflammation.
However, small peripheral infiltrates may be sterile.
When to Scrape
Scrape ulcers that are large, central or deep.
Also scrape if there is hypopyon or poor response.
Small peripheral lesions in lens wearers may be treated empirically.
Therefore, use clinical judgment.
Laboratory Work-Up for Bacterial Keratitis
Plate material on blood and chocolate agar.
Use Gram stain for early guidance.
Culture contact lenses and cases when possible.
Also record the results for later review.
Bacterial Keratitis and Empiric Antibiotics
Monotherapy with a fluoroquinolone is standard for most ulcers.
Moxifloxacin and levofloxacin have broad coverage.
Severe ulcers need fortified antibiotics.
So match the choice to severity.
Dosing Schedule in Bacterial Keratitis
Give a loading dose every five minutes for the first half hour in severe cases.
Then continue hourly day and night for two days.
Taper according to response.
Also warn patients about sleep interruption.
Fortified Antibiotics
Combine fortified cefazolin and tobramycin or vancomycin when severe.
These drops need pharmacy preparation.
They can be toxic to the surface.
Therefore, use them for selected cases.
Role of Steroids
The SCUT trial found no overall benefit from adjunctive steroids.
Patients with severe central ulcers may benefit from earlier use.
Do not use steroids until the organism is controlled (see SCUT).
So individualize the decision.
Adjunctive Care
Use cycloplegic drops for pain.
Protect the eye with a shield but avoid patching.
Treat raised pressure when it develops.
Also stop contact lens wear.
Follow-Up
Review daily until the infiltrate shrinks.
Look for epithelial healing and less pain.
Consider cultures if the ulcer does not improve.
Therefore, change therapy when the course is poor.
Complications of Bacterial Keratitis
Perforation, scarring and endophthalmitis are possible.
Neovascularization can threaten graft success later.
Early treatment reduces these risks.
Also plan rehabilitation for scars.
Prevention of Bacterial Keratitis
Good lens hygiene prevents many cases.
Avoid sleeping in lenses.
Educate patients at every visit.
So prevention is the best treatment.
Pitfalls to Avoid
- Do not start steroids before culture results
- Never patch an infected cornea
- Avoid tapering too early
- Do not forget to culture lens cases
Bacterial Keratitis in Children
Children with bacterial keratitis often have a history of trauma.
Because they cannot cooperate easily, examination may need sedation.
Fluoroquinolone drops are usually first-line.
Therefore, treat promptly and monitor closely.
Bacterial Keratitis and Resistance
Resistance to fluoroquinolones has increased in some regions.
If an ulcer fails to improve, culture results guide changes.
Because local data matter, review your hospital antibiogram.
Then update your first-line choice when needed.
Bacterial Keratitis in Corneal Grafts
Graft infections spread fast and threaten the graft.
When a graft ulcer appears, culture and treat at once.
Because steroid drops are often in use, check the regimen.
Therefore, refer to the corneal surgeon quickly.
Bacterial Keratitis and Perforation
Thin, melting ulcers may perforate.
If the cornea is thin, avoid pressure on the globe.
Then arrange urgent surgical repair.
In addition, use a shield to protect the eye.
Bacterial Keratitis and Cross-Linking
Cross-linking has been tried as an adjunct for infection.
Results are mixed and the evidence is limited.
Therefore, it is not standard care.
However, trials are ongoing.
Bacterial Keratitis Prognosis
Vision depends on the size and site of the scar.
Central scars limit vision more than peripheral ones.
Because early care helps, tell patients to seek help fast.
Then plan rehabilitation, including contact lenses or transplant.
Bacterial Keratitis: Practical Summary
When a patient presents with a painful white infiltrate, scrape the ulcer if it is large or central.
Then start a broad-spectrum drop without delay.
Because the course can change, review the eye every day at first.
Finally, reinforce lens hygiene before wear resumes.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Ung L, Bispo PJM, Shanbhag SS, Gilmore MS, Chodosh J. The persistent dilemma of microbial keratitis: global burden, diagnosis, and antimicrobial resistance. Surv Ophthalmol. 2019;64:255-271.
- Austin A, Lietman T, Rose-Nussbaumer J. Update on the management of infectious keratitis. Ophthalmology. 2017;124:1678-1689.
- Srinivasan M, Mascarenhas J, Rajaraman R, et al. Corticosteroids for bacterial keratitis: the Steroids for Corneal Ulcers Trial (SCUT). Arch Ophthalmol. 2012;130:143-150.
- Stapleton F, Carnt N. Contact lens-related microbial keratitis. Eye. 2012;26:185-193.
Test yourself
A few questions straight from this article.
-
What is the main risk factor for bacterial keratitis in developed countries?
Contact lens wear is the main risk factor in developed countries, and overnight lens wear is especially dangerous. -
Which organism is common in bacterial keratitis among contact lens wearers?
Pseudomonas aeruginosa is common in lens wearers, while Staphylococcus and Streptococcus species cause many other ulcers. -
What is the typical slit-lamp appearance of bacterial keratitis?
A focal white infiltrate with an overlying epithelial defect is typical, with pain, redness and discharge; a hypopyon signals severe inflammation. -
Which bacterial keratitis ulcer should be scraped for microbiology before treatment?
Large, central or deep ulcers are scraped, as are those with hypopyon or poor response; small peripheral lesions in lens wearers may be treated empirically. -
Corneal scrapings in bacterial keratitis are plated on which culture media?
Material is plated on blood and chocolate agar, with a Gram stain giving early guidance; lenses and cases are cultured when possible. -
What is the standard empiric antibiotic regimen for most bacterial corneal ulcers?
Fluoroquinolone monotherapy is standard for most ulcers, with moxifloxacin and levofloxacin giving broad coverage; severe ulcers need fortified antibiotics. -
How are drops given at the start of treatment for severe bacterial keratitis?
Severe cases get a loading dose every five minutes for the first half hour, then hourly drops day and night for two days before tapering by response. -
What did the SCUT trial find about adjunctive corticosteroids in bacterial keratitis?
SCUT found no overall benefit from adjunctive steroids, although patients with severe central ulcers may benefit, so the decision is individualised. -
How should an eye with bacterial keratitis be protected?
The eye is protected with a shield but never patched, alongside cycloplegic drops for pain and stopping contact lens wear. -
What chiefly determines final visual outcome after bacterial keratitis?
Vision depends on the size and site of the scar, and central scars limit vision more than peripheral ones.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.