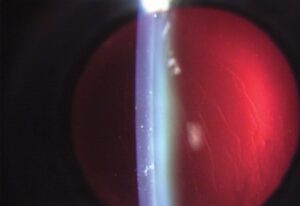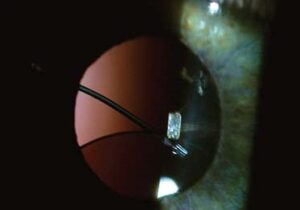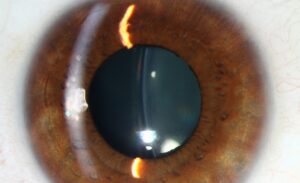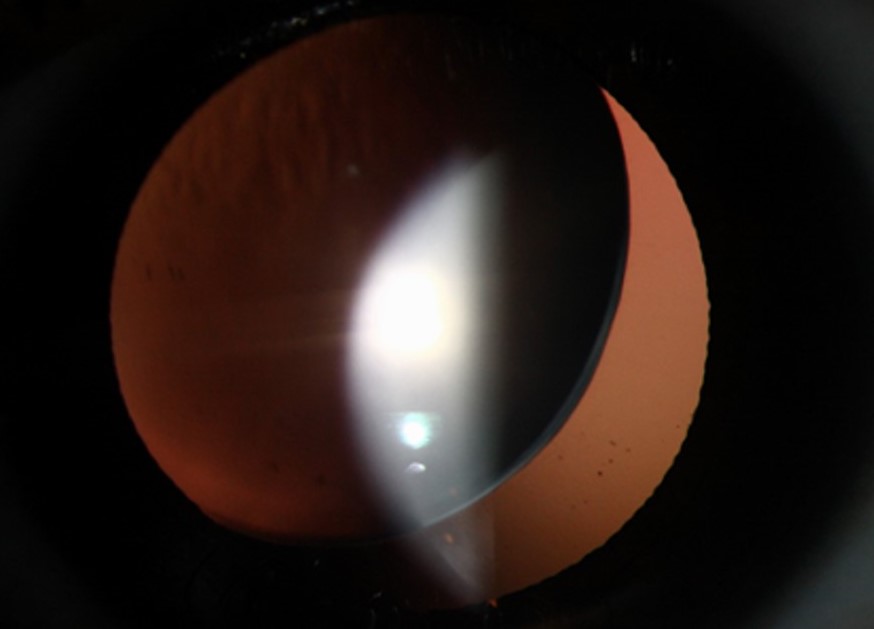
Phacodonesis is a tremor of the crystalline lens that appears on eye movement.
It is also a sign of weak or damaged zonules.
Surgeons often find it before cataract surgery, and it signals a higher risk of complications such as zonular dialysis and vitreous loss.
Also, recognizing it ahead of time allows the surgeon to plan for it.
What Is Phacodonesis?
The lens is suspended by thousands of fine zonular fibers from the ciliary body, which hold it in position and transmit the force of accommodation.
When the fibers stretch, break, or fail, the lens loses its stable attachment and trembles with each saccade.
Examiners see the movement at the slit lamp as a wobble of the lens, and in a similar way the iris may tremble if the lens is absent or displaced, which they call iridodonesis.
The tremor may also be mild and localized, or large, with obvious displacement of the lens.
Causes of Phacodonesis
- Trauma, blunt or penetrating, which can break zonules over a segment
- Pseudoexfoliation syndrome, a leading cause in older patients (see pseudoexfoliation syndrome)
- Marfan syndrome, homocystinuria, Weill-Marchesani syndrome, and other genetic disorders (see ectopia lentis in Marfan syndrome and Weill-Marchesani syndrome)
- Hypermature cataract, where the zonules have degenerated (see Morgagnian cataract)
- High myopia and buphthalmos, with stretching of the zonules
- Chronic uveitis and previous intraocular surgery, including vitrectomy
- Aniridia and other developmental conditions
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteExamination in Phacodonesis
Ask the patient to look from side to side while you observe the lens at the slit lamp with a narrow beam.
Also, look for a tremor of the anterior lens surface, a shifted lens, or vitreous in the anterior chamber.
Dilate the pupil and look at the lens edge, the zonular fibers if visible, and any phakodonesis that is more apparent in a sitting versus a supine position.
In addition, check the anterior chamber depth, which may be uneven in a subluxated lens, and the iris for iridodonesis.
Also, gonioscopy may show zonular fibers or pigment, and ultrasound biomicroscopy can show the zonules and the ciliary body.
Pseudoexfoliative material on the lens capsule and the pupil margin suggests the cause.
Importance for Cataract Surgery
Zonular weakness raises the risk of capsular rupture, zonular dialysis, nucleus loss, and vitreous loss.
- Plan a larger and more controlled capsulorhexis, with viscoelastic to stabilize the lens (see capsulorhexis radial tear)
- Use capsule hooks or iris retractors to support the rhexis margin during phacoemulsification
- Place a capsular tension ring early, or a segment, when the zonular defect is limited (see capsular tension ring indications)
- Reduce the stress on the bag by minimizing hydrodissection force and nuclear rotation
- Prepare for vitrectomy, and have the equipment ready (see vitreous loss in cataract surgery)
- Decide in advance on the lens plan, with options in the bag, in the sulcus, or sutured
A committee of the American Society of Cataract and Refractive Surgery has published recommendations on management of the subluxated lens.
Counselling
Warn the patient that the surgery is more complex than usual, that the surgeon may need to place the lens in an unusual position, and that vision may take longer to recover.
Inform patients with a hereditary condition about systemic issues and about the risk to relatives.
Refer to an experienced surgeon when the lens is markedly displaced.
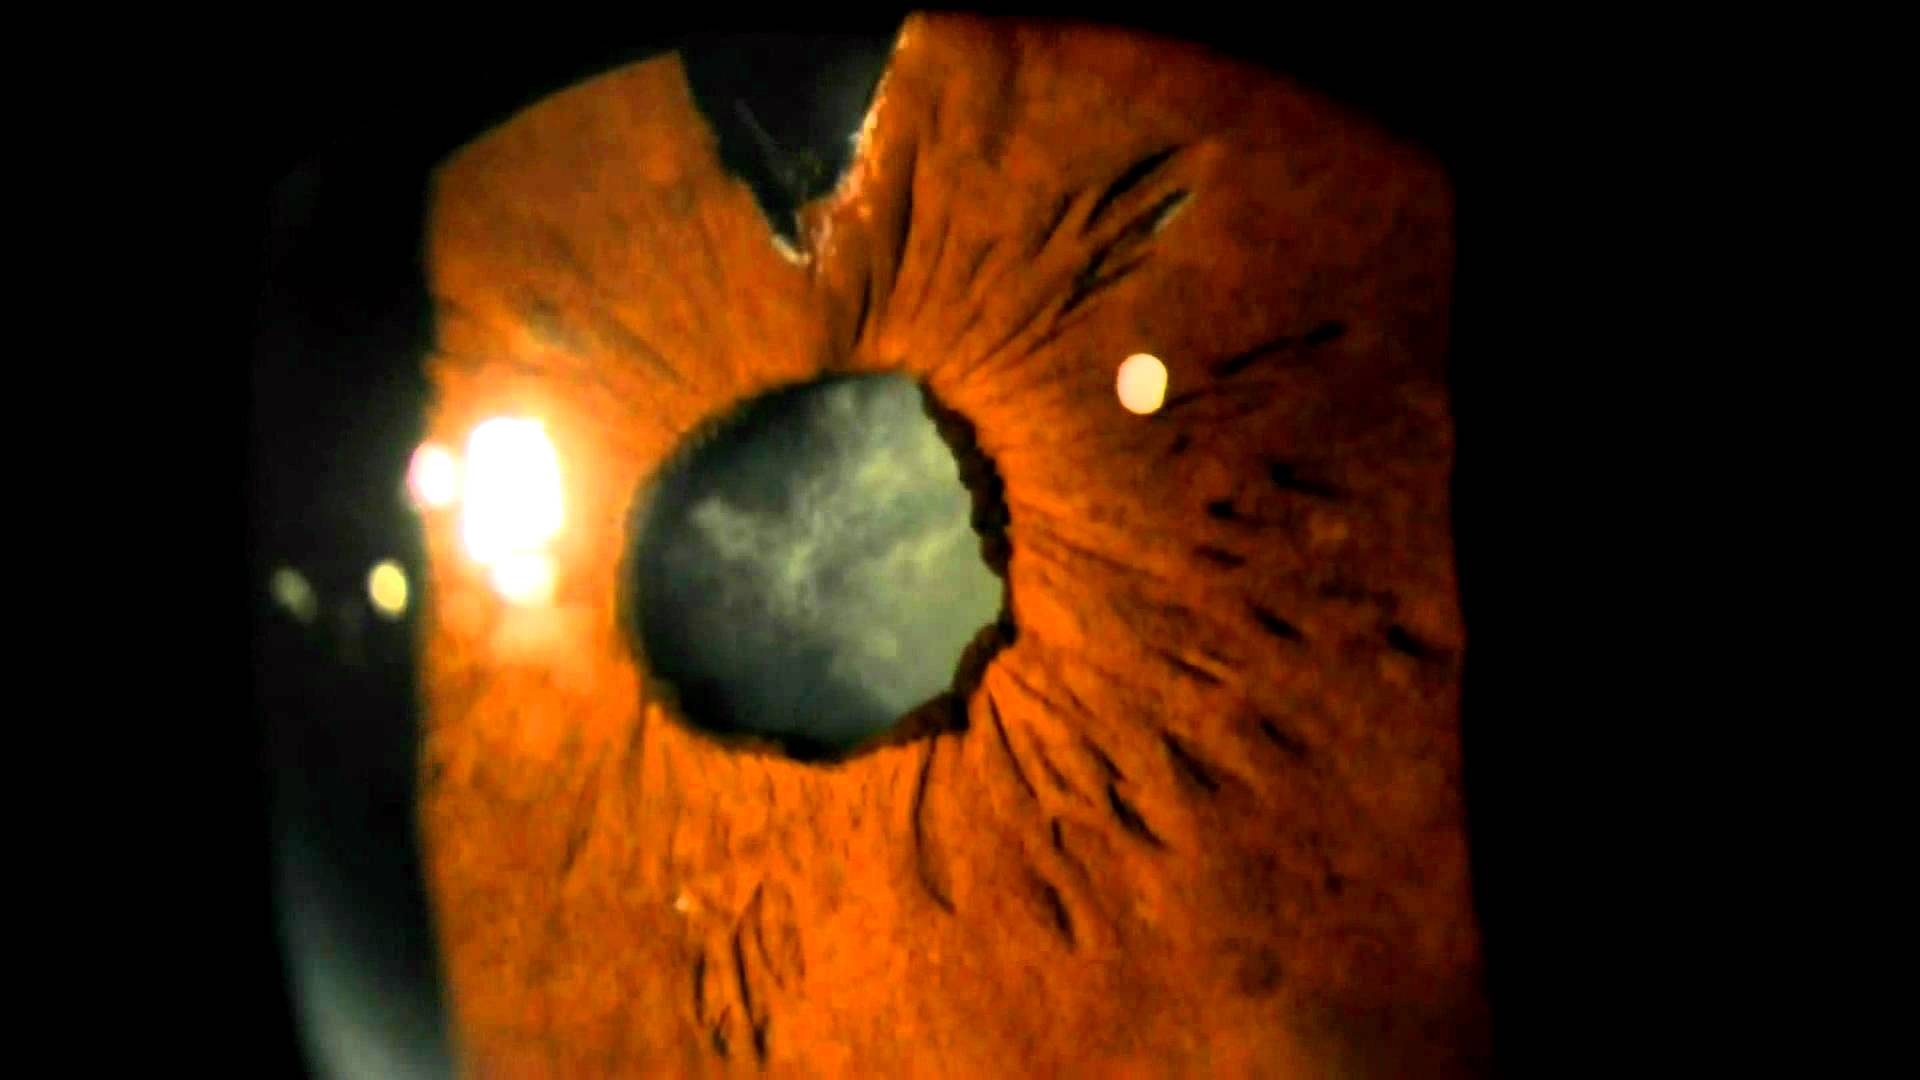
Grading the Zonular Weakness
Estimate the extent of the zonular defect in clock hours, since this determines the strategy.
Surgeons can often manage a small defect, up to about 4 clock hours, with a capsular tension ring and gentle technique.
A larger defect needs capsular hooks, a segment, or a plan for sutured fixation of the bag, or for removal of the bag and use of another lens.
In an eye with a lens that is also dislocated into the anterior chamber, treat urgently to avoid corneal damage and glaucoma.
Imaging in Phacodonesis
Ultrasound biomicroscopy and anterior segment OCT can show the zonular fibers, the ciliary body, and the position of the lens, and they help to detect subtle subluxation.
These tools are also useful in complex eyes, and they can guide the choice of fixation.
Associated Systemic Conditions
When no local cause is found, particularly in a young patient, consider a systemic cause such as Marfan syndrome or homocystinuria, and refer for the necessary evaluation.
The cardiovascular risk in Marfan syndrome and the thrombosis risk in homocystinuria are the reasons why recognizing the cause matters.
Postoperative Surveillance
Even after a successful operation, the bag may continue to shrink or shift, and the lens may decenter years later.
In addition, regular follow-up and patient education about symptoms help to catch problems early.
Document the findings for future care, including the type of ring used and the lens position.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Hoffman RS, Snyder ME, Devgan U, et al. Management of the subluxated crystalline lens. J Cataract Refract Surg. 2013;39:1904-1915.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- Yanoff M, Duker JS, eds. Ophthalmology. 5th ed. Elsevier; 2019.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 11: Lens and Cataract. AAO; current edition.
Test yourself
A few questions straight from this article.
-
Phacodonesis, a tremor of the crystalline lens on eye movement, is a sign of what?
When the zonular fibers stretch, break or fail, the lens loses its stable attachment and trembles with each saccade. -
How is phacodonesis best elicited at the slit lamp?
Asking the patient to look from side to side while observing the lens with a narrow beam reveals the tremor of the anterior lens surface. -
In a patient with zonular damage, what is iridodonesis?
In the same way that the lens wobbles in phacodonesis, the iris may tremble if the lens is absent or displaced; this is iridodonesis. -
Which condition is a leading cause of phacodonesis in older patients?
Pseudoexfoliation is a leading cause in older patients, and pseudoexfoliative material on the capsule and pupil margin suggests it as the cause. -
Which complications does phacodonesis increase the risk of during cataract surgery?
Zonular weakness raises the risk of capsular rupture, zonular dialysis, nucleus loss and vitreous loss, so vitrectomy equipment should be ready. -
Up to what extent of zonular defect can surgeons often manage phacodonesis with a capsular tension ring and gentle technique?
A defect up to about 4 clock hours can often be managed with a capsular tension ring; larger defects need hooks, a segment or sutured fixation. -
Which imaging can show the zonular fibers and ciliary body to detect subtle subluxation in phacodonesis?
Ultrasound biomicroscopy and anterior segment OCT show the zonules, ciliary body and lens position, and help guide the choice of fixation. -
Why does a lens dislocated into the anterior chamber in phacodonesis need urgent treatment?
A lens dislocated into the anterior chamber should be treated urgently to avoid corneal damage and glaucoma. -
Why does identifying homocystinuria as the cause of phacodonesis matter?
With no local cause, especially in a young patient, a systemic cause is sought; the thrombosis risk in homocystinuria is why recognizing it matters. -
Why do patients operated on for phacodonesis need long-term follow-up?
Even after a successful operation the bag may keep shrinking or shifting, so regular follow-up and documentation of the ring and lens position help.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.