Cycloplegic refraction is the standard way to measure refractive error in children.
Children accommodate strongly and hide hyperopia.
Without cycloplegia, glasses may be wrong.
Why Cycloplegic Refraction Is Needed
Accommodation in children is powerful and active.
It overcomes hyperopia and causes pseudomyopia.
Measuring without cycloplegia can mislead.
Therefore, relax accommodation before refraction.
Who Needs Cycloplegic Refraction
All young children with suspected refractive error need it.
Children with esotropia, amblyopia or headaches need it.
Adolescents with unexplained blur should also have it.
So use it freely in pediatric practice.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteCyclopentolate
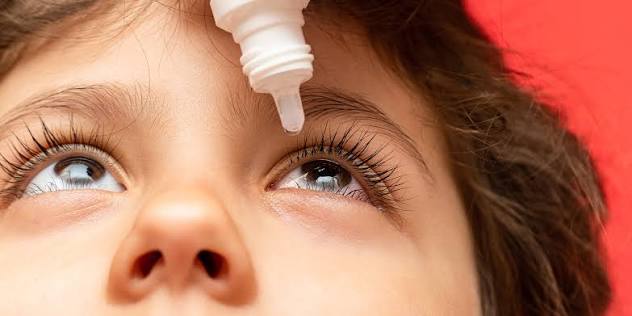
Cyclopentolate 1% is the usual agent.
It acts in 30 to 40 minutes.
Effects last for about 24 hours.
Also instill drops twice, five minutes apart.
Atropine
Atropine gives the deepest cycloplegia.
It is used in infants with esotropia or dark irides.
Effects last for days.
Therefore, reserve it for selected cases.
Tropicamide
Tropicamide is a weak cycloplegic.
It works fast and wears off quickly.
It is not enough for young hyperopes.
So use it for dilation and not for refraction in children.
Technique
Wait for full effect before retinoscopy.
Use a trial frame or lens bar.
Work in a dark room with a fixation target.
Also check the red reflex.
Retinoscopy
Streak retinoscopy gives an objective measurement.
It works in uncooperative children.
Accuracy improves with practice.
Therefore, train regularly.
Autorefraction
Handheld autorefractors help in infants.
Results should be verified by retinoscopy.
Cycloplegia is still needed.
So use devices as an aid.
Side Effects
Stinging, flushing and light sensitivity are common.
Rare systemic effects include fever, agitation and rapid pulse.
Infants with brain injury are at higher risk.
Therefore, use the lowest effective dose.
Safety Precautions
Press on the tear duct after instillation to reduce absorption.
Watch infants for several hours.
Warn parents about the symptoms.
Also avoid cyclopentolate 2% in infants.
Prescribing After Cycloplegic Refraction
Prescribe based on findings and symptoms.
Reduce the hyperopic correction slightly in some children.
Follow with a post-cycloplegic check if needed.
So tailor the glasses.
Cycloplegic Refraction in Esotropia
Full hyperopic correction often straightens accommodative esotropia (see esotropia).
Check alignment with glasses on.
Reassess regularly.
Also treat amblyopia.
Counseling Parents
Explain that drops will blur vision and enlarge pupils.
Advise sunglasses and limited reading.
Reassure that effects wear off.
Therefore, parents know what to expect.
Cycloplegic Refraction: Practical Summary
Choose the agent by age and risk, wait for full effect and use retinoscopy.
If the child has esotropia, prescribe the full correction.
Because side effects exist, give clear advice.
Finally, review the child at set intervals.
Pitfalls to Avoid
- Do not rely on non-cycloplegic refraction in young children
- Never use too short a waiting time
- Avoid strong drops in infants without caution
- Do not forget the post-visit instructions
Cycloplegic Refraction and Myopia Control
Children being treated for myopia progression need regular axial length checks.
Cycloplegic refraction gives accurate baselines.
Because pseudomyopia confuses results, always use cycloplegia.
Therefore, document the agent used.
Cycloplegic Refraction in Dark Irides
Pigmented eyes dilate more slowly.
A second drop or longer wait may be needed.
Because incomplete cycloplegia leaves residual accommodation, check the effect.
So allow more time.
Cycloplegic Refraction and Headaches
Children with headaches may have hidden hyperopia.
Cycloplegic refraction clarifies the need for glasses.
However, many headaches have other causes.
Because the exam is simple, include it in the work-up.
Cycloplegic Refraction in Adults
Young adults with unexplained blur may need it.
Older adults rarely do.
Because accommodation falls with age, tropicamide often suffices.
Therefore, choose the drug by age.
Cycloplegic Refraction and School Screening
School programs often use noncycloplegic tools.
These may overestimate myopia and underestimate hyperopia.
Because errors affect referrals, confirm abnormal results.
So pair screening with clinic exams.
Cycloplegic Refraction: Instructions for Parents
Tell parents the child will have blurred near vision for a day.
Advise sunglasses and avoiding sports where depth matters.
Because glare is common, send a hat.
Finally, provide a contact number.
Cycloplegic Refraction: Recording the Result
Write the agent, the time and the retinoscopy findings.
Note both the gross and net values.
Because later visits may compare results, keep clear records.
Therefore, store the prescription with the date.
Cycloplegic Refraction: Common Errors
Retinoscopists often measure too soon after instillation.
Others forget to account for working distance.
Because small errors matter in hyperopia, check technique.
So practice with peers.
For the latest studies, see the PubMed results for cycloplegic refraction.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Fotedar R, Rochtchina E, Morgan I, Wang JJ, Mitchell P, Rose KA. Necessity of cycloplegia for assessing refractive error in 12-year-old children: a population-based study. Am J Ophthalmol. 2007;144:307-309.
- Wallace DK, Christiansen SP, Sprunger DT, et al. Pediatric eye evaluations preferred practice pattern. Ophthalmology. 2018;125:P184-P227.
- Sankaridurg P, He M, Du Toit R, et al. Comparison of noncycloplegic and cycloplegic autorefraction in categorizing refractive error data in children. Acta Ophthalmol. 2017;95:e633-e640.
- Morgan IG, Iribarren R, Fotouhi A, Grzybowski A. Cycloplegic refraction is the gold standard for epidemiological studies. Acta Ophthalmol. 2015;93:581-585.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.