Nitrous oxide and intraocular gas are a dangerous combination.
Nitrous oxide diffuses into a gas bubble faster than nitrogen leaves it.
Therefore, the bubble expands and the eye pressure can rise to blinding levels.
Why Gas Is Used in the Eye
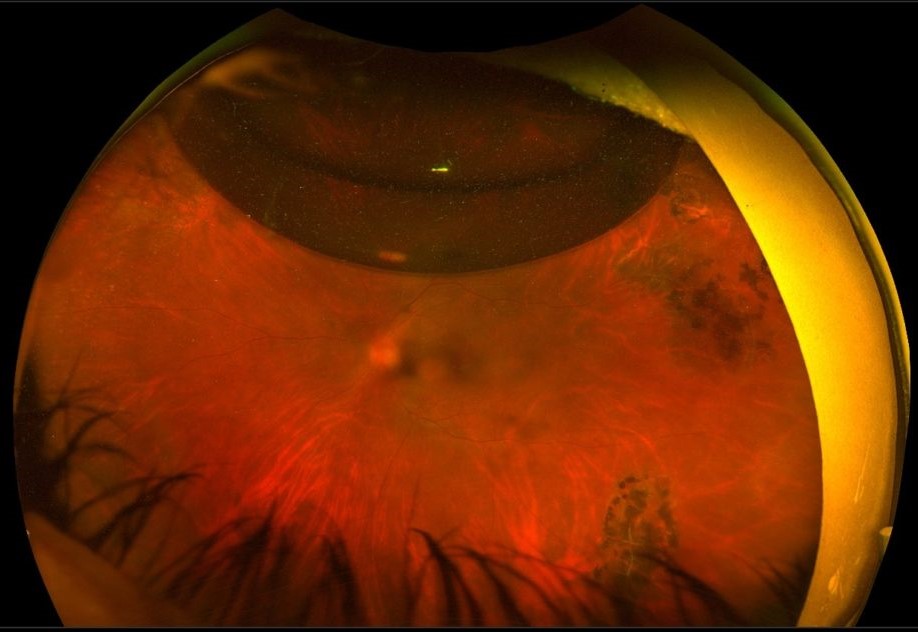
Gas bubbles press on a retinal tear and hold it against the pigment epithelium.
Surgeons use air, sulfur hexafluoride or perfluoropropane after vitrectomy or pneumatic retinopexy.
Also, the bubble also supports macular hole repair.
As a result, many patients carry a bubble for days to weeks.
How Long Each Gas Lasts
Air lasts about five days.
Sulfur hexafluoride lasts about two weeks and perfluoropropane about six to eight weeks.
Also, the pure gases expand in the eye, and the mixtures do not.
Therefore, the duration shapes how long anesthesia must avoid nitrous oxide.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteHow Nitrous Oxide and Intraocular Gas Interact
Nitrous oxide is about 30 times more diffusible in blood than nitrogen.
It enters the bubble quickly while nitrogen leaves slowly.
Also, the bubble can double or triple in volume within minutes.
As a result, the pressure inside a closed eye climbs fast.
Eye Damage From Nitrous Oxide and Intraocular Gas
A rapid rise in pressure can close the central retinal artery.
Prolonged elevation then causes permanent vision loss.
Also, Hart and colleagues described blindness after nitrous oxide anesthesia in an eye with perfluoropropane.
Therefore, the harm is real and not theoretical.
Evidence for Nitrous Oxide and Intraocular Gas
Stinson and Donlon modeled the interaction with air and sulfur hexafluoride.
Wolf and colleagues reported pressure rises after nitrous oxide in eyes with sulfur hexafluoride.
Also, Fu and colleagues described complications in a series of patients.
In addition, all reports urge strict avoidance.
Stopping the Gas Before Injection
Stop nitrous oxide at least 15 minutes before a gas bubble is injected.
Use oxygen and air during that time.
Also, communicate the plan clearly between the surgeon and the anesthetist.
Therefore, build this step into the operating room checklist.
After Surgery: Nitrous Oxide and Intraocular Gas
The bubble remains for days to weeks, and nitrous oxide stays unsafe for all that time.
Many sources advise about five days after air, ten after sulfur hexafluoride and four weeks after perfluoropropane.
Also, the gas can take longer in some eyes.
As a result, wait until the bubble is gone.
Warnings for Nitrous Oxide and Intraocular Gas
Give each patient a wristband or card that states that a gas bubble is in the eye.
Tell them to show it to dentists, anesthetists and emergency staff.
Also, ask them to avoid air travel and mountain trips (see intraocular gas and air travel).
In addition, record the gas type and date in the notes.
Anesthetic Alternatives
Intravenous anesthesia with propofol avoids the issue.
Volatile agents such as sevoflurane do not expand gas.
Also, local anesthesia suits most procedures.
Therefore, ask the anesthetist to plan without nitrous oxide.
Other Procedures That Use Nitrous Oxide
Dental work, labor analgesia and some emergency care use nitrous oxide.
Also, some sedation kits include it.
Patients can forget about the bubble during these events.
As a result, repeat the warning at each visit.
If Nitrous Oxide and Intraocular Gas Meet
Measure the pressure at once and check the optic nerve perfusion.
Release some of the gas with a needle in the pars plana if the pressure stays high.
Also, give pressure-lowering drugs while preparing.
Therefore, treat suspected exposure as an emergency.
Hypotony When Nitrous Oxide Stops
When the patient stops breathing the gas, the bubble can shrink rapidly.
The shrinkage can produce low pressure and a shallow chamber.
Also, the effect is smaller than the expansion but can still harm.
In addition, watch the eye after a short exposure.
Pitfalls to Avoid
- Do not assume that a small bubble is safe
- Never rely on the patient to remember the warning
- Do not stop the vigilance when the bubble looks small
- Never forget that pure gases keep expanding for hours
Communication Before Surgery
The surgeon should tell the anesthetist about the gas at the preoperative huddle.
Write the gas type on the chart and the board.
Also, place a warning on the patient’s file.
Therefore, no one is surprised in the operating room.
Pneumatic Retinopexy and Office Gas
Office injections of gas also create bubbles.
Patients may then need anesthesia for unrelated events.
Also, they may forget the bubble within days.
As a result, give the wristband at every gas procedure.
Role of the Anesthetist
The anesthetist should check the notes for gas on every admission.
They should refuse nitrous oxide until the bubble is gone.
Also, they should record the rule in the anesthesia chart.
In addition, they should educate junior staff.
For the latest studies, see the PubMed results for nitrous oxide and intraocular gas.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Stinson TW, Donlon JV. Interaction of intraocular air and sulfur hexafluoride with nitrous oxide: a computer simulation. Anesthesiology. 1982;56:385-388.
- Wolf GL, Capuano C, Hartung J. Nitrous oxide increases intraocular pressure after intravitreal sulfur hexafluoride injection. Anesthesiology. 1983;59:547-548.
- Fu AD, McDonald HR, Eliott D, et al. Complications of general anesthesia using nitrous oxide in eyes with preexisting gas bubbles. Retina. 2002;22:569-574.
- Hart RH, Vote BJ, Borthwick JH, McGeorge AJ, Worsley DR. Loss of vision caused by expansion of intraocular perfluoropropane (C3F8) gas during nitrous oxide anesthesia. Am J Ophthalmol. 2002;134:761-763.
Test yourself
A few questions straight from this article.
-
Why does nitrous oxide anesthesia enlarge an intraocular gas bubble?
Nitrous oxide diffuses into the bubble faster than nitrogen leaves it, so the bubble can double or triple in volume within minutes. -
Roughly how much more diffusible in blood is nitrous oxide than nitrogen?
Nitrous oxide is about 30 times more diffusible in blood than nitrogen, so it floods the bubble while nitrogen leaves slowly. -
Which vessel can be occluded by the pressure rise when nitrous oxide expands an intraocular gas bubble?
A rapid pressure rise can close the central retinal artery, and prolonged elevation causes permanent vision loss. -
How long does perfluoropropane gas typically remain in the eye?
Air lasts about five days, sulfur hexafluoride about two weeks and perfluoropropane about six to eight weeks. -
How long before intraocular gas injection should nitrous oxide anesthesia be stopped?
Stop nitrous oxide at least 15 minutes before a gas bubble is injected, using oxygen and air during that time. -
After retinal surgery with an intraocular gas bubble, for how long is nitrous oxide unsafe?
Nitrous oxide stays unsafe for as long as the bubble remains, which can be longer than expected in some eyes, so wait until it is gone. -
What should every patient with an intraocular gas bubble carry to warn dentists and anesthetists?
Give each patient a wristband or card stating that a gas bubble is in the eye, to show to dentists, anesthetists and emergency staff. -
Which anesthetic approach avoids bubble expansion in an eye containing intraocular gas?
Intravenous anesthesia with propofol avoids the issue, volatile agents such as sevoflurane do not expand gas, and local anesthesia suits most procedures. -
If nitrous oxide has expanded an intraocular gas bubble and pressure stays high, what should be done?
Measure the pressure, check optic nerve perfusion and release some gas through the pars plana with a needle if the pressure stays high, giving pressure-lowering drugs meanwhile. -
What can happen when nitrous oxide is stopped in an eye with an intraocular gas bubble?
When the patient stops breathing nitrous oxide the bubble can shrink rapidly, producing low pressure and a shallow chamber.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.